Related Experiment Video
Updated: Jun 2, 2026

Skin Biopsy for Diagnosing Discoid Lupus Erythematosus
Published on: June 10, 2025
Disseminated lupus vulgaris
Taru Garg1, Ramchander, Rashmi Shrihar
1Department of Dermatology, Venereology, and Leprosy, Lady Hardinge Medical College, New Deihi, India. drtarugarg@rediffmail.com

Abstract:
A 28-year-old woman presented with reddish raised, shiny lesions over the face and ears present for the past 3 years. Four years ago, she developed in her left axilla a nodule that became fluctuant and tender, which ruptured to discharge seropurulent material. It subsided after the patient had received antibiotics for 6 months, leaving puckered scarring. There was no history of antituberculous treatment. After 1 year, she developed papulonodular lesions on her face, nose, and ears. There was now a history of malaise, fever, dry cough, and anorexia and weight loss for the past 2 months. The patient was fully vaccinated in childhood, including against varicella infection. The general physical examination revealed lymphadenopathy involving cervical, axillary, and inguinal lymph nodes 0.5 x 0.5 cm to 1 x 1.5 cm, firm in consistency, and nontender. They were discrete except in the left axilla where multiple matted lymph nodes were present with overlying scarring and a papule. Her systemic examination was normal. Cutaneous examination showed a shiny erythematous plaque 3x2 cm with central atrophy and scarring on the face (Figure). It was comprised of multiple shiny nontender soft papules arranged in annular configuration. Similar discrete papules and nodules with adherent fine scaling were seen bilaterally on the alar prominence of the nose, lower lip, and post-auricular area. On diascopy, apple jelly nodules were seen. The hemogram, liver function tests, and renal function tests were normal, except for an elevated erythrocyte sedimentation rate. The Mantoux test showed erythema and an induration of 20 x 20 cm. A posteroanterior view on the chest x-ray showed fibrotic changes suggestive of pulmonary tuberculosis. Ultrasonography of the abdomen and pelvis showed no tubercular foci. Human immunodeficiency virus serology by enzyme-linked immunosorbent assay with 3 different kits was nonreactive. Histopathology from a nodule showed a focally thinned-out epidermis with follicular plugging and multiple epithelioid cell granulomas, rimmed by lymphocytes in the deeper portion of the dermis, mainly peri-appendageal. Stain for acid-fast bacteria was negative. Cultures from the skin lesions were negative. The patient was diagnosed as having lupus vulgaris with multiple lesions of varying morphology at different sites with pulmonary tuberculosis and healed lymph node involvement.

Related Concept Videos
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:26
Rocky Mountain Spotted Fever
 01:30
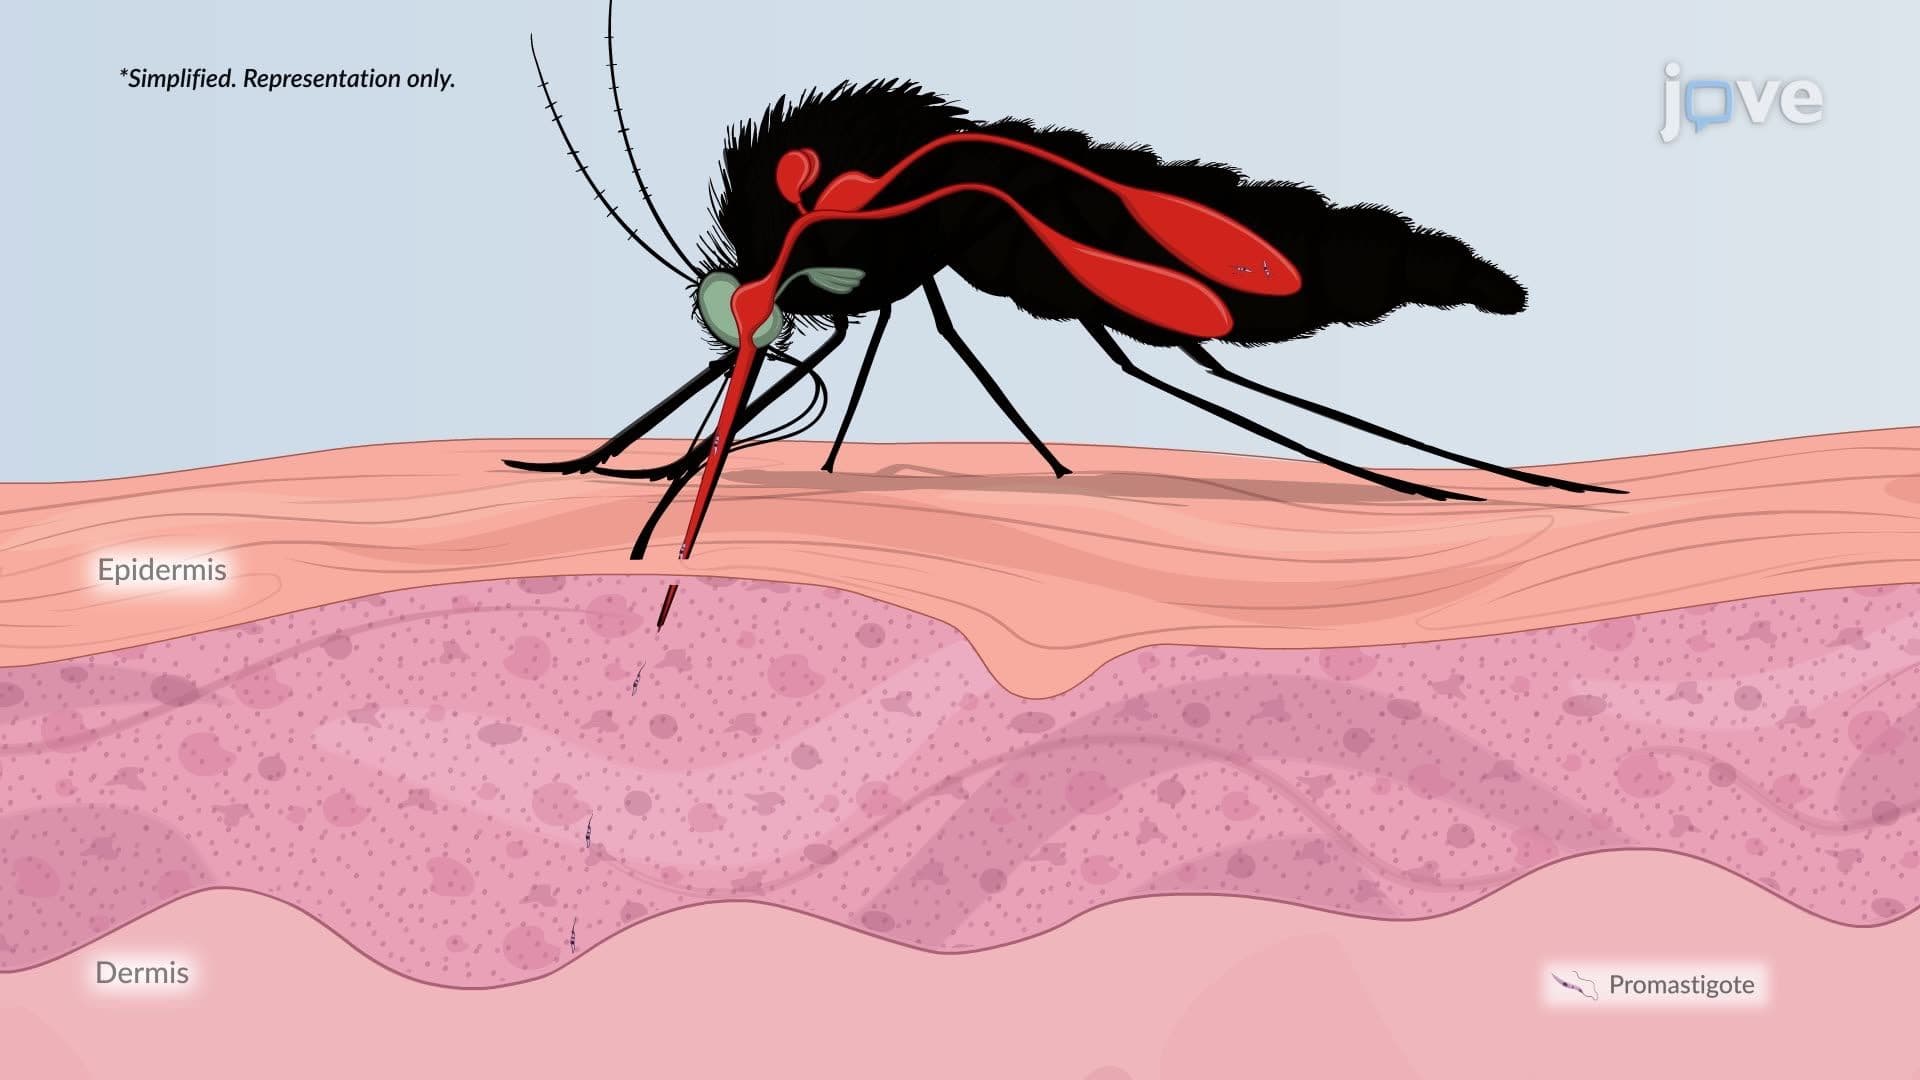
Leishmaniasis
 01:15
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...