Related Experiment Video
Updated: Jun 2, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Perineal repair after extralevator abdominoperineal excision for low rectal cancer
Henrik Kidmose Christensen1, Peter Nerstrøm, Troels Tei
1Surgical Department P, Aarhus University Hospital, Aarhus, Denmark. hkchristensen@gmail.com

Background:
Extralevator abdominoperineal excision for low rectal cancer includes resection of the pelvic floor as a part of the operative technique to reduce the risk of tumor-involved section margins.
Objective:
This study aimed to compare perineal defect reconstruction with a fasciocutaneous gluteal flap vs biological mesh regarding healing and occurrence of perineal hernia.
Design:
Retrospective review of medical records comparing surgical methods during 2 consecutive periods.
Settings:
Tertiary care university medical center (Colorectal Section, Surgical Department P, Aarhus University Hospital, Denmark).
Patients:
Patients with low rectal cancer who underwent extralevator abdominoperineal excision from December 2005 through October 2008 were included.
Intervention:
The perineum was reconstructed with a fasciocutaneous gluteal flap in the first period and with a biological mesh in the second period.
Main Outcome Measures:
We assessed rates of perineal wound infection requiring surgical intervention and perineal hernia diagnosed by clinical examination.
Results:
The study comprised 57 patients: 33 patients with gluteal flap and 24 with biological mesh reconstruction. Perineal hernia developed in 7 (21%) patients in the gluteal flap group and in none (0%) of the patients in the mesh group (P < .01). Median follow-up was 3.2 (1.7-4.3) years for gluteal flap and 1.7 (0.4-2.2) years for biologic mesh. All hernias occurred within the first postoperative year (median, 6 months; range, 1-12 months). Infectious complications were seen in 2 patients (6%) with a gluteal flap and in 4 patients (17%) with mesh repair (P = .26). After 3 months, all patients were completely healed except for 1 patient in each group with a persistent perineal sinus. The median (range) hospital stay was 14 (8-23) days in the flap group and 9 days (6-35) in the mesh group (P < .05).
Limitations:
This was a nonrandomized retrospective observational study comparing 2 methods used in different time periods.
Conclusion:
We recommend biological mesh reconstruction of the pelvic floor after extralevator abdominoperineal resection because this method can achieve a high healing rate with an acceptable risk of infection, a low hernia rate, and a shorter hospital stay without donor-site morbidity.

Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
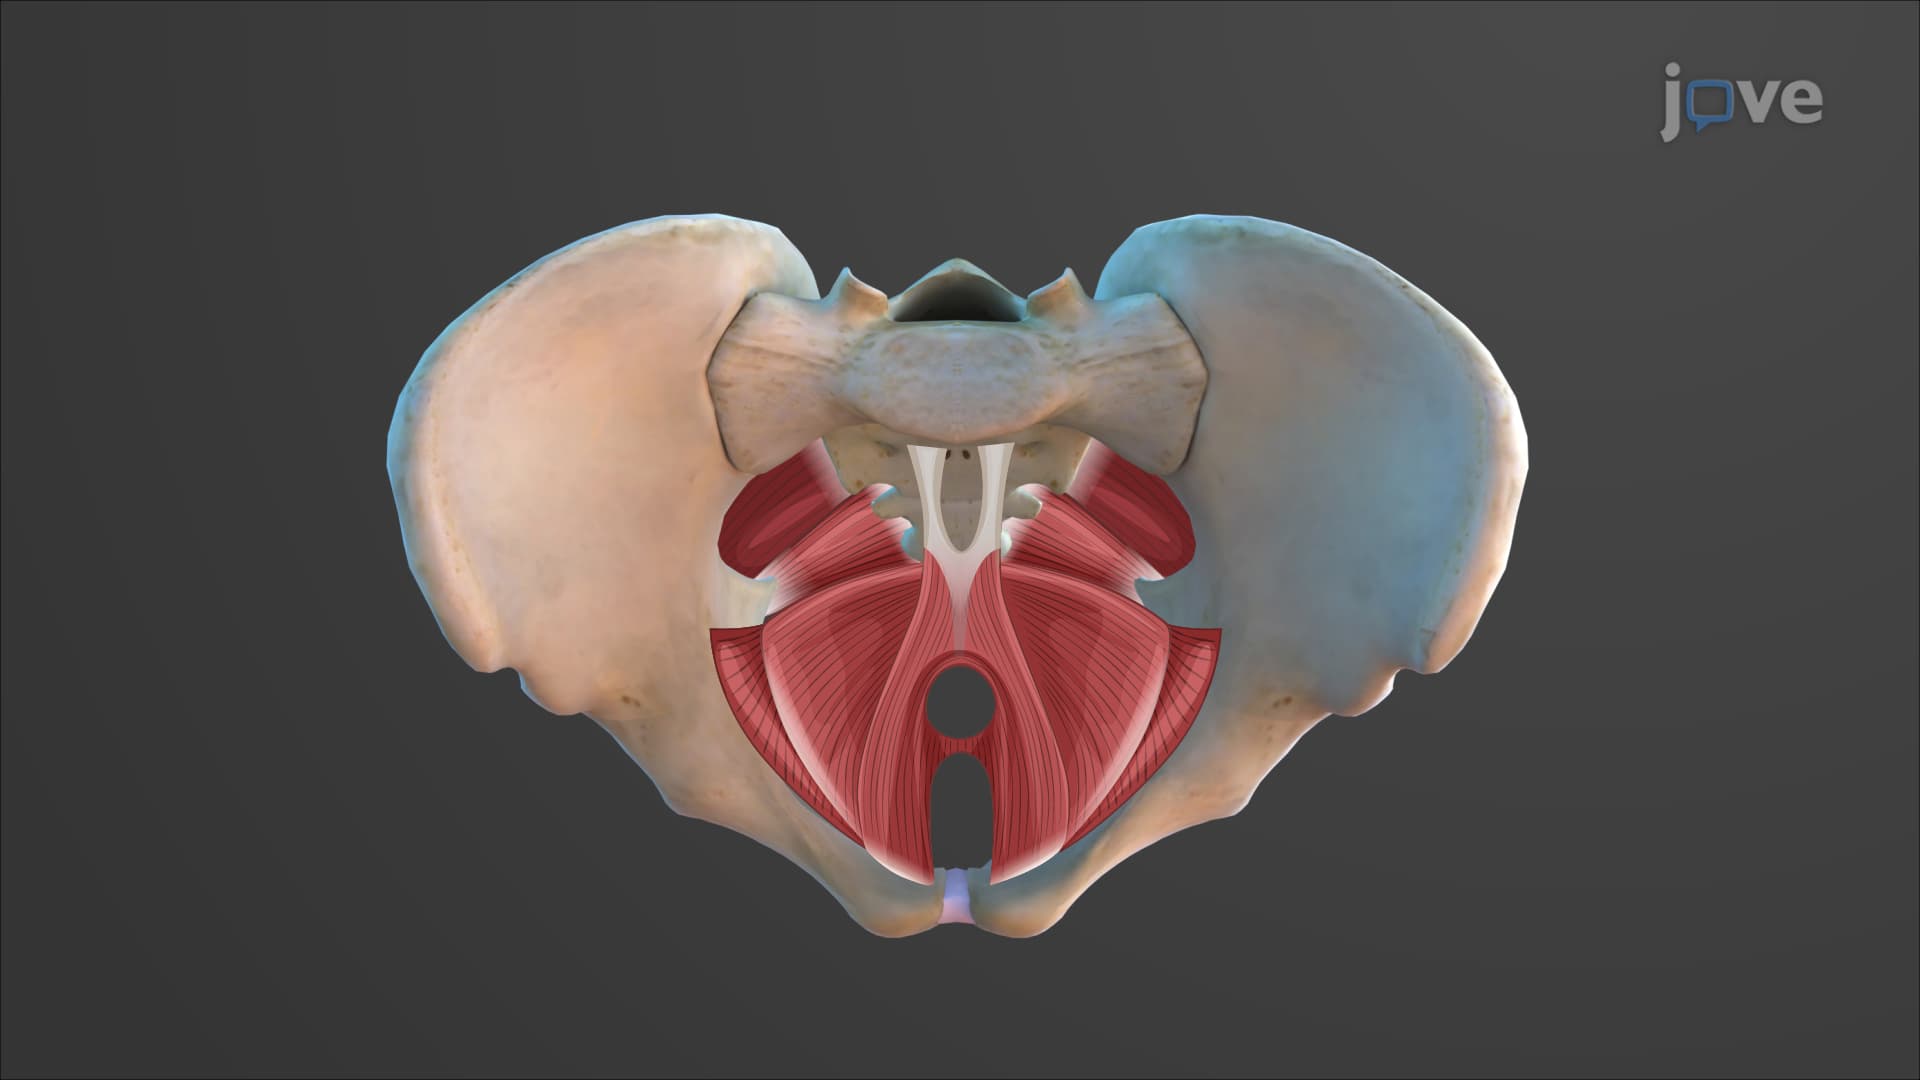
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...