Related Experiment Video
Updated: Jun 2, 2026
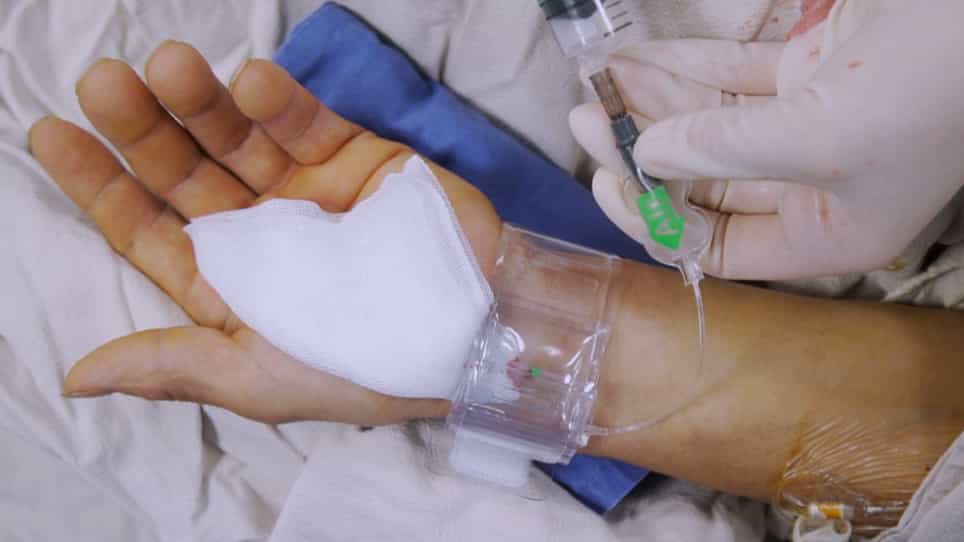
Transradial Access Chemoembolization for Hepatocellular Carcinoma Patients
Published on: September 20, 2020
Transradial percutaneous coronary intervention in acute ST elevation myocardial infarction and high-risk patients:
1Department of Cardiology, Changi General Hospital, 2 Simei Street 3, Singapore 529889.

Insights
Primary transradial percutaneous coronary intervention (TRI) is effective for ST-elevation myocardial infarction (STEMI), even in high-risk patients. This study shows high success rates and comparable procedural times to traditional methods.
Area of Science:
- Cardiology
- Interventional Cardiology
- Vascular Medicine
Background:
- Primary transradial percutaneous coronary intervention (TRI) is established for stable acute coronary syndrome.
- Its application in acute ST-elevation myocardial infarction (STEMI), particularly in high-risk populations, requires further evaluation.
Purpose of the Study:
- To assess the feasibility and efficacy of primary TRI in patients with acute STEMI.
- To evaluate outcomes including success rates, door-to-balloon time, and major adverse cardiac events in a high-risk registry cohort.
Main Methods:
- A single-centre case series of 138 patients undergoing primary TRI for STEMI.
- TRI was performed using a 6-Fr guiding catheter irrespective of Killip class.
- Outcomes included TRI success, door-to-balloon time, procedure duration, contrast volume, and 30-day/six-month major adverse cardiac events.
Main Results:
- Primary TRI was successful in 97.1% of 134 patients (4 failed, requiring femoral approach).
- Median door-to-balloon time was 92 minutes; median procedure time was 39 minutes.
- Most patients (91.8%) presented with Killip class I or II; 8.2% were in Killip class III/IV.
Conclusions:
- Primary TRI demonstrates high success rates and comparable procedural times to the femoral approach.
- It is a feasible and effective strategy for managing acute STEMI, including in high-risk individuals.
Introduction:
Primary transradial percutaneous coronary intervention (TRI) is shown to be efficacious in stable patients with acute coronary syndrome. We aimed to evaluate the application of primary TRI for acute ST elevation myocardial infarction (STEMI), including among high-risk patients from our registry.
Methods:
This was a single-centre case series comprising 138 patients who underwent primary TRI for STEMI between May 2007 and June 2008. TRI was attempted with a 6-Fr guiding catheter in all patients regardless of Killip class status. Outcome measures were success rates of primary TRI, door-to-balloon time, procedure duration and volume of contrast used. All patients were followed up for major adverse cardiac events in-hospital, at 30 days and six months.
Results:
A total of 138 patients had primary TRI attempted for STEMI. Four patients failed primary TRI and required a femoral approach. The remaining 134 patients underwent primary TRI. The mean patient age was 56.4 years. Most patients with acute STEMI presented in Killip class I and II (91.8 percent). Only 8.2 percent were in Killip class III or IV on admission. 50 percent of patients presented with anterior STEMI. The median door-to-balloon time for this group was 92 (interquartile range [IQR] 77-121) minutes, with a median procedure time of 39 (IQR 29-51) minutes. The success rate of primary TRI was 97.1 percent.
Conclusion:
Success rate, procedural and radiation time for TRI are comparable to those achieved via the femoral approach. Primary TRI is therefore a feasible and effective approach for acute STEMI, even in high-risk patients.

Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:30
Acute Coronary Syndrome III: Diagnostic Studies