Small airway function, exhaled NO and airway hyper-responsiveness in paediatric asthma
Related Experiment Video
Updated: Jun 2, 2026
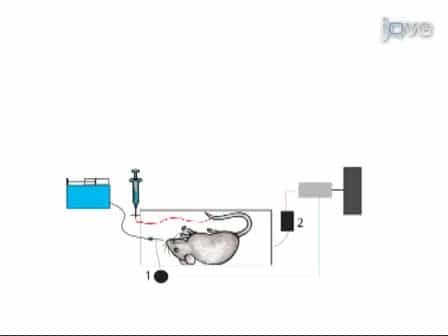
A Reversible, Non-invasive Method for Airway Resistance Measurements and Bronchoalveolar Lavage Fluid Sampling in Mice
Published on: April 13, 2010
Christina Keen1, Anna-Carin Olin, Göran Wennergren
1Department of Paediatrics, University of Gothenburg, Queen Silvia Children's Hospital, SE-416 85 Gothenburg, Sweden. christina.keen@telia.com

Insights
Small airway dysfunction is common in pediatric asthma and linked to airway inflammation and hyper-responsiveness. These findings suggest small airway issues are key in childhood asthma management.
Area of Science:
- Pediatric Pulmonology
- Respiratory Medicine
- Asthma Research
Background:
- Asthma is a chronic inflammatory airway disorder affecting peripheral airways.
- Current guidelines rely on symptoms and spirometry (FEV1) for diagnosis and treatment.
- FEV1 is an inadequate measure of small airway function, asthma control, and inflammation.
Purpose of the Study:
- To evaluate the role of small airway dysfunction and inflammation in pediatric asthma.
- To investigate the relationship between small airway dysfunction, airway inflammation, and airway hyper-responsiveness (AHR).
Main Methods:
- Small airway function assessed using the SF(6) multiple breath inert gas washout (MBW) technique (LCI, S(cond), S(acin)) in 47 asthmatic children and 74 controls.
- Exhaled nitric oxide at 50 mL/s (FENO(50)) measured to determine alveolar and bronchial NO flux (airway inflammation surrogate).
- Airway hyper-responsiveness (AHR) assessed via isocapnoic dry air hyperventilation challenge.
Main Results:
- 66% of asthmatic children showed impaired S(cond), and 38% had impaired S(acin).
- Increased LCI and decreased FEV1 were observed in 15% of asthmatic subjects.
- Subjects with AHR exhibited higher S(cond) and FENO(50) levels. Elevated FENO(50) and bronchial NO flux were noted in asthmatics versus controls.
- S(cond) correlated with FENO(50) and alveolar NO; S(acin) correlated with alveolar NO in asthmatic children.
Conclusions:
- Small conducting airway dysfunction is significantly associated with airway inflammation in pediatric asthma.
- These findings highlight the importance of small airway dysfunction in the pathophysiology of childhood asthma.
- Small airway dysfunction is linked to airway hyper-responsiveness, suggesting a comprehensive approach to asthma management is needed.
Background:
Asthma is a chronic inflammatory airway disorder known to involve the peripheral airways. Current guidelines state that diagnosis and treatment should be guided by symptoms and spirometry. FEV(1) is, however, a poor marker of small airway function and correlates poorly with asthma control and airway inflammation.
Aims:
To assess the contribution of small airway dysfunction and inflammation in paediatric asthma. A secondary aim was to study the associations between small airway dysfunction, airway inflammation and airway hyper-responsiveness (AHR).
Methods:
Small airway function was measured as LCI, S(cond) and S(acin), evaluated with the SF(6) multiple breath inert gas washout (MBW) technique, in 47 asthmatic children and 74 healthy controls. Exhaled NO at multiple exhalation flow rates including 50 mL/s (FENO(50)) was assessed to calculate alveolar NO and bronchial NO flux (a surrogate for airway inflammation). AHR was evaluated with isocapnoic dry air hyperventilation challenge in the asthmatic children.
Results:
S(cond) was elevated in 31 (66%) and S(acin) in 18 (38%) of the asthmatic subjects. LCI was increased and FEV(1) decreased in 7 (15%) of the subjects with asthma. Individuals with AHR had higher S(cond) (p = 0.001) and FENO(50) (p < 0.0001) than those without AHR. The levels of FENO(50) and bronchial NO flux were elevated in asthmatic subjects compared with healthy controls. In asthma, S(cond) correlated with FENO(50) (r(s) = 0.42, p = 0.003) and alveolar NO (r(s) = 0.40, p = 0.011), and S(acin) correlated with alveolar NO (r(s) = 0.40, p = 0.015).
Conclusion:
Dysfunction of small conducting airways is associated with airway inflammation and hyper-responsiveness in paediatric asthma.
Related Concept Videos
 01:28
Asthma I: Introduction
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:05
Breathing
 01:29
Asthma-I: Introduction
 01:13
Asthma III: Clinical Manifestations