Related Experiment Video
Updated: Jun 1, 2026
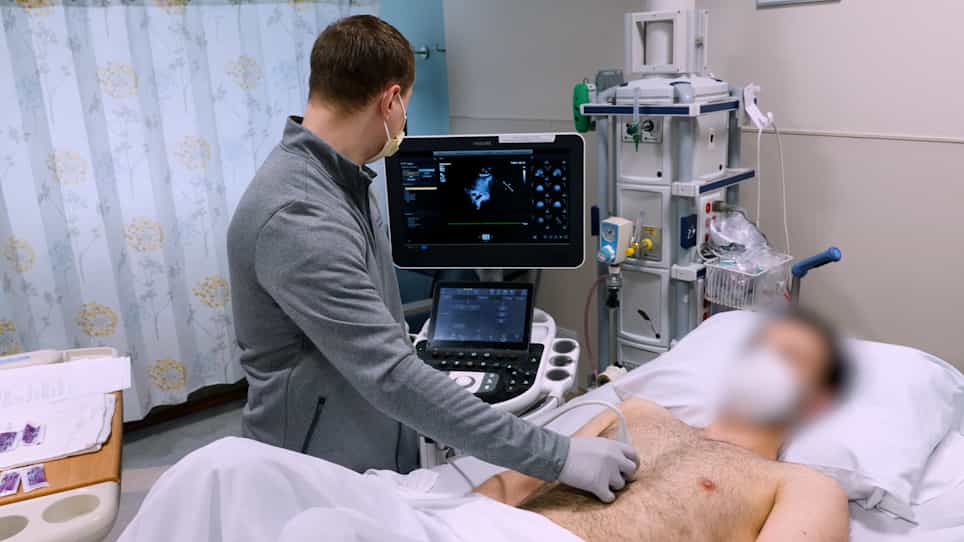
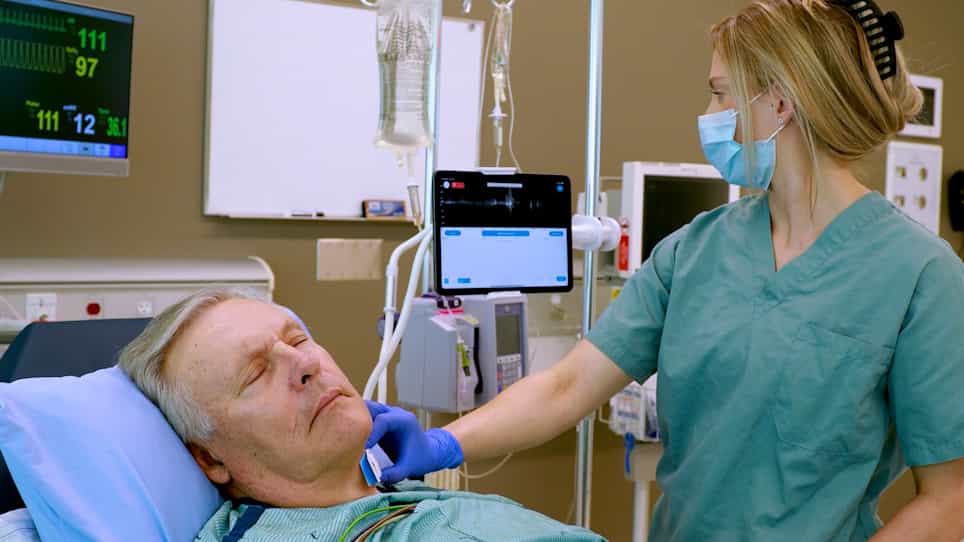
Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Inferior vena cava variation compared to pulse contour analysis as predictors of fluid responsiveness: a prospective
Enrique Machare-Delgado1, Matthew Decaro, Paul E Marik
1Division of Pulmonary and Critical Care Medicine, Thomas Jefferson University, Philadelphia, PA, USA.

Background:
Both occult hypoperfusion and volume overload are associated with increased morbidity and mortality in critically ill patients. Accurately predicting fluid responsiveness (FRes) allows for optimization of cardiac performance while avoiding fluid overload and prolonged mechanical ventilation.
Objective:
To simultaneously assess the ability to predict FRes using the stroke volume variation (SVV) obtained with the Vigileo/Flotrac monitor and inferior vena cava respiratory variation (ΔIVC) measured by standard echocardiography ([ECHO) during mechanical ventilation.
Methods:
We included medical intensive care unit (ICU) patients undergoing mechanical ventilation that required vasopressors, had worsening organ function, and that were well adapted to the ventilator. We excluded patients requiring escalating doses of vasopressors, hemodialysis, with ascites and patients with atrial fibrillation or a heart rate >120/min. Stroke volume index (SVI) and SVV were obtained from the Vigileo monitor whereas ΔIVC was obtained with ECHO (M-mode). Doppler ECHO was used to measure SVI and used to determine FRes (defined by SVI increase ≥ 10%). A data set was obtained before and 30 minutes after a 10-minute fluid challenge (FC) with 500 mL of saline.
Results:
In all, 25 patients were prospectively enrolled over an 8-month period. A total of 12 patients had acute respiratory distress syndrome (ARDS), 3 had a cardiac arrest, and 10 had sepsis. The patients' mean age was 61.36 years (±13.7), study enrollment since ICU admission was 3.4 days (±3.39), the Sequential Organ Failure Assessment (SOFA) score was 12.44 (±2.59), and the tidal volume 8.6 mL/kg (±1.68). Of the 25 patients, 8 (32%) were FRes. The correlation coefficient between the baseline ΔIVC and percentage increase in SVI (by ECHO) after an FC was R(2) = .51 with a receiver operating characteristic (ROC) curve of 0.81 while that for the baseline SVV by Vigileo was R(2) = .12 with an ROC curve of 0.57. The mean SVI bias between ECHO and Vigileo was -2 mL/m(2), the precision was -18 to 14 and the mean error was 46%.
Conclusions:
ECHO assessment of the IVC variation during mechanical ventilation may prove to be a useful technique to predict FRes and guide fluid resuscitation in the ICU. The SVV obtained with the Vigileo monitor failed to predict FRes likely due to lack of calibration and the use of a complex algorithm that may be unreliable in patients with sepsis.
Related Concept Videos
 01:19
Assessing Blood pressure using a doppler ultrasound
Pre-Procedural Guidelines for Doppler Ultrasound Blood Pressure Assessment:
Preparation of Equipment:
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system as it...
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.