Related Experiment Video
Updated: Jun 1, 2026
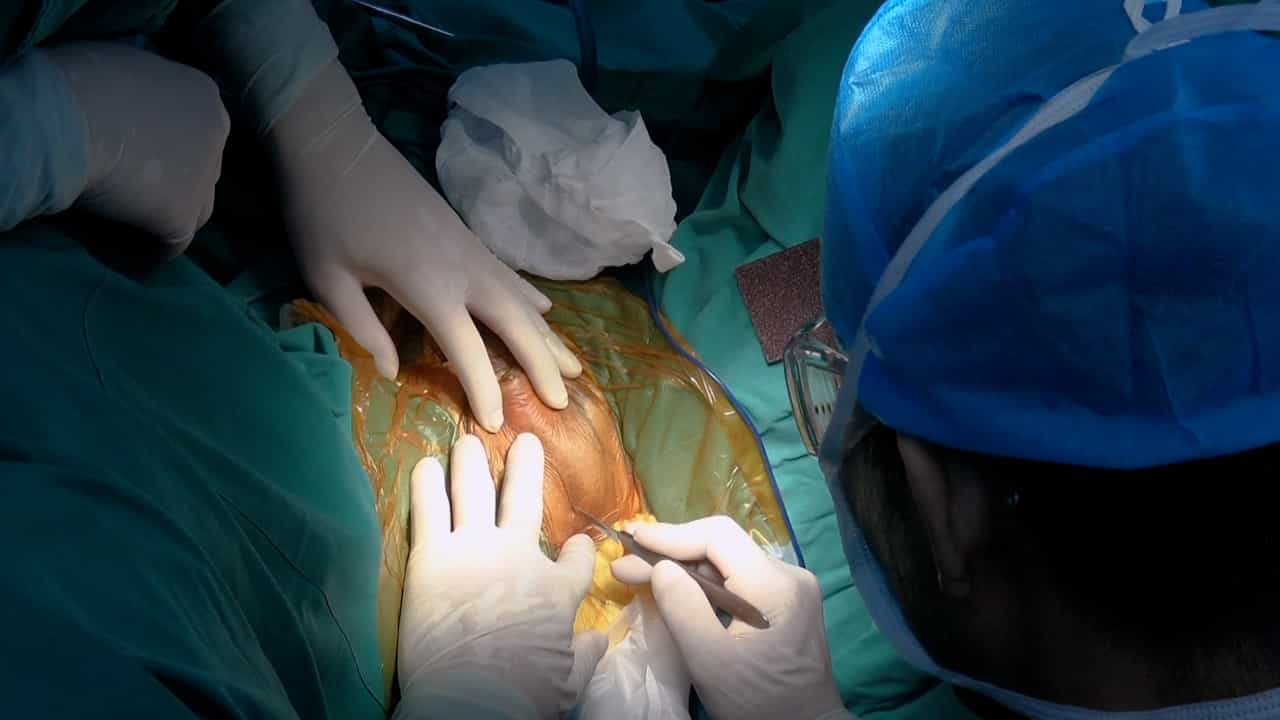

Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
Incidence of postoperative urinary retention (POUR) after joint arthroplasty and management using ultrasound-guided
T Balderi1, G Mistraletti, E D'Angelo
1Service of Anesthesia and Resuscitation IV, Department of Surgery, University of Pisa, Pisa, Italy.

Background:
Postoperative urinary retention (POUR) following lower limb arthroplasty is a common complication. The aim of this observational study was to establish the incidence of POUR and assess the usefulness of an ultrasonographic nurse-driven protocol, thereby avoiding elective bladder catheterization.
Methods:
Two-hundred and eighty six consecutive patients undergoing elective hip and knee arthroplasty were retrospectively studied. None of the patients received elective bladder catheterization. Data on risk factors for POUR, urinary tract infections, length of hospital stay and analgesia were collected. Student's t, Wilcoxon rank-sum, ANOVA and Kruskall-Wallis tests were performed for comparison among two or more groups. Categorical variables were studied using Pearson's χ2 test. Results were considered significant when the P value <0.05.
Results:
Of the 286 patients studied, 49 (17%) required indwelling catheter for 24-48 h. Patients who had POUR had more risk factors (P<0.05) and had longer hospital stays (P<0.05). When comparing analgesia, continuous peripheral nerve block (CPNB) had the least impact on POUR (15.8%), while epidural analgesia had the greatest impact (48.1%).
Conclusion:
Bladder scanners timely detect POUR following lower joint arthroplasty, making elective bladder catheterization unnecessary.
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:24
Imaging Studies II: Ultrasonography
 01:30
Urinary Tract Calculi III: Medical Management
 01:28
Urinary Tract Calculi V: Nursing Management
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography