Related Experiment Video
Updated: Jun 1, 2026
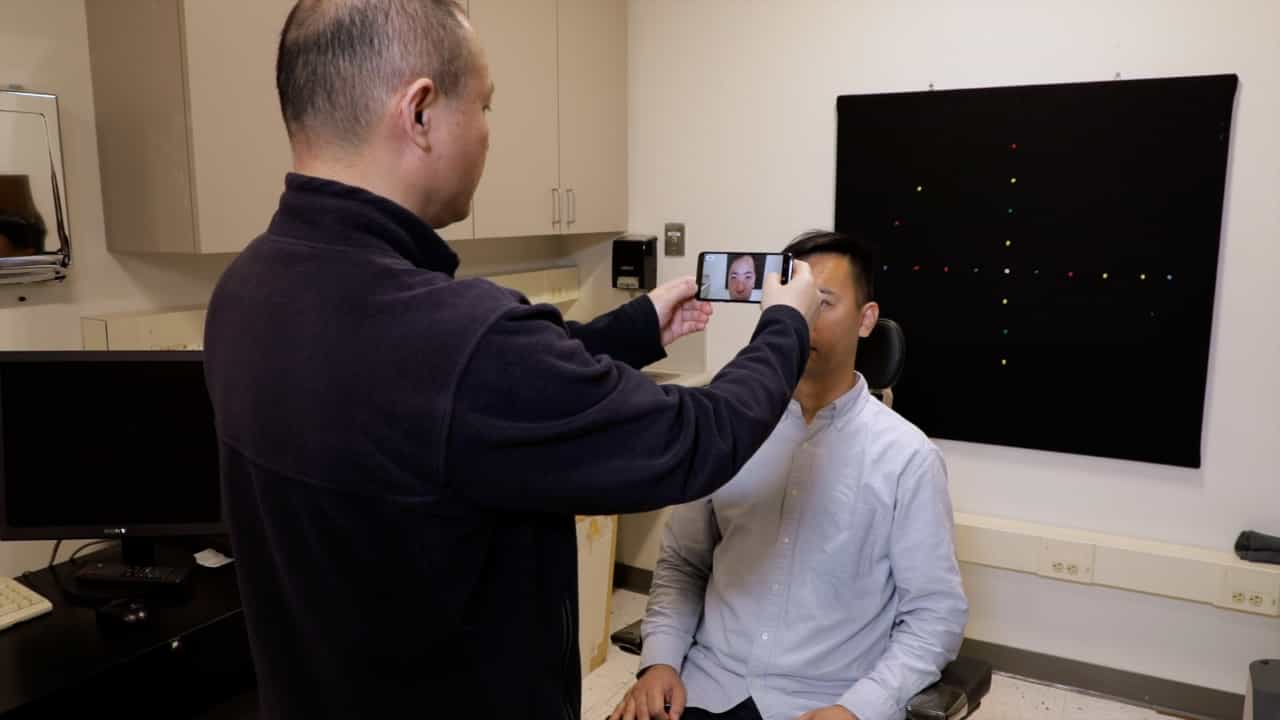

Subjective Refraction Test Using a Smartphone for Vision Screening
Published on: October 18, 2024
Screening for hyperopia in infants using the PowerRefractor
Nidhi G Satiani1, Donald O Mutti
1The Ohio State University College of Optometry, Columbus, Ohio, USA.

Insights
High hyperopia was detected in 7.5% of 2-month-old infants. Using accessory +4.50 D spectacles with the PowerRefractor improved detection accuracy compared to standard methods.
Area of Science:
- Ophthalmology
- Pediatric Optometry
- Refractive Error Assessment
Background:
- High hyperopia in infants can impact visual development.
- Accurate refractive error assessment is crucial in early childhood.
- The PowerRefractor (PR) is a handheld autorefractor used for infant eye exams.
Purpose of the Study:
- Determine the prevalence of high hyperopia in infants.
- Evaluate the PowerRefractor's ability to detect high hyperopia.
- Compare the PR with and without accessory lenses to cycloplegic retinoscopy.
Main Methods:
- 200 infants underwent cycloplegic retinoscopy and PowerRefractor (PR) examination.
- PR measurements were repeated with +4.50 D spectacles if initial readings were high.
- Examinations were performed during routine well-baby visits at 2 months of age.
Main Results:
- 7.5% of infants had spherical equivalent refractive error ≥ +5.00 D.
- The +4.50 D accessory spectacles significantly improved the PR's detection of high hyperopia.
- The PR with accessory glasses showed high sensitivity and specificity compared to retinoscopy.
Conclusions:
- Accessory +4.50 D spectacles effectively extend the PowerRefractor's range.
- The modified PR can accurately detect high hyperopia in 2-month-old infants.
- This method offers a viable alternative to cycloplegic retinoscopy for detecting significant hyperopia.
Purpose:
To determine the proportion of infants in a pediatric medical practice who have high levels of hyperopia in addition to evaluating the ability of the PowerRefractor (PR) [with and without accessory +4.50 diopter (D) spectacles] compared with cycloplegic retinoscopy to detect highly hyperopic refractive errors.
Methods:
The cycloplegic refractive error (2 drops tropicamide 1% given 5 min apart) of 200 normal birth weight infants was measured by retinoscopy and the Plusoptix PR. If initial readings were ≥ +2.00 D, PR measurement was repeated with accessory +4.50 D spectacles to extend its operating range. Examinations were conducted during well-baby visits at 2 months of age at the office of a local pediatrician group practice.
Results:
Of the 200 infants, 7.5% had a spherical equivalent refractive error of +5.00 D or more in both eyes. The use of +4.50 D accessory glasses during PowerRefraction significantly improved the ability to detect higher levels of hyperopia. Areas under receiver operating characteristic curves that were 0.69 to 0.51 when no glasses were worn improved to 0.87 to 0.98 when the glasses were worn (cutpoints between +3.50 and +5.00 D by retinoscopy). Significant underestimation of higher levels of hyperopia by the PR compared with retinoscopy was eliminated when +4.50 D accessory glasses were worn.
Conclusions:
Accessory +4.50 diopter sphere spectacles appeared to successfully extend the operating range of the PR with cycloplegia, allowing for detection of high levels of hyperopia that occurred in a large proportion of 2-month old infants with adequate sensitivity and specificity compared with cycloplegic retinoscopy.


