Related Experiment Video
Updated: Jun 1, 2026


Improved Renal Denervation Mitigated Hypertension Induced by Angiotensin II Infusion
Published on: May 26, 2022
Correction of iron deficiency in the cardiorenal syndrome
Donald S Silverberg1, Dov Wexler, Adrian Iaina
1Department of Nephrology, Tel Aviv Sourasky Medical Center, Weizman 6, Tel Aviv 64239, Israel.

Insights
Iron deficiency, common in heart failure and kidney disease, worsens outcomes. Treating iron deficiency with IV iron may improve cardiac function and quality of life, regardless of anemia status.
Area of Science:
- Cardiology
- Nephrology
- Metabolic Disorders
Background:
- Impaired energy metabolism is a hallmark of Congestive Heart Failure (CHF).
- Iron deficiency is prevalent in both Chronic Kidney Disease (CKD) and CHF, impacting cellular energy production.
- Emerging evidence indicates iron deficiency as an independent mortality risk factor in CHF.
Purpose of the Study:
- To evaluate the impact of correcting iron deficiency with intravenous (IV) iron on patients with CKD and CHF.
- To determine if improvements in cardiac function, exercise capacity, and quality of life are linked to iron status, independent of anemia.
Main Methods:
- Review of studies investigating IV iron therapy in CKD and CHF patients.
- Analysis of outcomes including anemia correction, renal function, cardiac function, exercise capacity, and quality of life.
Main Results:
- IV iron administration improved anemia and, in some cases, renal function in both CKD and CHF cohorts.
- CHF patients receiving IV iron showed enhanced cardiac function, structure, exercise capacity, and quality of life.
- These improvements were observed even in patients without anemia, suggesting iron deficiency's independent detrimental effect.
Conclusions:
- Correction of iron deficiency with IV iron shows promise in managing cardiorenal syndrome.
- Iron deficiency may independently contribute to the progression of CHF and CKD.
- Routine assessment of iron deficiency parameters in CKD and CHF patients, irrespective of anemia, is warranted.
Abstract:
Impaired energy metabolism is a feature of Congestive Heart Failure (CHF). Iron deficiency has been shown to reduce energy production in the cell in animals and humans. Iron deficiency is common in both Chronic Kidney Disease (CKD) and in CHF. Recent studies suggest that iron deficiency is an independent risk factor for mortality in CHF. Studies of correction of the anemia with intravenous (IV) iron in both CKD and CHF have shown an improvement in the anemia and, in some cases, in the renal function as well. Some CHF studies of correction of the iron deficiency have shown an improvement in cardiac function and structure as well as in exercise capacity and quality of life. This occurred independent of whether or not they had anemia, suggesting that the iron deficiency itself may be independently contributing to the worsening of the CHF and CKD. If future long-term studies confirm the safety and efficacy of IV iron in the treatment of iron deficiency in CKD and CHF, this will become a new addition to the therapeutic armamentarium of the cardiorenal syndrome, and parameters of iron deficiency will become part of the routine measurements performed in both CKD and CHF whether or not the patient is anemic.

Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:22
Heart Failure VI: Adjunct Therapies
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:29
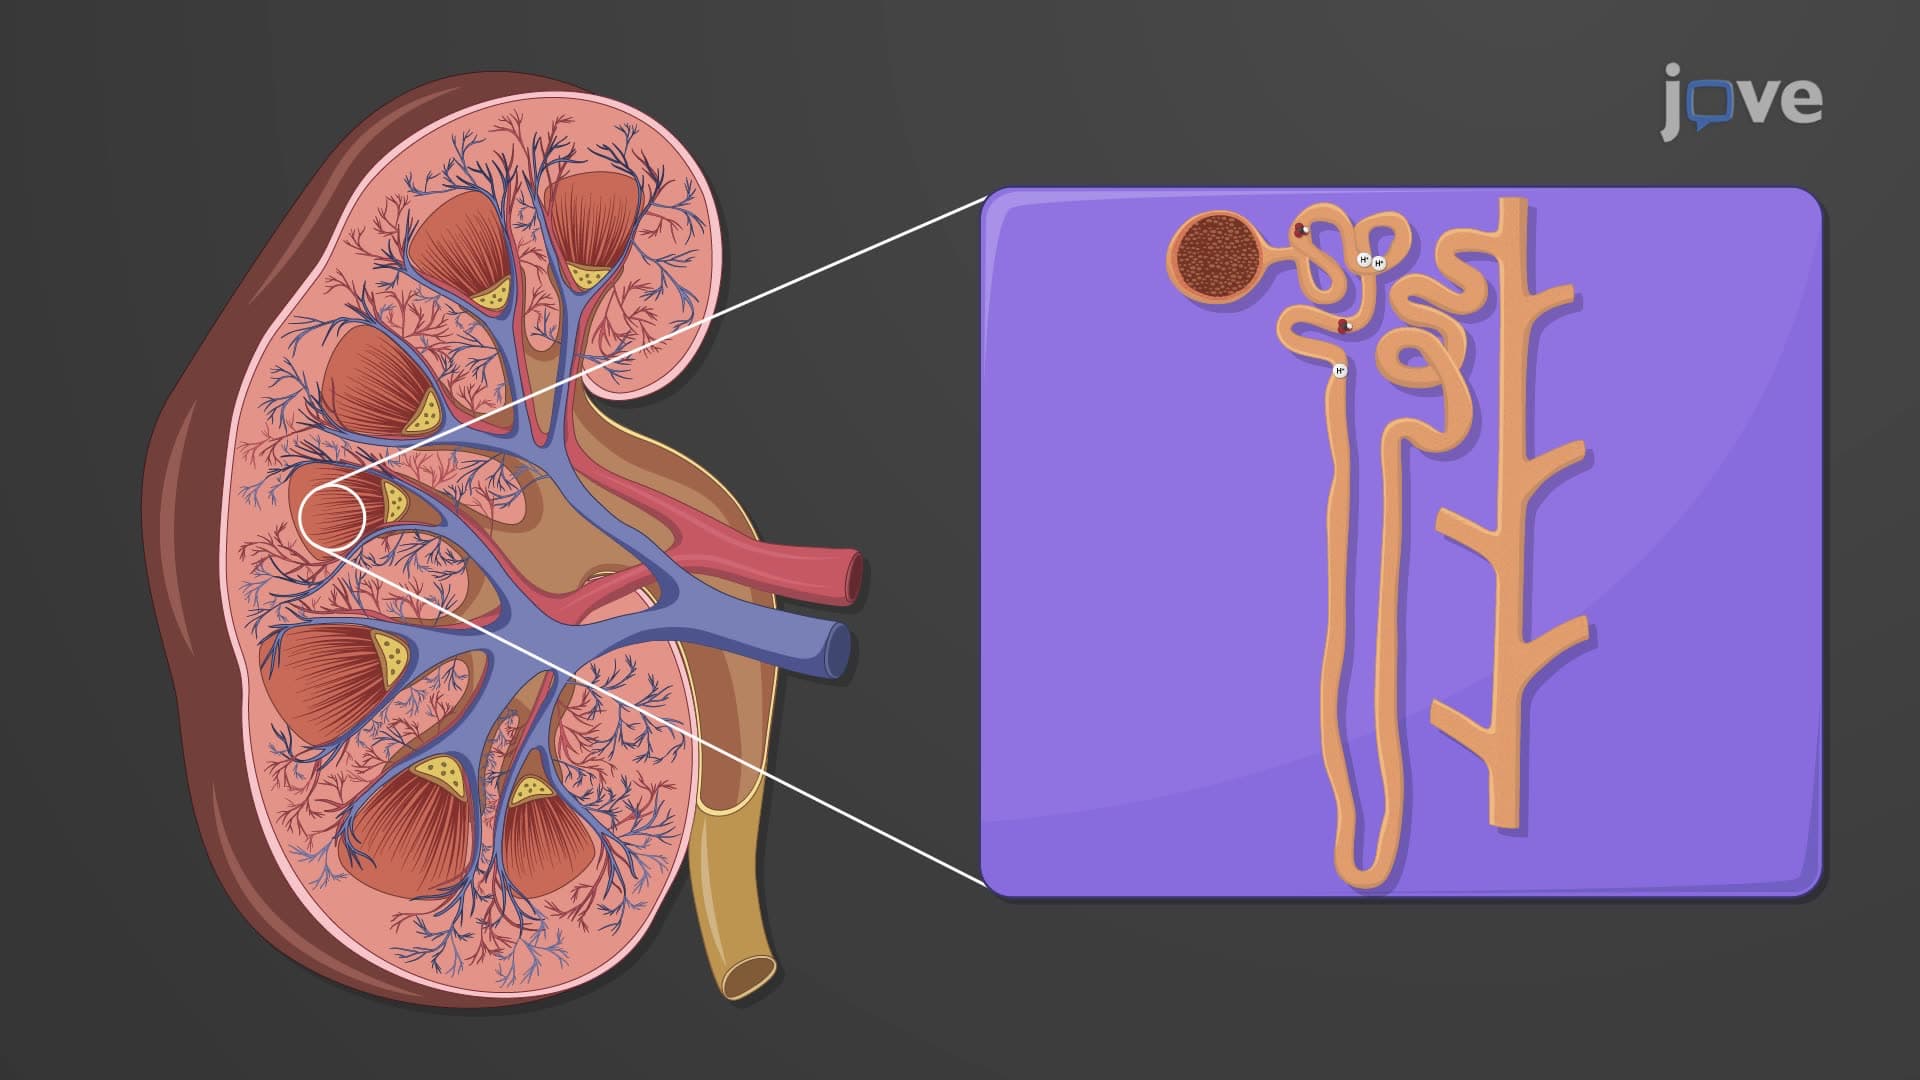
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:20
Acute Kidney Injury V: Interprofessional Care