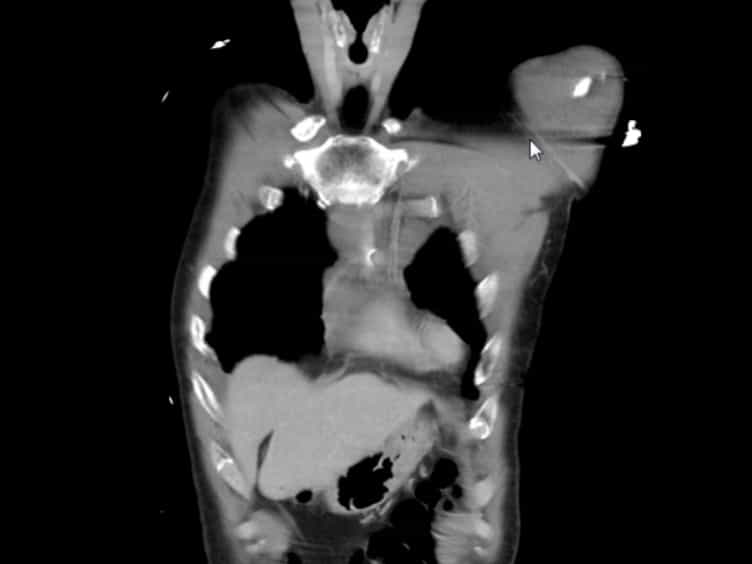
Progressive displacement of clavicular fractures in the early postinjury period
Elizabeth K Plocher1, Jack Anavian, Sandy Vang
1Department of Orthopaedic Surgery, State University of New York at Buffalo, Buffalo, New York, USA.

Background:
Historically, minimally to moderately displaced clavicular fractures have been managed nonoperatively. However, there is no clear evidence on whether clavicular fractures can progressively displace following injury and whether such displacement might influence decisions for surgery.
Methods:
We retrospectively reviewed data on 56 patients who received operative treatment for clavicular fractures at our institution from February 2002 to February 2007 and identified those patients who were initially managed nonoperatively based on radiographic evaluation (<2 cm displacement) and then subsequently went on to meet operative indications (≥2 cm displacement) as a result of progressive displacement. Standardized radiographic measurements for horizontal shortening (medial-lateral displacement) and vertical translation (cephalad-caudad displacement) were developed and used.
Results:
Fifteen patients with clavicle fractures initially displaced less than 2 cm and treated nonoperatively underwent later surgery because of progressive displacement (14 diaphyseal and 1 lateral). Radiographs performed during the injury workup and at a mean of 14.8 days postinjury demonstrated that progressive deformity had taken place. Ten of 15 patients (67%) displayed progressive horizontal shortening. Average change in horizontal shortening between that of the injury radiographs and the repeat radiographs in this group was 14.3 mm (5.9-29 mm). Thirteen of 15 patients (87%) displayed progressive vertical translation. Eight of 15 patients (53%) displayed both progressive horizontal shortening and vertical translation.
Conclusion:
We have demonstrated that a significant proportion of clavicle fractures (27% of our operative cases over a 5-year period) are minimally displaced at presentation, but are unstable and demonstrate progressive deformity during the first few weeks after injury. Because of this experience, we recommend close monitoring of nonoperatively managed clavicular fractures in the early postinjury period. A prudent policy is to obtain serial radiographic evaluation for 3 weeks, even for initially, minimally displaced clavicle fractures.

Related Concept Videos
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology