Ablation of atrial fibrillation: comparison of catheter-based techniques and the Cox-Maze III operation
Related Experiment Video
Updated: Jun 1, 2026
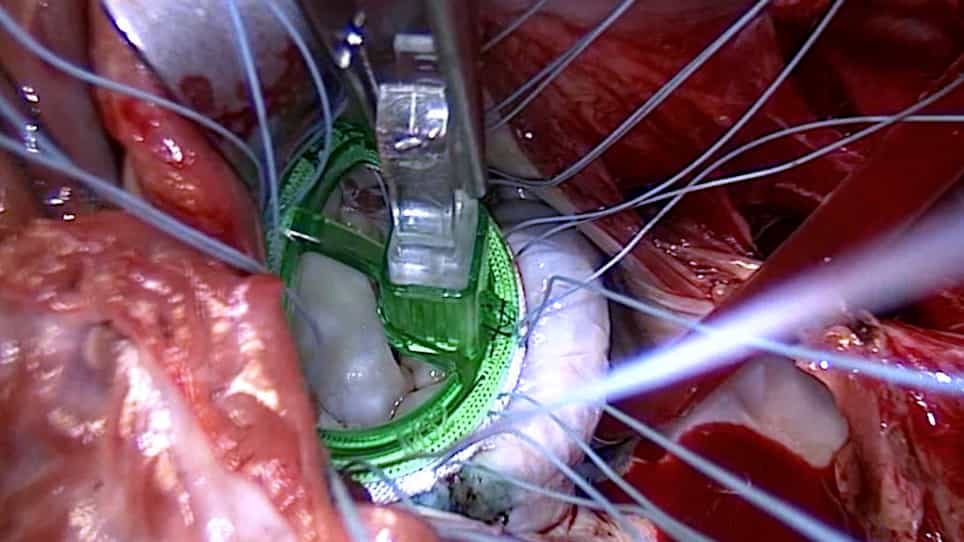
Cox-Maze IV Procedure Concomitant with Valvular Surgery In Situs Inversus Dextrocardia: A Single-Center Experience in China
Published on: February 11, 2022
John M Stulak1, Joseph A Dearani, Thoralf M Sundt
1Division of Cardiovascular Surgery, Mayo Clinic and Foundation, Rochester, Minnesota 55905, USA.

Insights
The Cox-Maze procedure offers superior long-term freedom from atrial fibrillation (AF) compared to catheter ablation. This surgical approach reduces the need for antiarrhythmic drugs and anticoagulation, improving patient outcomes.
Area of Science:
- Cardiology
- Cardiac Surgery
- Electrophysiology
Background:
- Catheter ablation is a common treatment for atrial fibrillation (AF), but its long-term effectiveness compared to surgical options is not well-established.
- Concerns exist regarding the transmurality of catheter ablation, potentially limiting its efficacy.
- Direct comparative data on late outcomes between surgical Cox-Maze and catheter ablation for AF are lacking.
Purpose of the Study:
- To compare the clinical outcomes of the cut-and-sew Cox-Maze procedure with catheter-based ablation for atrial fibrillation.
- To evaluate the long-term efficacy and need for medical management after both procedures.
Main Methods:
- A retrospective study matched 97 patients who underwent the Cox-Maze procedure with 194 patients who had catheter ablation for lone AF between 1993 and 2007.
- Patients were matched 1:2 based on age, sex, and AF type.
Main Results:
- At follow-up, 82% of Cox-Maze patients were AF-free and off medications versus 55% of ablation patients (p<0.001).
- Five-year freedom from AF was 87% for Cox-Maze versus 28% for ablation (p<0.001).
- Cox-Maze required less warfarin (12% vs 55%) and antiarrhythmic drugs (15% vs 68%) compared to ablation (p<0.001).
Conclusions:
- The Cox-Maze procedure demonstrates superior long-term efficacy in achieving freedom from atrial fibrillation compared to catheter ablation.
- Surgical ablation significantly reduces the need for subsequent antiarrhythmic drug therapy and warfarin anticoagulation.
- The Cox-Maze procedure offers a more durable solution for managing atrial fibrillation, with fewer patients requiring repeat interventions.
Background:
Catheter-based ablation is often recommended for treatment of atrial fibrillation (AF), but there are no data that directly compare late results to those of the Cox-Maze procedure. Although catheter ablation avoids operation, lack of reliable transmurality may reduce effectiveness. We compared clinical outcomes of the cut-and-sew Cox-Maze procedure with catheter ablation.
Methods:
Between January 1993 and October 2007, 97 patients aged 25 to 80 years underwent an isolated cut-and-sew Cox-Maze procedure. Patients were matched 1:2 according to age, sex, and AF type, with 194 patients undergoing catheter-based ablation for lone AF.
Results:
At last follow-up, 82% of patients who underwent the Cox-Maze procedure were free of AF and had stopped taking antiarrhythmic medications compared with 55% of patients who underwent ablation (p<0.001). When analyzed as a time-related event, freedom from recurrent AF was 87% 5 years after the Cox-Maze procedure compared with 28% after catheter ablation (p<0.001). Late warfarin anticoagulation was required in 12% of patients who underwent the Cox-Maze procedure compared with 55% of patients who underwent ablation (p<0.001), and use of antiarrhythmic medications during follow-up was significantly higher in patients who underwent ablation (68% versus 15%, p<0.001). Forty-one patients (24%) required repeated ablation procedure and 9 required a second repeated ablation.
Conclusions:
Compared with catheter-based ablation, the Cox-Maze procedure results in greater freedom from AF and less medical treatment with antiarrhythmic drugs and warfarin anticoagulation during follow-up.


