Related Experiment Video
Updated: Jun 1, 2026

Magnetic Resonance Derived Myocardial Strain Assessment Using Feature Tracking
Published on: February 12, 2011
Differences in cardiovascular risk profile between electrocardiographic hypertrophy versus strain in asymptomatic
Anders M Greve1, Eva Gerdts, Kurt Boman
1Department of Medicine B, The Heart Center, Rigshospitalet, Copenhagen, Denmark. greve_anders@hotmail.com

Insights
Electrocardiograms reveal that left ventricular hypertrophy and strain are linked to aortic stenosis severity. These findings clarify the clinical value of ECGs in managing aortic stenosis patients.
Area of Science:
- Cardiology
- Medical Imaging
- Clinical Research
Background:
- Electrocardiograms (ECGs) are standard for monitoring asymptomatic aortic stenosis (AS).
- The relationship between ECG findings, left ventricular (LV) response to pressure overload, and clinical factors in AS is not fully understood.
- The clinical utility of routine ECGs in AS management remains uncertain.
Purpose of the Study:
- To investigate the association between electrocardiographic criteria for LV hypertrophy and strain with AS severity and LV mass.
- To explore differences in clinical covariates among patients with varying ECG findings.
Main Methods:
- Analysis of data from 1,563 patients in the Simvastatin and Ezetimibe in Aortic Stenosis (SEAS) study.
- ECG data were Minnesota coded for arrhythmias and blocks; LV hypertrophy was assessed using Sokolow-Lyon and Cornell criteria.
- AS severity was measured by echocardiographic peak aortic jet velocity; LV mass was indexed by body surface area.
Main Results:
- Higher peak aortic jet velocity correlated with ECG strain and LV hypertrophy (Sokolow-Lyon criteria) after adjustments.
- Increased LV mass index was associated with ECG strain and both LV hypertrophy criteria after adjustments.
- ECG strain was linked to higher peak aortic jet velocity, blood glucose, and uric acid; LV hypertrophy criteria showed associations with age and gender.
Conclusions:
- ECG criteria for LV hypertrophy and strain are independently associated with AS severity (peak aortic jet velocity) and LV mass.
- Distinct clinical covariates are associated with ECG strain versus LV hypertrophy by Sokolow-Lyon and Cornell criteria.
- ECG findings provide valuable prognostic information in patients with aortic stenosis.
Abstract:
Electrocardiograms are routinely obtained in clinical follow-up of patients with asymptomatic aortic stenosis (AS). The association with aortic valve, left ventricular (LV) response to long-term pressure load, and clinical covariates is unclear and the clinical value is thus uncertain. Data from clinical examination, electrocardiogram, and echocardiogram in 1,563 patients in the Simvastatin and Ezetimibe in Aortic Stenosis (SEAS) study were used. Electrocardiograms were Minnesota coded for arrhythmias and atrioventricular and intraventricular blocks; LV hypertrophy was assessed by Sokolow-Lyon voltage and Cornell voltage-duration criteria; and strain by T-wave inversion and ST-segment depression. Degree of AS severity was evaluated by echocardiography as peak aortic jet velocity and LV mass was indexed by body surface area. After adjustment for age, gender, LV mass index, heart rate, systolic and diastolic blood pressures, blood glucose, digoxin, antiarrhythmic drugs, drugs acting on the renin-angiotensin system, diuretics, β blockers and calcium receptor blockers; peak aortic jet velocity was significantly greater in patients with electrocardiographic strain (mean difference 0.13 m/s, p <0.001) and LV hypertrophy by Sokolow-Lyon voltage criteria (mean difference 0.12 m/s, p = 0.004). After similar adjustment, LV mass index was significantly greater in patients with electrocardiographic strain (mean difference 14.8 g/cm(2), p <0.001) and LV hypertrophy by Sokolow-Lyon voltage criteria and Cornell voltage-duration criteria (mean differences 8.8 and 17.8 g/cm(2), respectively, p <0.001 for the 2 comparisons). In multiple comparisons patients with electrocardiographic strain had increased peak aortic jet velocity, blood glucose, and uric acid, whereas patients with LV hypertrophy by Sokolow-Lyon voltage criteria were younger and patients with LV hypertrophy by Cornell voltage-duration criteria more often were women. In conclusion, electrocardiographic criteria for LV hypertrophy and strain are independently associated with peak aortic jet velocity and LV mass index. Moreover, clinical covariates differ significantly between patients with electrocardiographic strain and those with LV hypertrophy by Sokolow-Lyon voltage criteria and Cornell voltage-duration criteria.
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:26
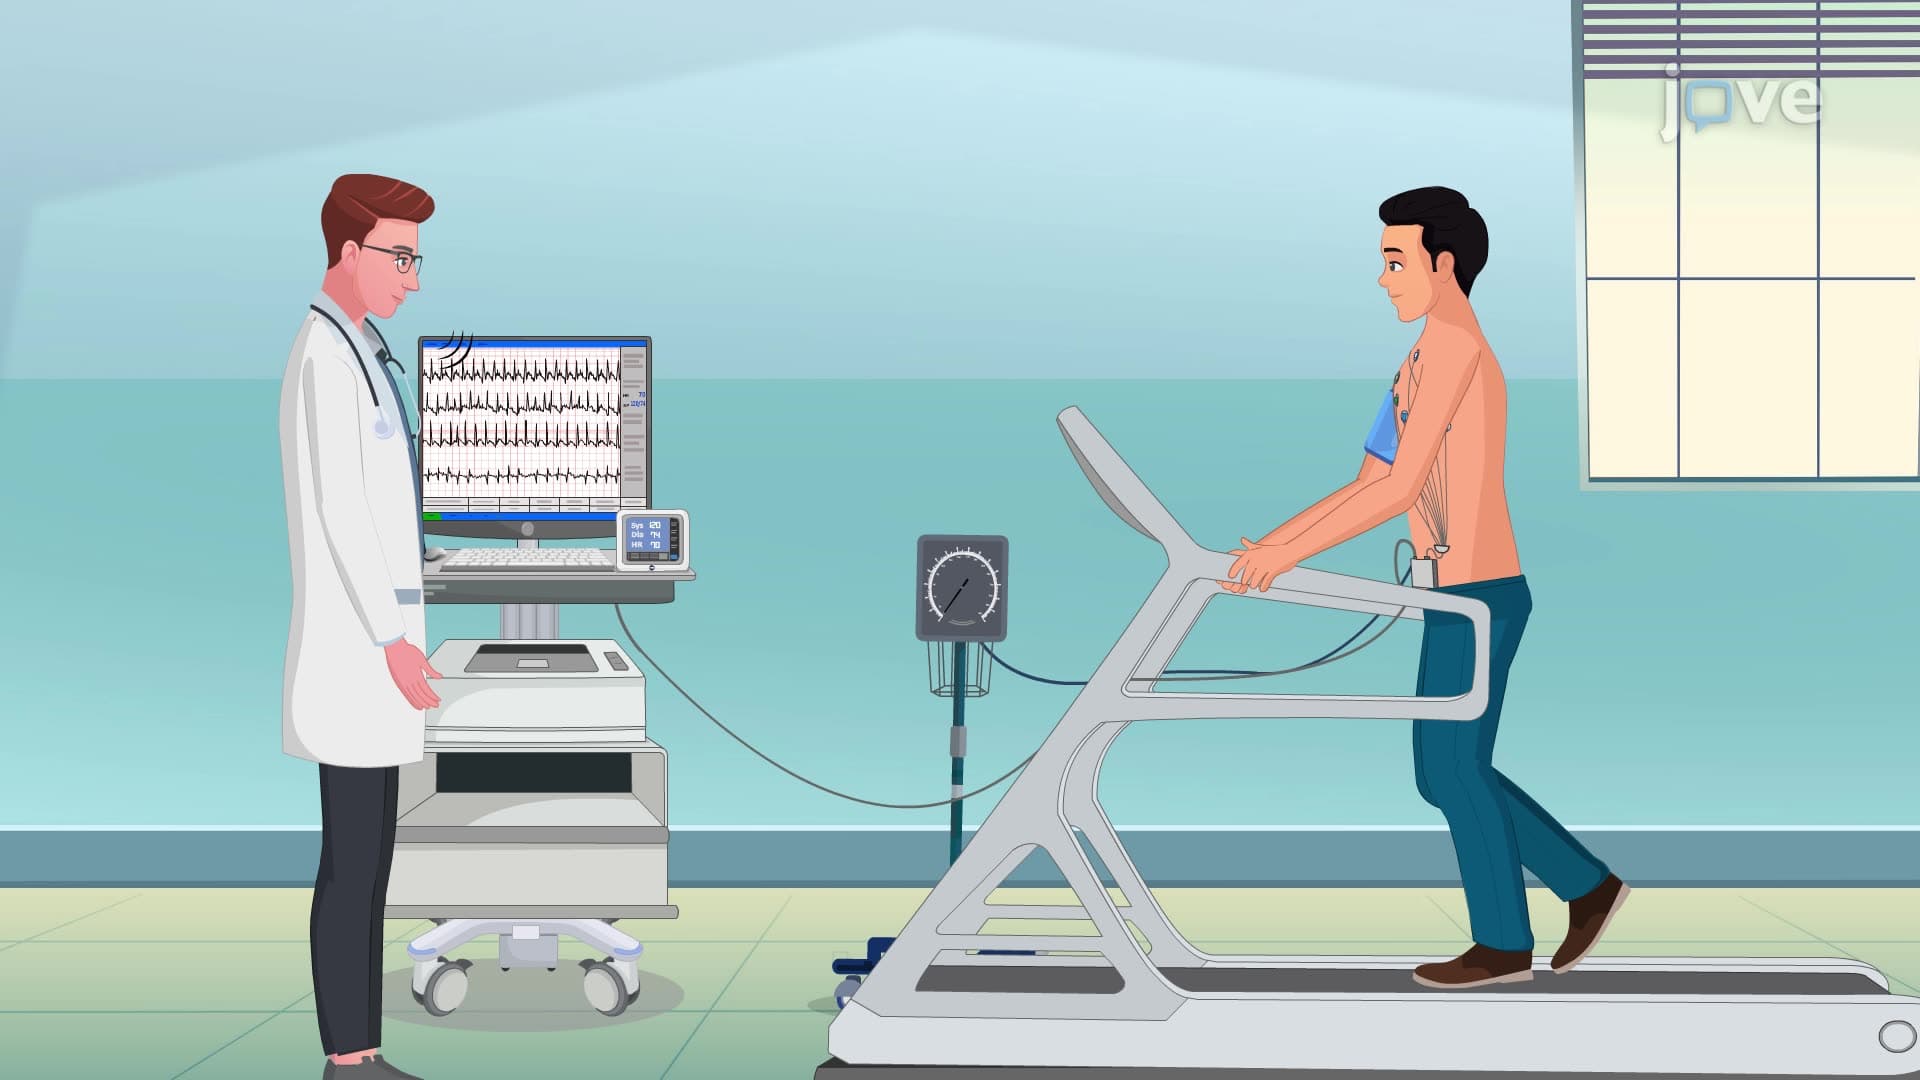
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies