Related Experiment Video
Updated: Jun 1, 2026
Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
Adenosine A2(A) receptor gene polymorphism (1976C>T) affects coronary flow reserve response during vasodilator stress
Maria Grazia Andreassi1, Franco Laghi Pasini, Eugenio Picano
1CNR, Institute of Clinical Physiology, Pisa, Italy. john.stapleton@ucl.ac.uk

Insights
Genetic variations in the A2(A) receptor gene, specifically the 1976C>T polymorphism, are linked to reduced coronary flow reserve in dilated cardiomyopathy patients. This finding impacts understanding of genetic influences on cardiac function during stress testing.
Area of Science:
- Cardiology
- Pharmacology
- Genetics
Background:
- Patients with non-ischemic dilated cardiomyopathy (DCM) exhibit an activated adenosinergic system and reduced coronary flow reserve (CFR).
- Adenosinergic stress, induced by dipyridamole, is used to evaluate CFR via Doppler echocardiography.
Purpose of the Study:
- To investigate the association between A2(A) receptor gene polymorphisms (263C>T and 1976C>T) and CFR response in DCM patients.
- To explore the impact of these genetic variants on A2(A) receptor protein expression.
Main Methods:
- Genotyping of A2(A) receptor polymorphisms (263C>T and 1976C>T) using polymerase chain reaction-restriction fragment length polymorphism analysis in 80 DCM patients and 162 controls.
- Assessment of Doppler-derived CFR in DCM patients during dipyridamole-induced adenosinergic stress.
- Evaluation of A2(A) receptor protein and mRNA expression in healthy controls.
Main Results:
- No significant difference in genotype distribution for either polymorphism between DCM patients and controls.
- Patients with the 1976TT genotype showed significantly lower CFR values compared to 1976CC patients.
- Increased A2(A) receptor protein expression was observed in controls with the T1976 allele (heterozygous or homozygous).
Conclusions:
- The A2(A) 1976C>T polymorphism is associated with a blunted coronary vasodilatory response in DCM patients.
- This single nucleotide polymorphism appears to directly influence A2(A) receptor protein expression.
- Further research is warranted to elucidate the functional role and clinical implications of this genetic variant in pharmacological stress cardiac imaging.
Objectives:
Patients with non ischemic-dilated cardiomyopathy (DCM) are characterized by an activation of the adenosinergic system and reduced coronary flow reserve (CFR) evaluated by transthoracic Doppler echocardiography during vasodilator adenosinergic stress (dipyridamole administration). The aim of this study was to assess whether genetic polymorphisms (263C>T and 1976C>T) of the A2(A) receptor gene affect CFR response in patients with DCM.
Methods:
We enrolled a group of 80 patients with DCM (55 male; age, 62±10.3 years) and 162 healthy volunteers (55 male; age, 45.1±9.5 years). Doppler-derived CFR (high-dose dipyridamole coronary diastolic peak flow velocity to resting coronary peak flow velocity ratio) of distal left anterior descending artery was determined in DCM. A2(A) receptor genotyping was determined in all patients by polymerase chain reaction-restriction fragment length polymorphism analysis. The expression of A2(A) protein and mRNA was also assessed in healthy controls.
Results:
The genotype distribution of the 263C>T (P=0.5) and 1976C>T (P=0.8) polymorphisms was not significantly different between patients and controls. Patients with 1976TT genotype had significantly lower CFR value than 1976CC patients (2.3±0.7, 2.0±0.5 and 1.9±0.4, P<0.05 for CC, CT and TT genotypes, respectively). Controls who were heterozygous (P=0.02) or homozygous (P=0.001) for the T1976 allele showed a significant increase in A2(A) receptor protein.
Conclusion:
These data demonstrate that A2(A) 1976C>T polymorphism is associated with a blunted coronary vasodilatory response in patients with DCM, and support a direct consequences of this single nucleotide polymorphism for protein expression. Additional studies are needed to better define the functional role of this genetic variant as well as to clarify the potential clinical impact of genetics during pharmacological stress cardiac imaging.
More Related Videos


Related Concept Videos
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase
 01:31
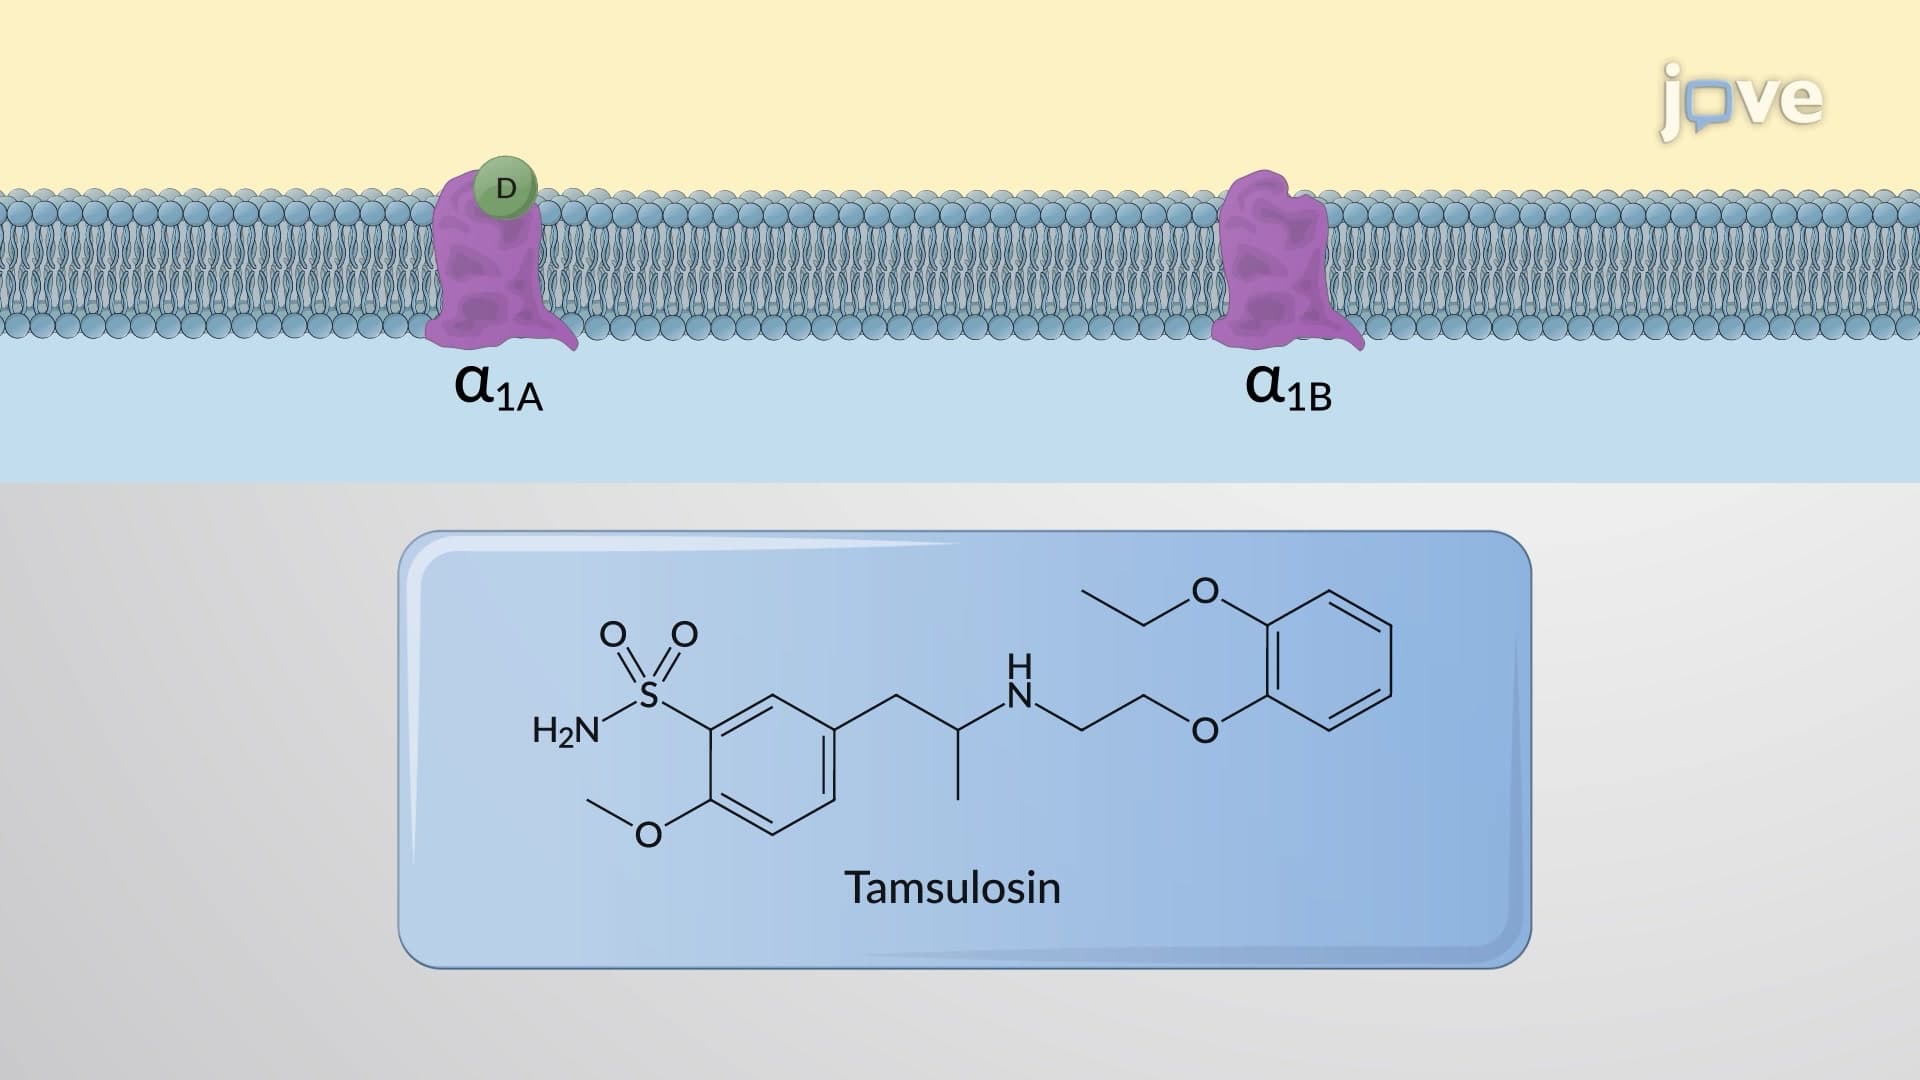
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
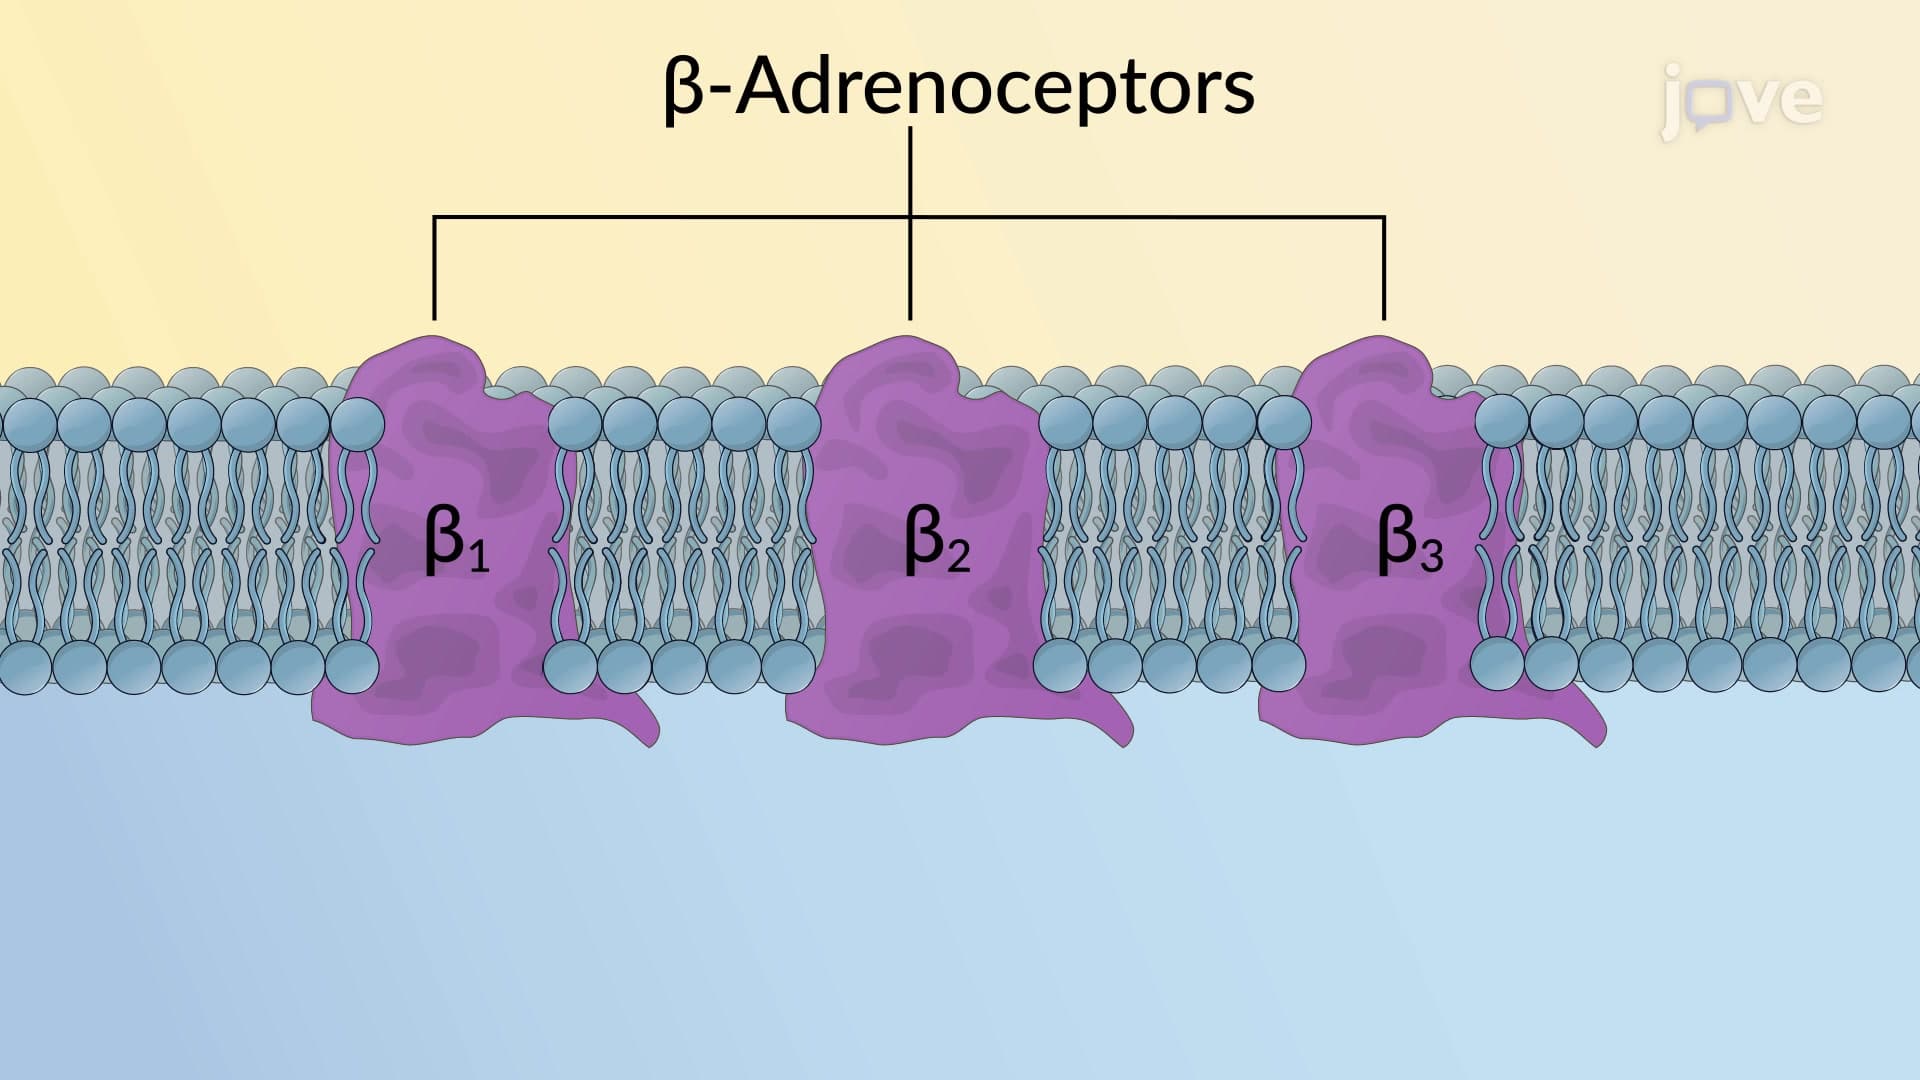
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
 01:29
Heart Failure II: Pathophysiology