Related Experiment Video
Updated: Jun 1, 2026
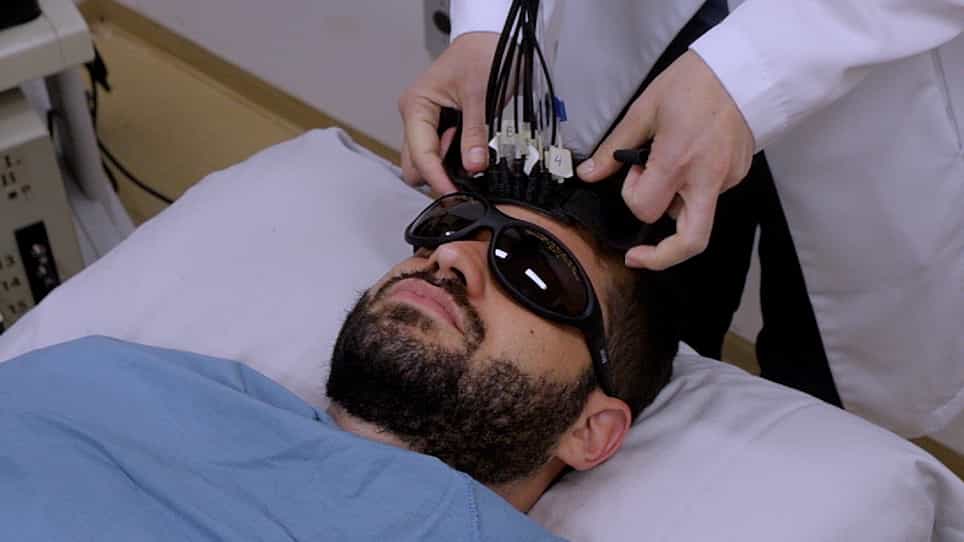

Real-Time Monitoring of Neurocritical Patients with Diffuse Optical Spectroscopies
Published on: November 19, 2020
Comparison between cerebral tissue oxygen tension and energy metabolism in experimental subdural hematoma
Troels Halfeld Nielsen1, Susanne I Engell, Rikke Aagaard Johnsen
1Department of Neurosurgery, Odense University Hospital, Sdr. Boulevard 29, 5000 Odense C, Denmark. troels.halfeld.nielsen@ouh.regionsyddanmark.dk

Background:
An experimental swine model (n = 7) simulating an acute subdural hematoma (ASDH) was employed (1) to explore the relation between the brain tissue oxygenation (PbtO(2)) and the regional cerebral energy metabolism as obtained by microdialysis, and (2) to define the lowest level of PbtO(2) compatible with intact energy metabolism.
Methods:
ASDH was produced by infusion of 7 ml of autologous blood (infusion rate 0.5 ml/min) by a catheter placed subdurally. PbtO(2) and microdialysis probes were placed symmetrically in the injured ("bad-side") and non-injured ("good-side") hemispheres. Intracranial pressure (ICP) was monitored in the "good-side."
Results:
ICP, cerebral perfusion pressure (CPP), PbtO(2), glucose, lactate, pyruvate, lactate-pyruvate ratio (LP ratio), glutamate, and glycerol were recorded at baseline (60 min) and post trauma (360 min). After the creation of the ASDH, PbtO(2) decreased significantly in both the hemispheres (P < 0.001). No significant difference was found between the sides post trauma. The LP ratio, glutamate, and glycerol in the "bad-side" increased significantly over the "good-side" where the values remained within the normal limits. A PbtO(2) value below approximately 25 mmHg was found to be associated with disturbed energy metabolism in the "bad-side" but not in the "good-side." No correlation was found between the LP ratio and PbtO(2) in either hemisphere.
Conclusions:
PbtO(2) monitoring accurately describes tissue oxygenation but does not disclose whether the oxygen delivery is sufficient for maintaining cerebral energy metabolism. Accordingly, it may not be possible to define a threshold level for PbtO(2) below which energy failure and permanent tissue damage occurs.
