Related Experiment Video
Updated: Jun 1, 2026


Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Physiologic decrease of ventilatory response to exercise in the second decade of life in healthy children
Alessandro Giardini1, Dolf Odendaal, Sachin Khambadkone
1Cardiorespiratory Unit, Great Ormond Street Hospital for Children, Great Ormond Street, London WC1N 3JH, UK. alessandro5574@iol.it

Insights
The ventilatory response to exercise, measured by the minute ventilation to carbon dioxide production (VE/VCO2) slope, decreases with age in children. Normative percentiles are essential for interpreting these exercise test results in adolescents.
Area of Science:
- Pediatric Cardiology
- Exercise Physiology
- Pulmonary Medicine
Background:
- Cardiopulmonary exercise testing (CPET) is vital for assessing children with congenital heart defects.
- Interpreting CPET results requires normative data, which are lacking for ventilatory responses in this population.
- There is a need for age-specific reference values for the ventilatory response to exercise in pediatric cardiology.
Purpose of the Study:
- To establish normative data for the ventilatory response to exercise in healthy children.
- To investigate the relationship between age, sex, and the VE/VCO2 slope in children.
- To provide gender-specific percentiles for VE/VCO2 slope to aid clinical interpretation.
Main Methods:
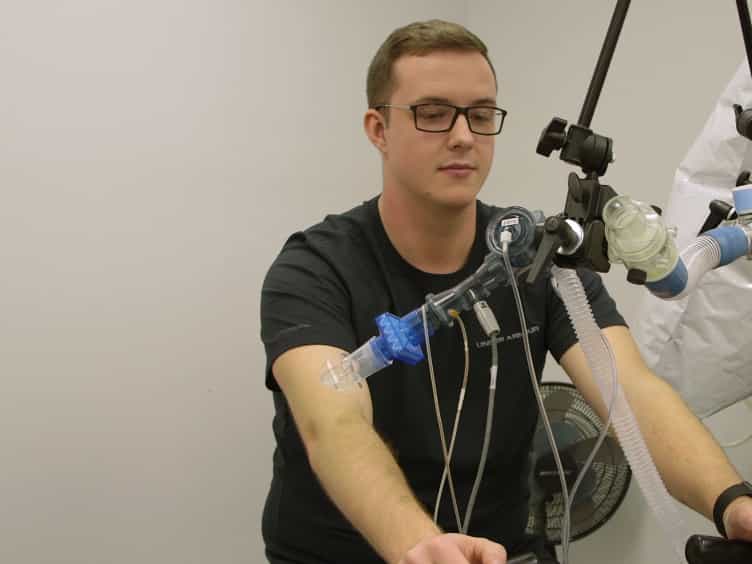
- Maximal cardiopulmonary exercise testing was performed on 243 healthy children (age 13.2 ± 2.1 years).
- The minute ventilation to carbon dioxide production (VE/VCO2) slope was calculated using data until respiratory compensation point (VE/VCO2RC) and peak exercise (VE/VCO2Peak).
- Gender-specific percentiles for VE/VCO2 slopes were derived from the study cohort.
Main Results:
- The VE/VCO2Peak slope averaged 28.2 ± 3.7, and VE/VCO2RC slope averaged 24.5 ± 3.0.
- A progressive decrease in both VE/VCO2 slopes was observed between ages 10 and 16 years, more pronounced in boys.
- Normal spirometry confirmed the absence of pulmonary limitations in the study group.
Conclusions:
- The VE/VCO2 slope declines with age during the second decade of life.
- Absolute VE/VCO2 slope values are less informative than age- and gender-specific percentiles for interpretation.
- These findings provide crucial normative data for evaluating ventilatory responses in pediatric exercise testing.
Background:
Cardiopulmonary exercise testing is increasingly used in children with congenital heart defects. Because of changes related to growth, the interpretation of exercise test results heavily relies on the presence of normative data. There is growing interest in the assessment of the ventilatory response to exercise in children with congenital heart disease, but normative data are lacking.
Methods:
We studied 243 consecutive children (age, 13.2 ± 2.1 years; 128 boys) with maximal cardiopulmonary exercise testing. All children had normal clinical examination and echocardiograms. In all children, the slope of the relationship between minute ventilation and carbon dioxide production (VE/VCO(2) slope) was calculated using both only data until the respiratory compensation point (VE/VCO(2RC)) and using data until peak exercise (VE/VCO(2Peak)).
Results:
The exercise test was maximal in all children (peak respiratory exchange ratio, 1.2 ± 0.1). For all the cohorts, VE/VCO(2Peak) slope was 28.2 ± 3.7; and VE/VCO(2RC) slope was 24.5 ± 3.0, whereas peak oxygen uptake was 94.6% ± 14.0% of predicted value. Baseline spirometric function was normal in all children (vital capacity, 100% ± 14% and forced expired volume in the first second 97% ± 13% of predicted). From the age of 10 to 16 years, we observed a progressive decrease in both VE/VCO(2Peak) and VE/VCO(2RC) slopes (-0.833 and -0.705 per each year), with the highest reduction observed in boys. Gender-specific percentiles for both VE/VCO(2Peak) and VE/VCO(2RC) slopes were constructed.
Conclusion:
Ventilatory response to exercise expressed as VE/VCO(2) slope seems to decrease progressively in the second decade of life. Because of age-related changes, interpretation of VE/VCO(2) slopes in this age range should be based on the reported percentiles rather than on the absolute values.
Related Concept Videos
 01:24
Factors Affecting Respiration
 01:17
Pulmonary Cycle: Exhalation
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:25
Hyperpnea and Hyperventilation
 01:22
Respiratory Volumes and Capacities
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...