Multidrug-resistant tuberculosis (MDR-TB) treatment in the UK: a study of injectable use and toxicity in practice
Related Experiment Video
Updated: Jun 1, 2026

System for Efficacy and Cytotoxicity Screening of Inhibitors Targeting Intracellular Mycobacterium tuberculosis
Published on: April 5, 2017
Ann Sturdy1, Anna Goodman, Ricardo J José
1Faculty of Medicine, Imperial College London, London SW7 2AZ, UK.

Background:
Multidrug-resistant tuberculosis (MDR-TB) is an increasing challenge to health services globally. Although new drugs are in development, current guidelines still recommend prolonged use of injectable antimicrobials (usually amikacin, kanamycin or capreomycin). The evidence base to inform treatment and monitoring strategies is very limited.
Methods:
We conducted a retrospective study of patients initiating injectable antimicrobials for MDR-TB treatment in five UK centres between January 2004 and December 2009. (i) Current treatment and monitoring strategies were reviewed. (ii) The incidence of ototoxicity (defined both clinically and on audiological testing) and factors associated with ototoxicity were investigated using logistic regression.
Results:
(i) The choice of injectable antimicrobial varied. Of 50 MDR-TB patients, 29/50 (58%) received amikacin, 11/50 (22%) received capreomycin and 10/50 (20%) received streptomycin or a combination; reflecting a difference in policy between centres. Only 21/50 (42%) patients received baseline screening by audiogram within 2 weeks of starting treatment and 16/50 (32%) then had monthly audiograms, with the majority screened more infrequently and 12/50 (24%) receiving no screening. (ii) Of the 50 patients, 14 (28%) experienced ototoxicity, with 9/50 (18%) left with long-term hearing loss. Increased age (P = 0.02), use of amikacin (P = 0.02) and decreased renal function (P = 0.01) were significantly associated with ototoxicity.
Conclusions:
There is local variation in both the choice of injectable agent and in ototoxicity screening practices. Long-term morbidity from injectable treatment is significant even in this well-resourced setting, and the data suggest capreomycin might be associated with less ototoxicity when compared with amikacin. There is a need for more high-quality clinical data to inform future guidelines for treatment and monitoring.

Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
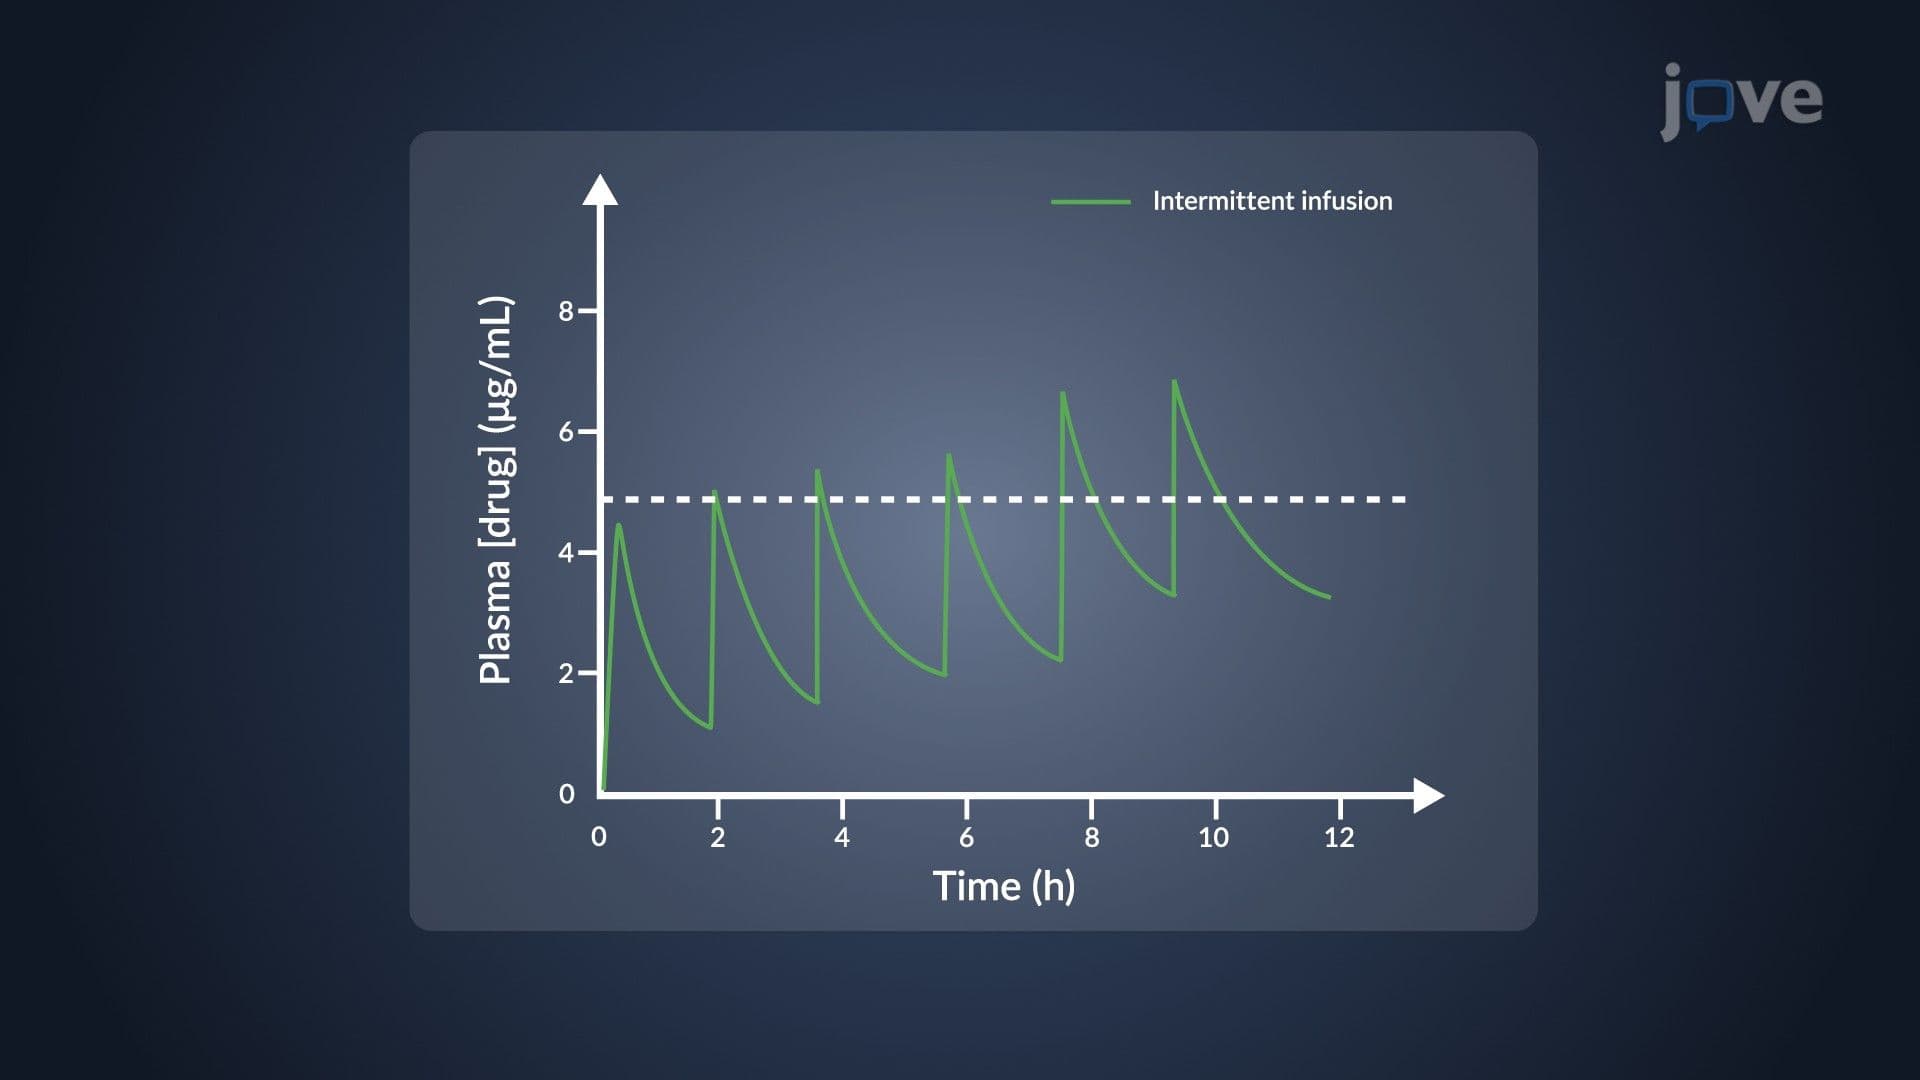 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions