Related Experiment Video
Updated: Jun 1, 2026

Measuring the Rate of Lipolysis in Ex Vivo Murine Adipose Tissue and Primary Preadipocytes Differentiated In Vitro
Published on: March 17, 2023
The pharmacology of adrenomedullin 2/intermedin
Yanguo Hong1, Debbie L Hay, Remi Quirion
1McGill University, Montreal, QC, Canada.

Abstract:
Adrenomedullin 2 (AM2) or intermedin is a member of the calcitonin gene-related peptide (CGRP)/calcitonin family of peptides and was discovered in 2004. Unlike other members of this family, no unique receptor has yet been identified for it. It is extensively distributed throughout the body. It causes hypotension when given peripherally, but when given into the CNS, it increases blood pressure and causes sympathetic activation. It also increases prolactin release, is anti-diuretic and natriuretic and reduces food intake. Whilst its effects resemble those of AM, it is frequently more potent. Some characterization of AM2 has been done on molecularly defined receptors; the existing data suggest that it preferentially activates the AM(2) receptor formed from calcitonin receptor-like receptor and receptor activity modifying protein 3. On this complex, its potency is generally equivalent to that of AM. There is no known receptor-activity where it is more potent than AM. In tissues and in animals it is frequently antagonised by CGRP and AM antagonists; however, situations exist in which an AM2 response is maintained even in the presence of supramaximal concentrations of these antagonists. Thus, there is a partial mismatch between the pharmacology seen in tissues and that on cloned receptors. The only AM2 antagonists are peptide fragments, and these have limited selectivity. It remains unclear as to whether novel AM2 receptors exist or whether the mismatch in pharmacology can be explained by factors such as metabolism.

Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:31
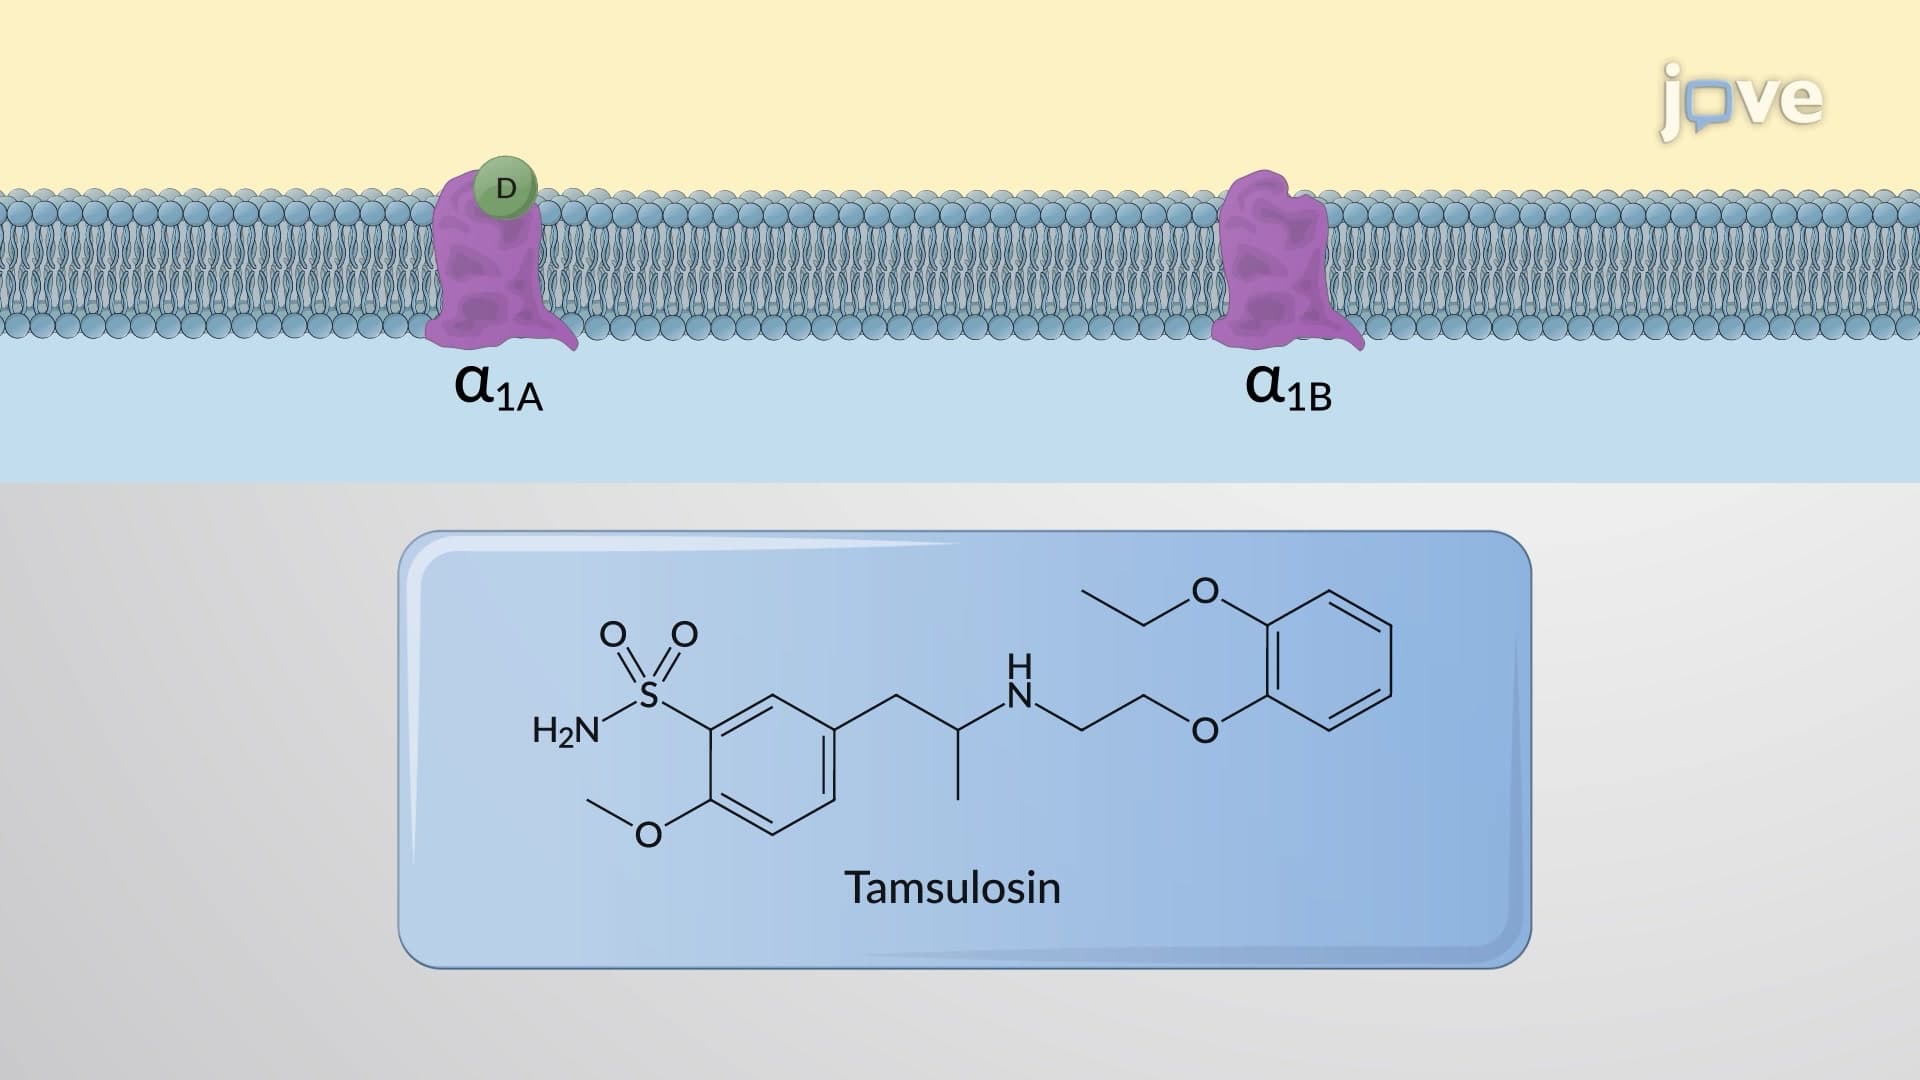
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
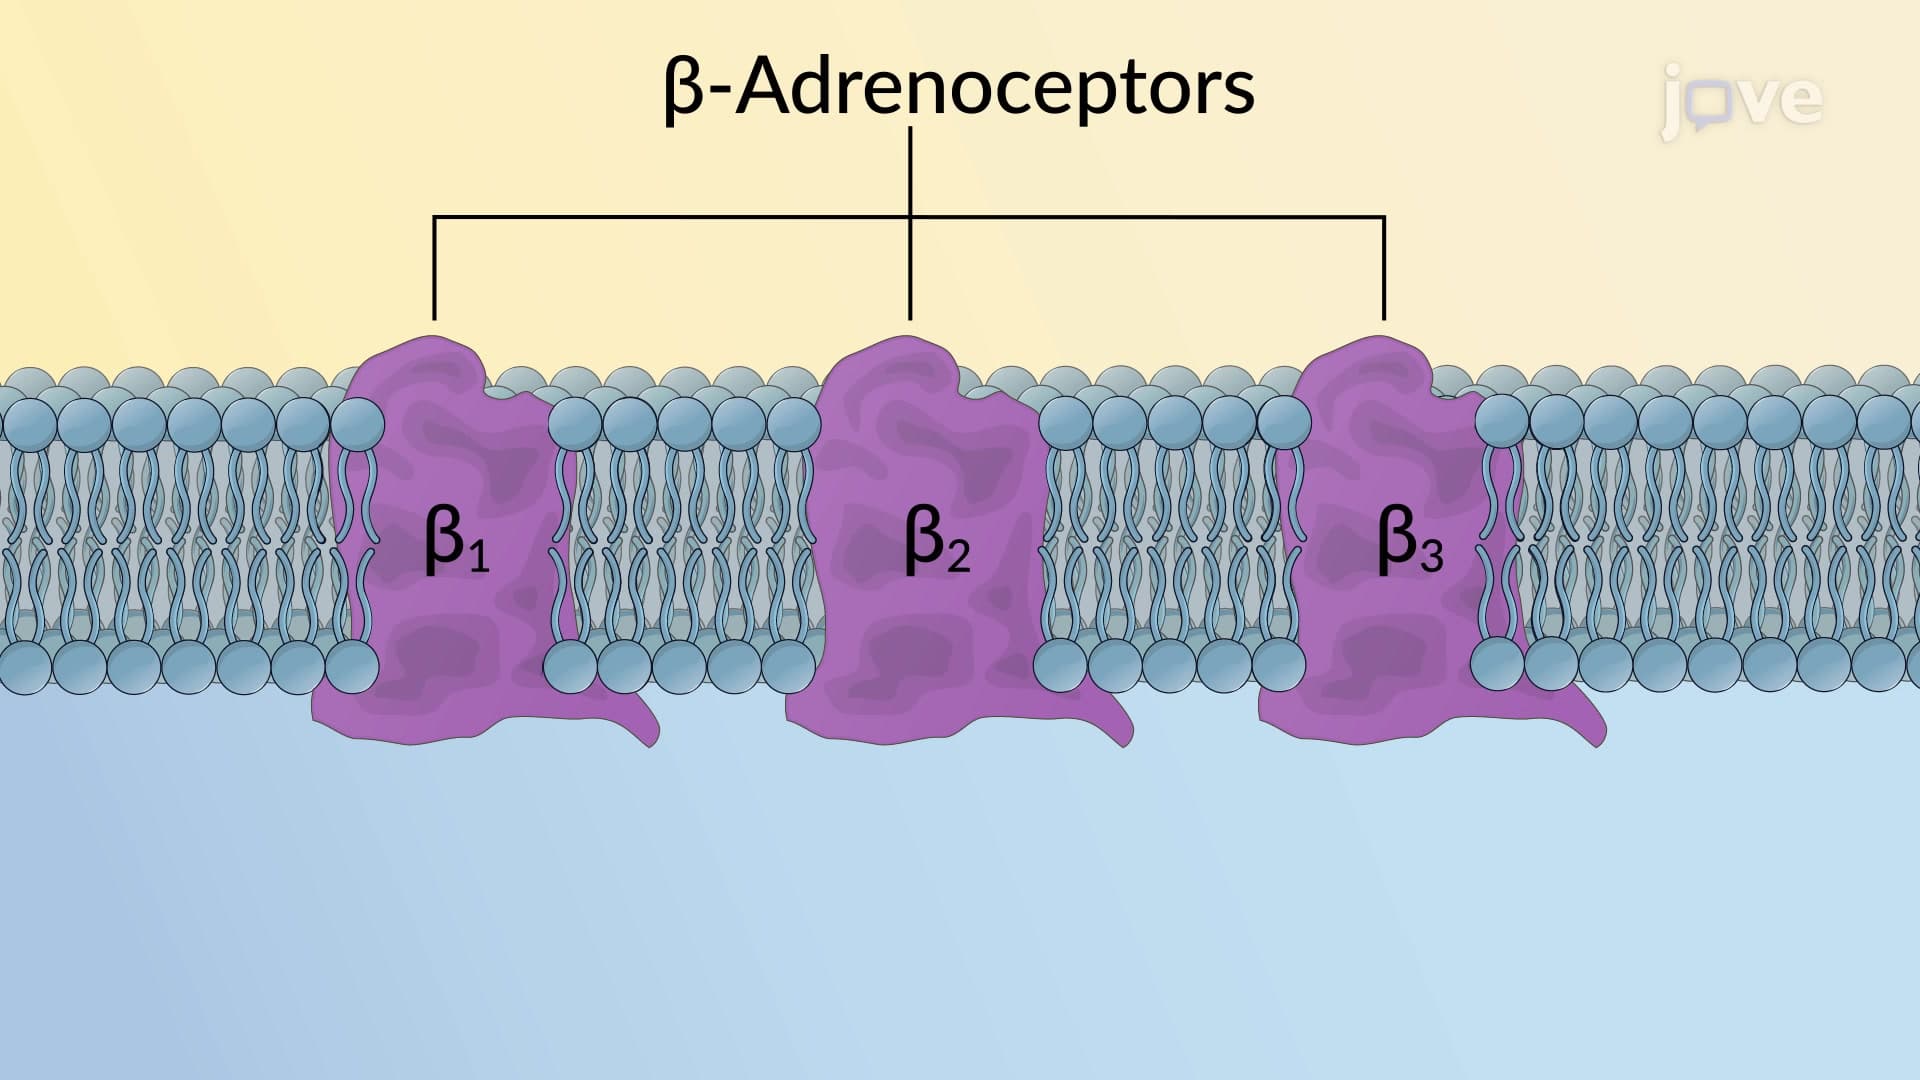
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:27
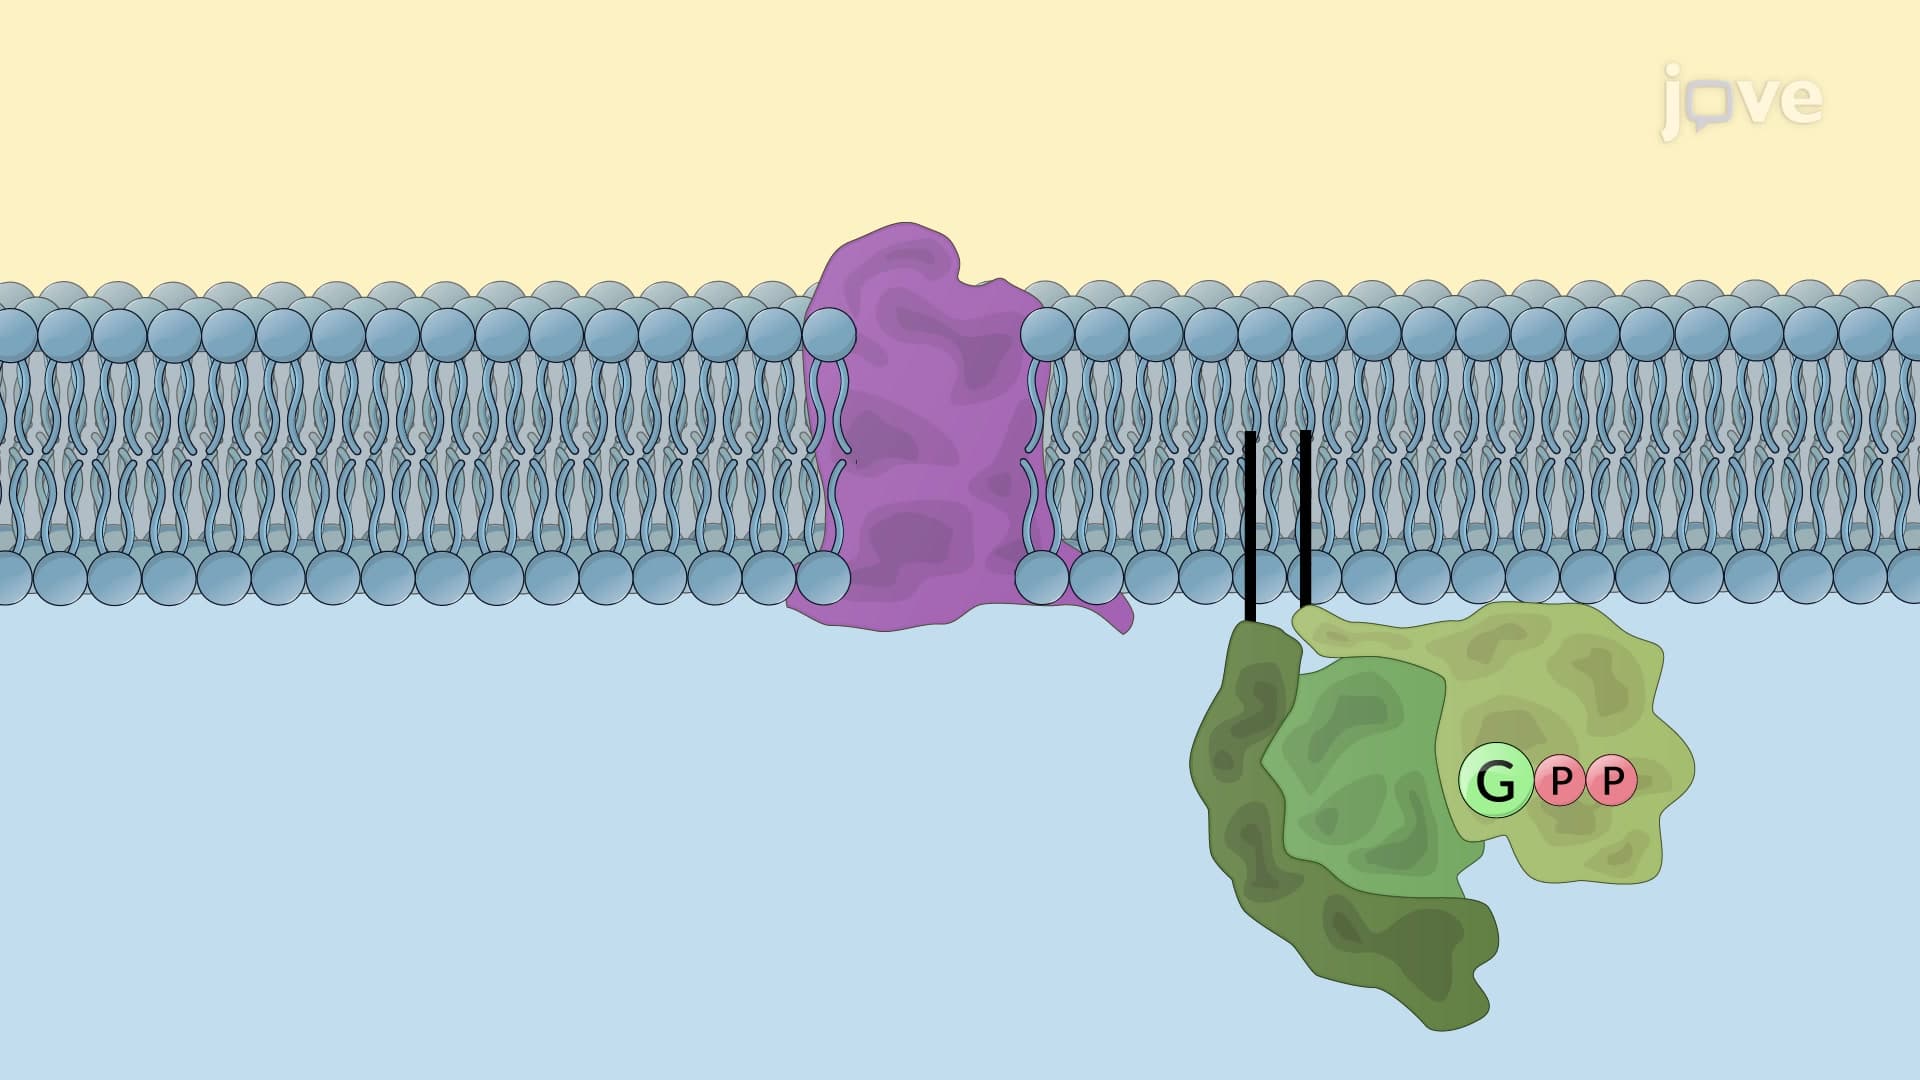
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:25
Adrenergic Agonists: Indirect-Acting Agents
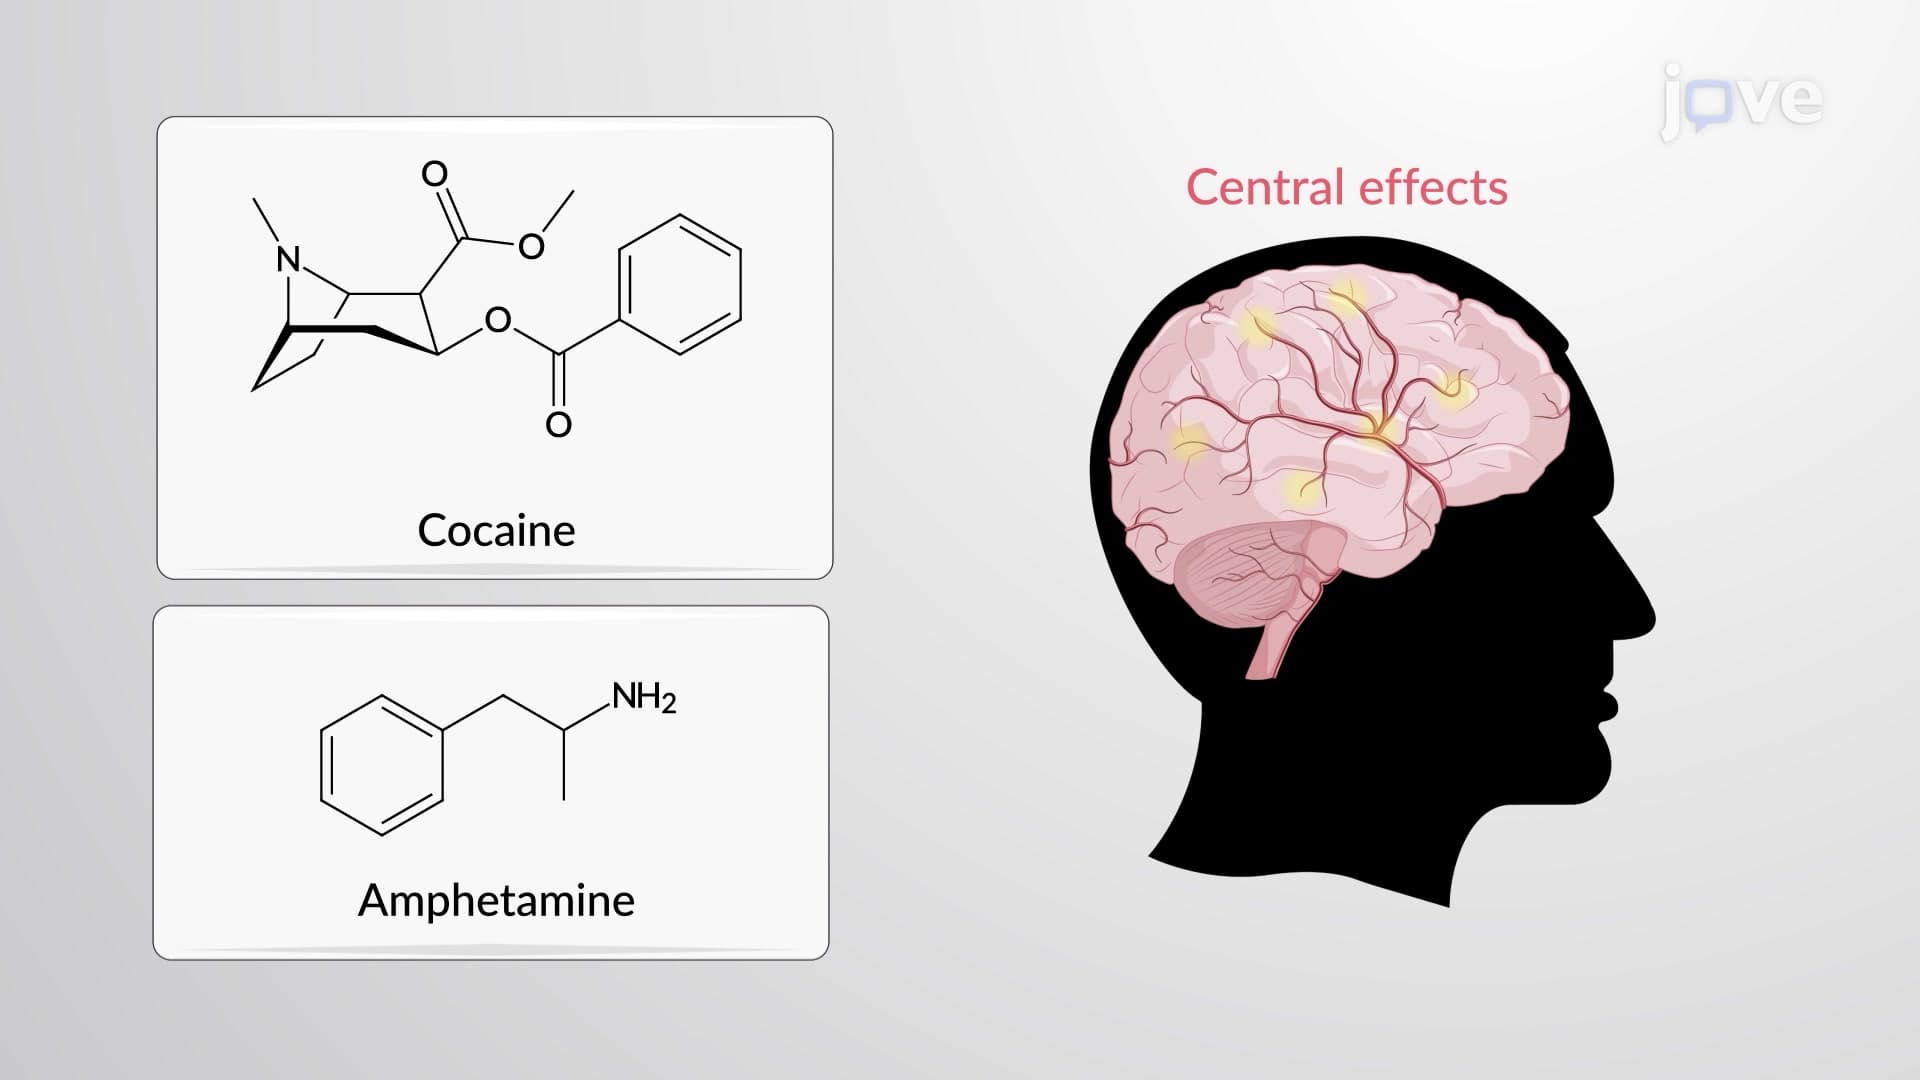
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...