Related Experiment Video
Updated: Jun 1, 2026


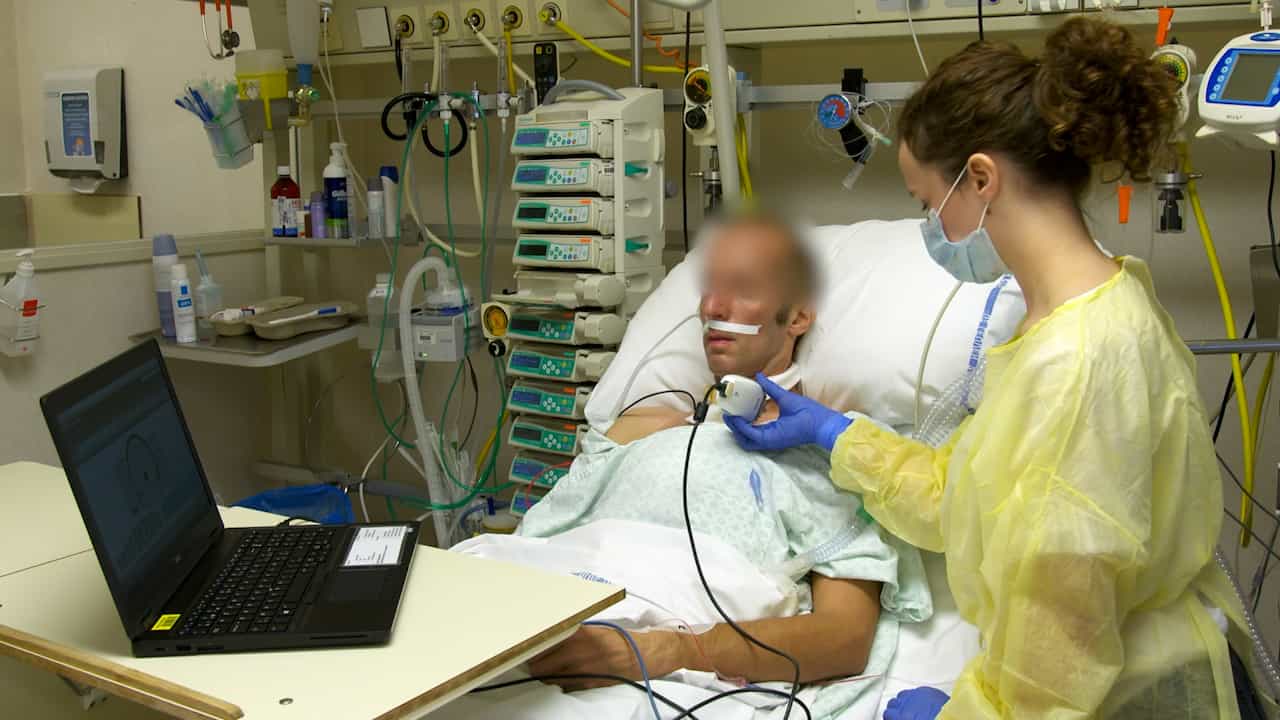
Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
A spontaneous breathing trial with pressure support overestimates readiness for extubation in children
Lee P Ferguson1, Brian K Walsh, Daphne Munhall
1Department of Anesthesia, Children's Hospital, Boston, MA, USA. lee.ferguson7@nuth.nhs.uk

Insights
A spontaneous breathing trial for pediatric extubation readiness may overestimate a child's ability to breathe independently, leading to higher failure rates. Objective data can help identify children who would benefit from noninvasive ventilation post-extubation.
Area of Science:
- Pediatric critical care medicine
- Respiratory physiology
- Mechanical ventilation
Background:
- Extubation readiness tests are crucial for determining when to discontinue mechanical ventilation in pediatric patients.
- Spontaneous breathing trials (SBTs) are commonly used to assess extubation readiness.
- Optimizing extubation success rates in pediatric intensive care units (PICUs) remains a significant clinical challenge.
Purpose of the Study:
- To evaluate the performance of an extubation readiness test utilizing a spontaneous breathing trial with pressure support in a pediatric intensive care unit.
- To assess the accuracy of this specific extubation readiness test in predicting successful extubation.
- To identify factors associated with extubation failure in intubated children.
Main Methods:
- A retrospective chart review was conducted in a pediatric intensive care unit.
- The study included infants and children requiring intubation between July 2007 and December 2008.
- An extubation readiness test using pressure support, adjusted for endotracheal tube size, was routinely employed.
Main Results:
- A total of 755 extubation readiness tests were performed on 538 patients, with an 83% pass rate.
- Among children who passed the test and were extubated without planned noninvasive ventilation, the extubation failure rate was 11.2%.
- Prolonged mechanical ventilation (over 48 hours) was significantly associated with extubation failure, irrespective of passing the readiness test, which was not a significant predictor of success.
Conclusions:
- The spontaneous breathing trial with pressure support, particularly with higher settings for smaller endotracheal tubes, may overestimate extubation readiness in children, increasing failure rates.
- Inadequate gas exchange due to lower respiratory tract dysfunction was a primary cause of extubation failure.
- Objective data from extubation readiness tests can aid in identifying pediatric patients who may benefit from transitioning to noninvasive ventilation.
Objective:
To evaluate the performance of an extubation readiness test based on a spontaneous breathing trial using pressure support.
Design:
Retrospective chart review.
Setting:
Pediatric intensive care unit.
Patients:
All infants and children admitted to the pediatric intensive care unit requiring intubation from July 2007 to December 2008 were eligible for this study.
Interventions:
Routine use of an extubation readiness test using pressure support set according to endotracheal tube size to determine completion of weaning and readiness for extubation.
Measurements And Main Results:
A total of 755 extubation readiness tests were performed in 538 patients with a pass rate of 83%. Of 500 children who passed the extubation readiness test and were extubated without planned noninvasive ventilation use, the extubation failure rate was 11.2% (5.8% required reintubation). Extubation failure was defined as need for noninvasive ventilation or reintubation within 24 hrs of planned extubation. Logistic regression analysis revealed a significant association between duration of mechanical ventilation and extubation failure. Children ventilated for over 48 hrs had an 18.5% failure rate despite passing an extubation readiness test before extubation and the extubation readiness test was not a significant predictor of extubation success. Most extubation failures were the result of inadequate gas exchange attributable to lower respiratory tract dysfunction.
Conclusions:
A spontaneous breathing trial using pressure support set at higher levels for smaller endotracheal tubes overestimates readiness for extubation in children and contributes to a higher failed extubation rate. The objective data obtained during an extubation readiness test may help to identify patients who will benefit from extubation to noninvasive ventilation.
Related Concept Videos
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:17
Pulmonary Cycle: Exhalation
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...