Related Experiment Video
Updated: Jun 1, 2026
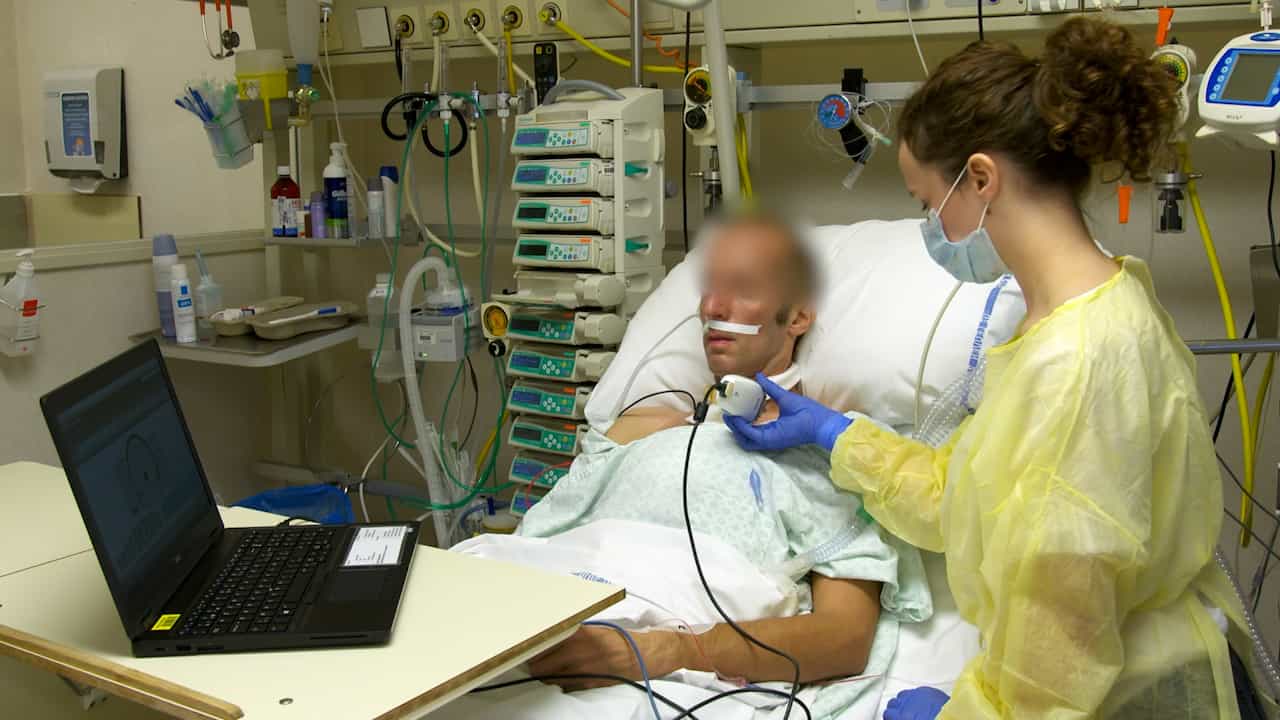
Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Increased protein-energy intake promotes anabolism in critically ill infants with viral bronchiolitis: a double-blind
Carlijn T de Betue1, Dick A van Waardenburg, Nicolaas E Deutz
1Department of Paediatrics, Maastricht University Medical Center, PO Box 5800, 6202 AZ Maastricht, The Netherlands.

Objective:
The preservation of nutritional status and growth is an important aim in critically ill infants, but difficult to achieve due to the metabolic stress response and inadequate nutritional intake, leading to negative protein balance. This study investigated whether increasing protein and energy intakes can promote anabolism. The primary outcome was whole body protein balance, and the secondary outcome was first pass splanchnic phenylalanine extraction (SPE(Phe)).
Design:
This was a double-blind randomised controlled trial. Infants (n=18) admitted to the paediatric intensive care unit with respiratory failure due to viral bronchiolitis were randomised to continuous enteral feeding with protein and energy enriched formula (PE-formula) (n=8; 3.1 ± 0.3 g protein/kg/24 h, 119 ± 25 kcal/kg/24 h) or standard formula (S-formula) (n=10; 1.7 ± 0.2 g protein/kg/24 h, 84 ± 15 kcal/kg/24 h; equivalent to recommended intakes for healthy infants <6 months). A combined intravenous-enteral phenylalanine stable isotope protocol was used on day 5 after admission to determine whole body protein metabolism and SPE(Phe).
Results:
Protein balance was significantly higher with PE-formula than with S-formula (PE-formula: 0.73 ± 0.5 vs S-formula: 0.02 ± 0.6 g/kg/24 h) resulting from significantly increased protein synthesis (PE-formula: 9.6 ± 4.4, S-formula: 5.2 ± 2.3 g/kg/24 h), despite significantly increased protein breakdown (PE-formula: 8.9 ± 4.3, S-formula: 5.2 ± 2.6 g/kg/24 h). SPE(Phe) was not statistically different between the two groups (PE-formula: 39.8 ± 18.3%, S-formula: 52.4 ± 13.6%).
Conclusions:
Increasing protein and energy intakes promotes protein anabolism in critically ill infants in the first days after admission. Since this is an important target of nutritional support, increased protein and energy intakes should be preferred above standard intakes in these infants. Dutch Trial Register number: NTR 515.
Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Overview of Protein Metabolism
Amino acids play various roles in the body once they are absorbed into cells. They are restructured...
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...