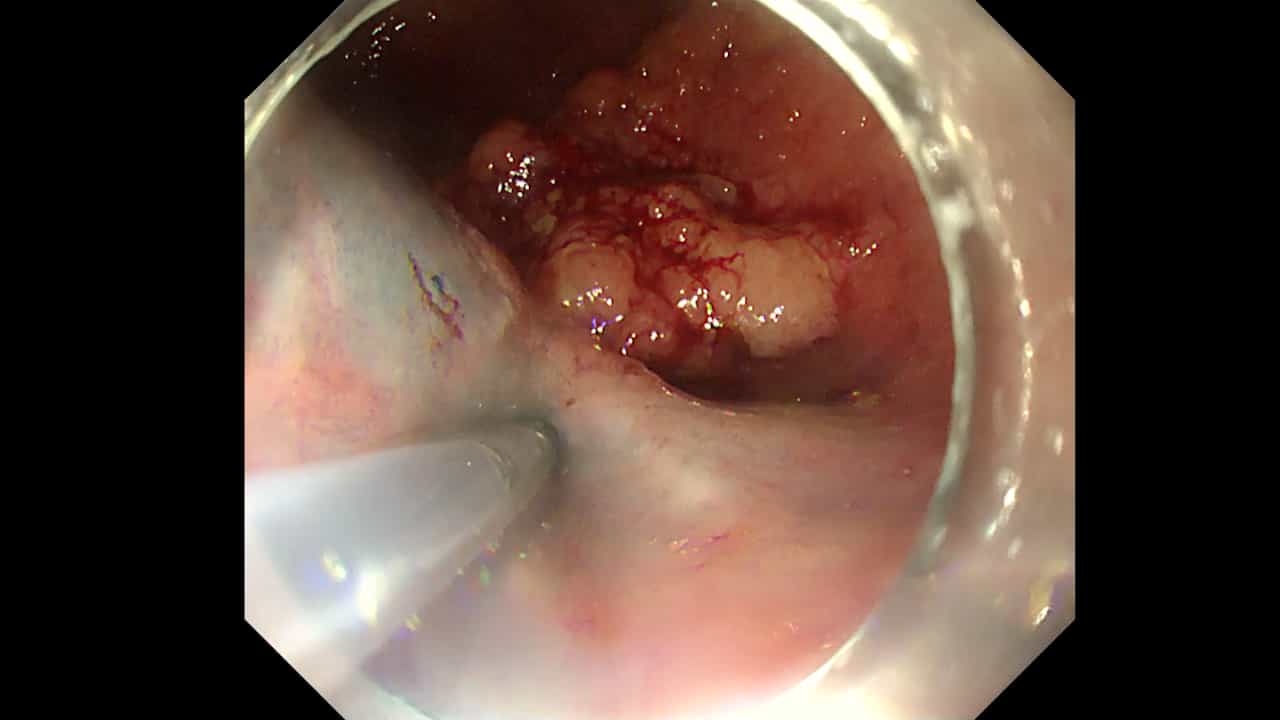
Related Experiment Video
Updated: May 31, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Transanal endoscopic microsurgery for T1 and T2 rectal cancers: a meta-analysis and meta-regression analysis of
George Sgourakis1, Sophocles Lanitis, Ines Gockel
1Second Surgical Department and Surgical Oncology Unit of Korgialenio - Benakio, Red Cross Hospital, Athens, Greece. ggsgourakis@yahoo.gr

Abstract:
The objective of this study is to assess transanal endoscopic microsurgery (TEM) as a surgical strategy for stage I rectal cancer. The literature lacks level I and level II evidence of the oncologic competence of TEM. Three randomized controlled, one prospective, and seven retrospective comparative studies were evaluated. End-points included perioperative outcomes, margin involvement, disease-free and overall survival, and recurrence. The number of patients with major (odds ratio (OR) = 0.24, 95% confidence interval (CI) 0.07-0.91) and overall postoperative complications (OR = 0.16, 95% CI 0.06-0.38) were significantly lower in TEM. The disease-free survival was higher in standard resection (SR) group compared with TEM (OR = 0.46, 95% CI 0.24-0.88). The number of patients with positive margins were less in the SR group (OR = 6.49, 95% CI 1.49-24.91), which was associated with lower local recurrence (OR = 4.92, 95% CI 1.81-13.41) and overall recurrence rate (OR = 2.03, 95% CI 1.15-3.57). No survival advantage was observed in favor of either procedure. TEM had lower rate of positive margins and longer disease-free survival when compared with transanal excision (TAE). TEM seems to be superior to SR concerning morbidity whilst less effective in obtaining negative surgical margins, and it is associated with higher local and overall recurrence. No survival advantage was observed in favor of either procedure. Unfavorable tumor preoperative histology does not seem to influence the selection between TEM and SR. TEM is more effective than TAE in obtaining negative surgical margins and shows a greater disease-free survival.
Insights
Transanal endoscopic microsurgery (TEM) offers lower complications for early rectal cancer but has higher recurrence rates than standard resection. Transanal endoscopic microsurgery (TEM) shows better disease-free survival than transanal excision (TAE).
Area of Science:
- Colorectal Surgery
- Surgical Oncology
- Minimally Invasive Procedures
Background:
- Stage I rectal cancer treatment requires oncologically sound strategies.
- Evidence for transanal endoscopic microsurgery (TEM) in early rectal cancer is limited.
- Comparative outcomes of TEM versus standard resection (SR) and transanal excision (TAE) need clarification.
Purpose of the Study:
- To evaluate transanal endoscopic microsurgery (TEM) for stage I rectal cancer.
- To compare TEM with standard resection (SR) and transanal excision (TAE) regarding oncologic outcomes and perioperative complications.
Main Methods:
- Systematic review and meta-analysis of randomized controlled trials, prospective, and retrospective comparative studies.
- Inclusion of 11 studies evaluating TEM versus SR and TAE.
- End-points: perioperative outcomes, margin status, disease-free survival, overall survival, and recurrence rates.
Main Results:
- TEM demonstrated significantly lower major and overall postoperative complications compared to SR.
- Standard resection (SR) was associated with a lower rate of positive margins and reduced local and overall recurrence.
- Transanal endoscopic microsurgery (TEM) showed improved disease-free survival and lower positive margin rates compared to transanal excision (TAE).
Conclusions:
- Transanal endoscopic microsurgery (TEM) offers reduced morbidity for stage I rectal cancer but is linked to higher recurrence rates than standard resection (SR).
- TEM is superior to transanal excision (TAE) in achieving negative margins and improving disease-free survival.
- No significant survival advantage was observed between TEM and SR; preoperative histology did not influence treatment selection.