Related Experiment Video
Updated: May 31, 2026


Simultaneous Laryngopharyngeal and Conventional Esophageal pH Monitoring
Published on: December 14, 2020
Distal esophageal spasm in high-resolution esophageal pressure topography: defining clinical phenotypes
John E Pandolfino1, Sabine Roman, Dustin Carlson
1Department of Medicine, The Feinberg School of Medicine, Northwestern University, Chicago, Illinois 60611-2951, USA. j-pandolfino@northwestern.edu

Background:
The manometric diagnosis of distal esophageal spasm (DES) uses "simultaneous contractions" as a defining criterion, ignoring the concept of short latency distal contractions as an important feature. Our aim was to apply standardized metrics of contraction velocity and latency to high-resolution esophageal pressure topography (EPT) studies to refine the diagnosis of DES.
Methods:
Two thousand consecutive EPT studies were analyzed for contractile front velocity (CFV) and distal latency to identify patients potentially having DES. Normal limits for CFV and distal latency were established from 75 control subjects. Clinical data of patients with reduced distal latency and/or rapid CFV were reviewed.
Results:
Of 1070 evaluable patients, 91 (8.5%) had a high CFV and/or low distal latency. Patients with only rapid contractions (n = 186 [17.4%] using conventional manometry criteria; n = 85 [7.9%] using EPT criteria) were heterogeneous in diagnosis and symptoms, with the majority ultimately categorized as weak peristalsis or normal. In contrast, 96% of patients with premature contraction had dysphagia, and all (n = 24; 2.2% overall) were ultimately managed as spastic achalasia or DES.
Conclusions:
The current DES diagnostic paradigm focused on "simultaneous contractions" identifies a large heterogeneous set of patients, most of whom do not have a clinical syndrome suggestive of esophageal spasm. Incorporating distal latency into the diagnostic algorithm of EPT studies improves upon this by isolating disorders of homogeneous pathophysiology: DES with short latency and spastic achalasia. We hypothesize that prioritizing measurement of distal latency will refine the management of these disorders, recognizing that outcomes trials are necessary.


Related Concept Videos
 01:27
Esophageal Achalasia
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:25
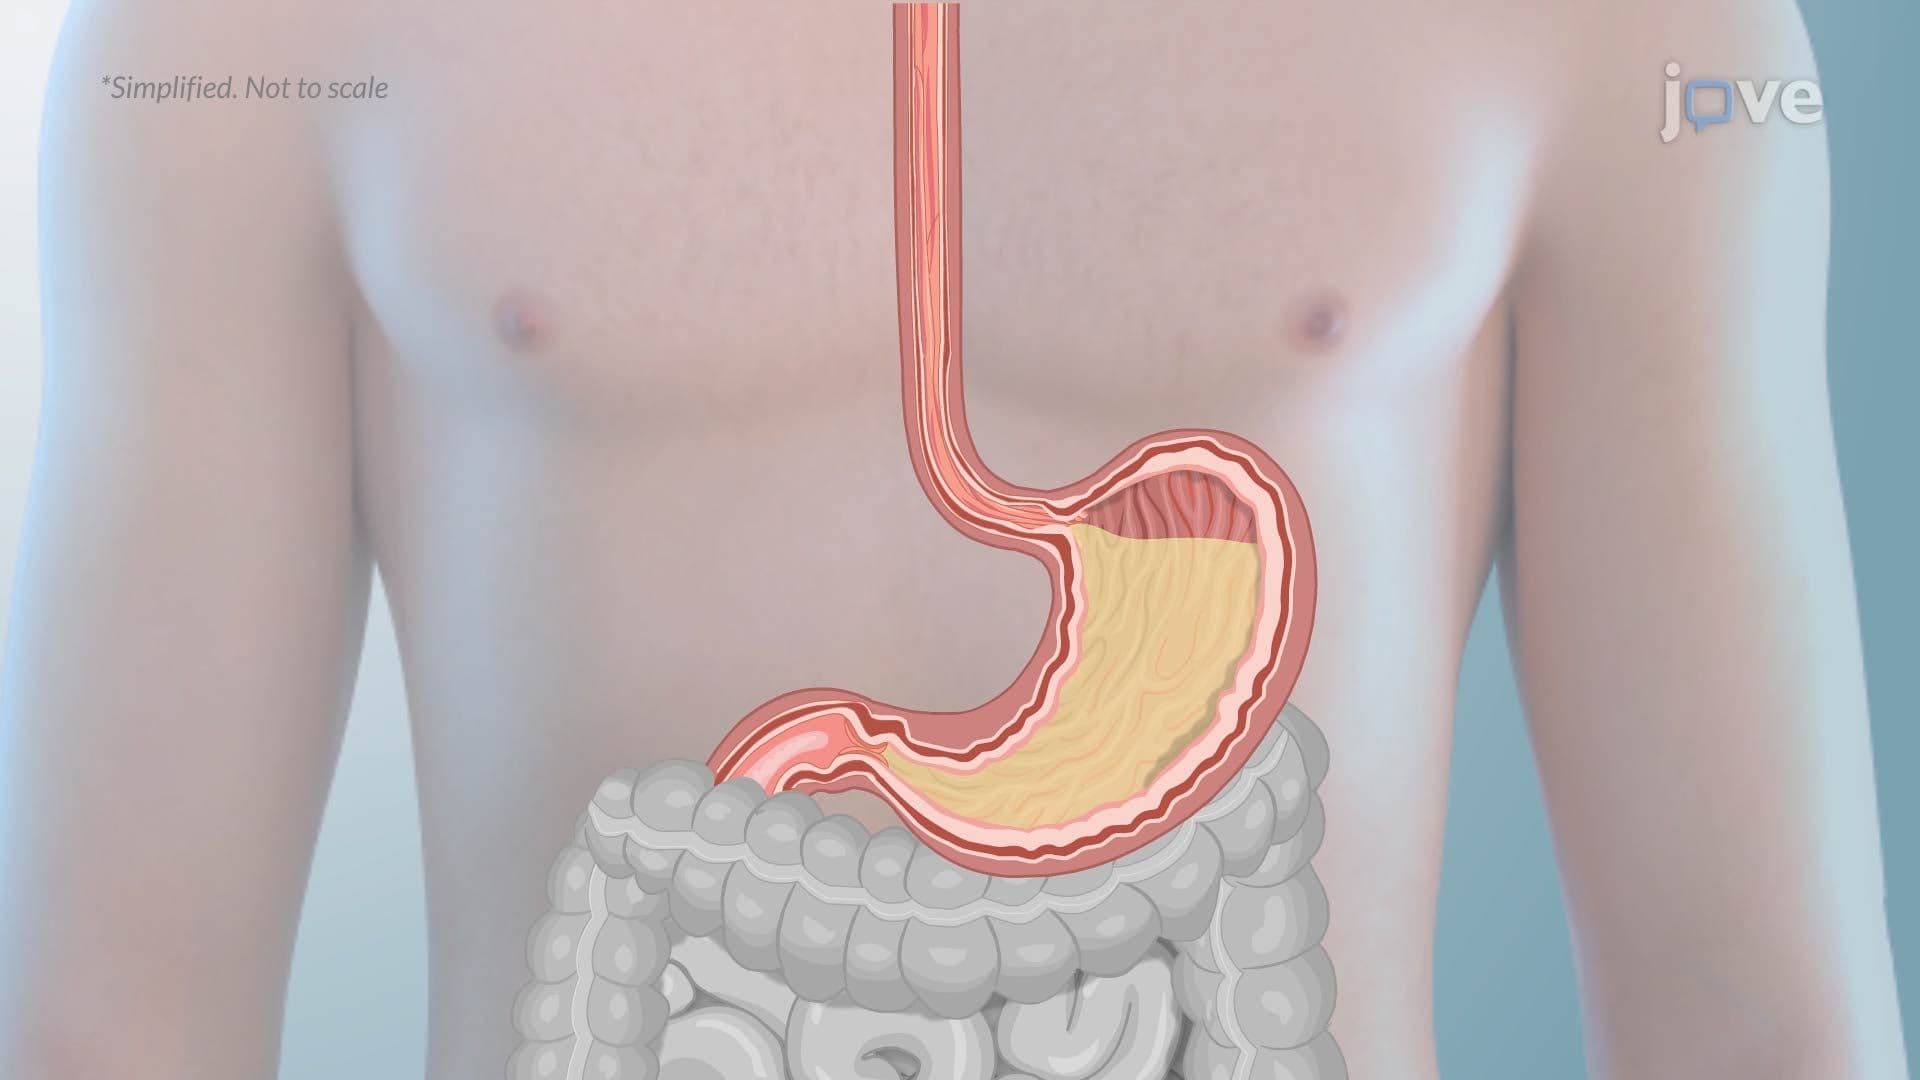
Gastroesophageal Reflux Disease
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...