Related Experiment Video
Updated: May 31, 2026


Dissection and Flat-mounting of the Threespine Stickleback Branchial Skeleton
Published on: May 7, 2016
Branchial anomalies in children
Y Bajaj1, S Ifeacho, D Tweedie
1Department of Otolaryngology, Great Ormond Street Hospital, Great Ormond Street, London LS17 7WA, United Kingdom. ybajaj@hotmail.co.uk

Background:
Branchial cleft anomalies are the second most common head and neck congenital lesions seen in children. Amongst the branchial cleft malformations, second cleft lesions account for 95% of the branchial anomalies. This article analyzes all the cases of branchial cleft anomalies operated on at Great Ormond Street Hospital over the past 10 years.
Methods:
All children who underwent surgery for branchial cleft sinus or fistula from January 2000 to December 2010 were included in this study.
Results:
In this series, we had 80 patients (38 female and 42 male). The age at the time of operation varied from 1 year to 14 years. Amongst this group, 15 patients had first branchial cleft anomaly, 62 had second branchial cleft anomaly and 3 had fourth branchial pouch anomaly. All the first cleft cases were operated on by a superficial parotidectomy approach with facial nerve identification. Complete excision was achieved in all these first cleft cases. In this series of first cleft anomalies, we had one complication (temporary marginal mandibular nerve weakness. In the 62 children with second branchial cleft anomalies, 50 were unilateral and 12 were bilateral. In the vast majority, the tract extended through the carotid bifurcation and extended up to pharyngeal constrictor muscles. Majority of these cases were operated on through an elliptical incision around the external opening. Complete excision was achieved in all second cleft cases except one who required a repeat excision. In this subgroup, we had two complications one patient developed a seroma and one had incomplete excision. The three patients with fourth pouch anomaly were treated with endoscopic assisted monopolar diathermy to the sinus opening with good outcome.
Conclusion:
Branchial anomalies are relatively common in children. There are three distinct types, first cleft, second cleft and fourth pouch anomaly. Correct diagnosis is essential to avoid inadequate surgery and multiple procedures. The surgical approach needs to be tailored to the type of anomaly of origin of the anomaly. Complete excision is essential for good outcomes.


Related Concept Videos
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:07
Development of the Limb Synovial Joints
The mesenchymal stem cells differentiate into chondrocytes that form the hyaline cartilage, and later the cartilaginous model of the bone. This model further transforms into a bone. This process is known as endochondral ossification.
During development, the limbs...
 01:30
Neurulation
 01:12
Arteries of the Upper Limbs
 01:09
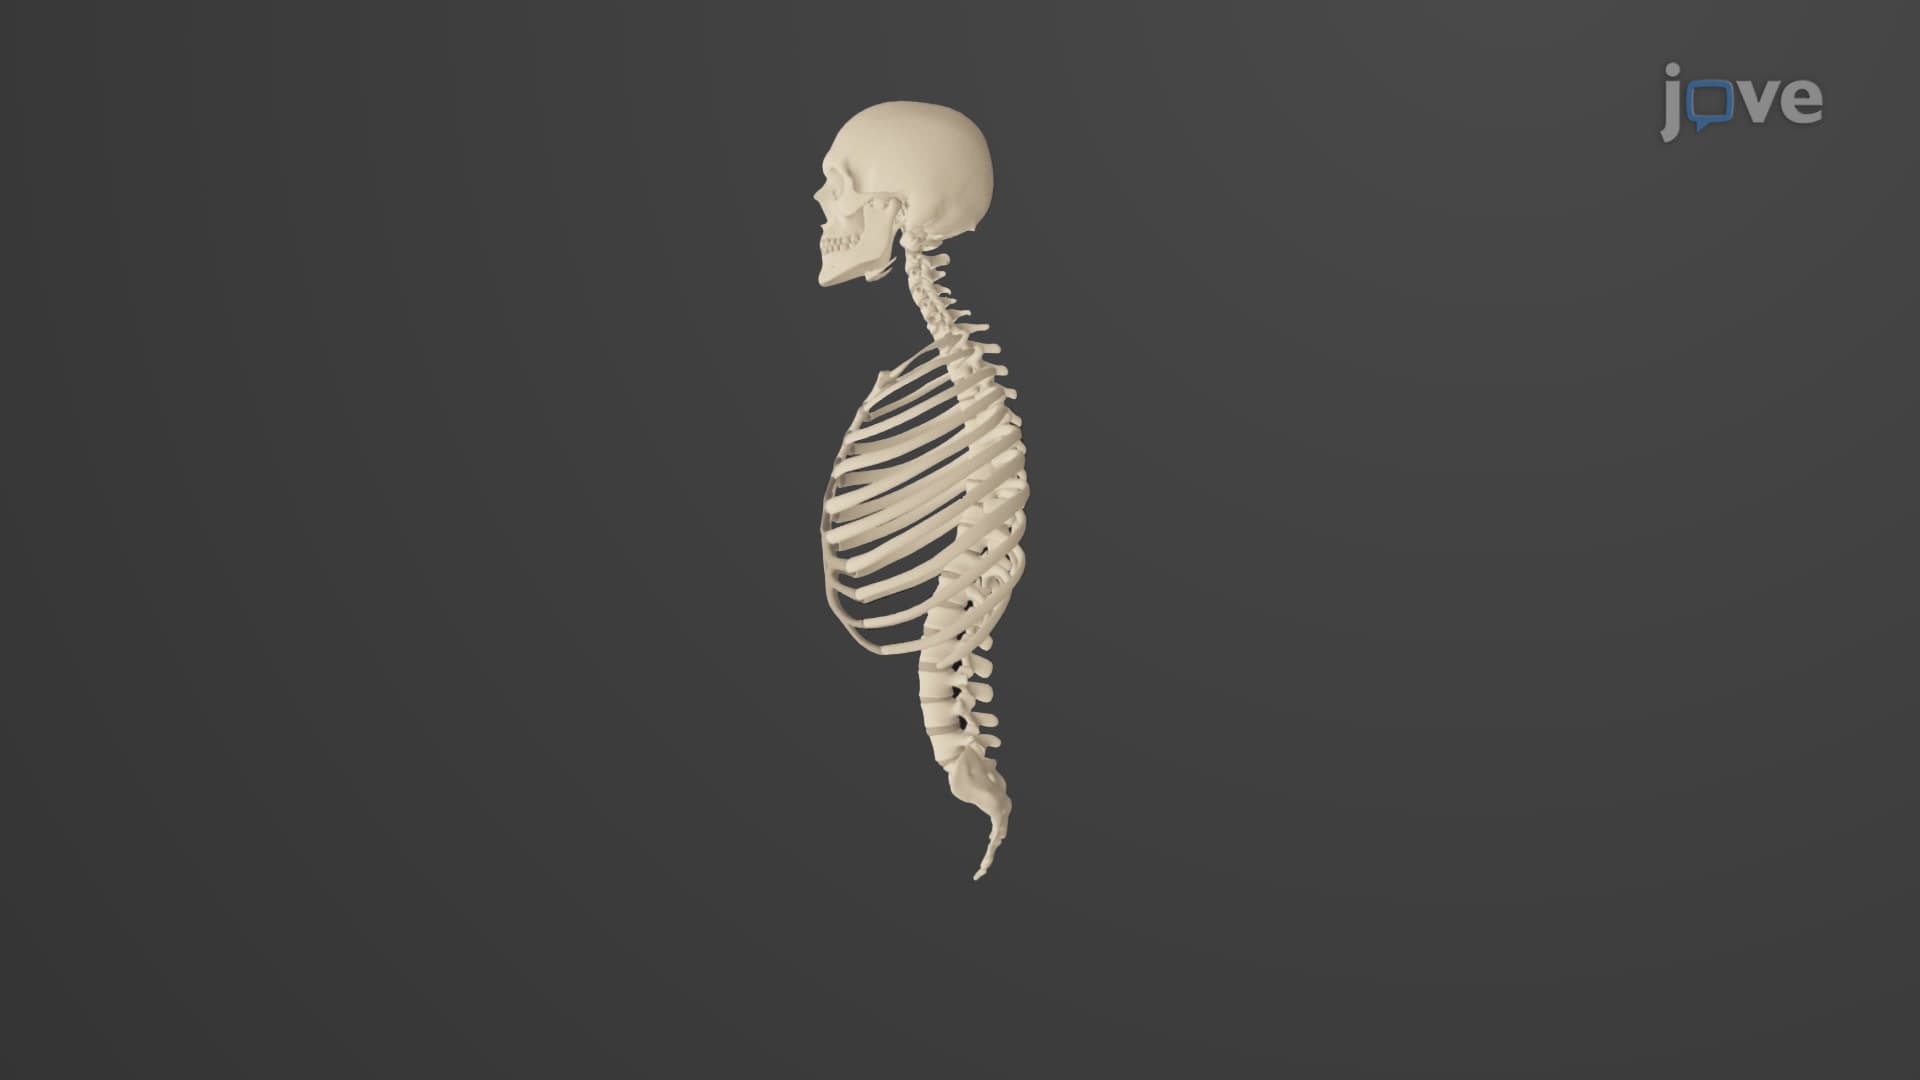
Overview of the Axial Skeleton
The axial skeleton of the adult...