Related Experiment Video
Updated: May 31, 2026


Measuring Carbon Content in Airway Macrophages Exposed to Carbon-Containing Particulate Matters
Published on: July 12, 2024
A persisting secondhand smoke hazard in urban public places: results from fine particulate (PM2.5) air sampling
Nick Wilson1, Richard Edwards, Rhys Parry
1Department of Public Health, University of Otago Wellington, PO Box 7343 Wellington South, New Zealand. nick.wilson@otago.ac.nz

Aim:
To assess the need for additional smokefree settings, by measuring secondhand smoke (SHS) in a range of public places in an urban setting.
Methods:
Measurements were made in Wellington City during the 6-year period after the implementation of legislation that made indoor areas of restaurants and bars/pubs smokefree in December 2004, and up to 20 years after the 1990 legislation making most indoor workplaces smokefree. Fine particulate levels (PM2.5) were measured with a portable real-time airborne particle monitor. We collated data from our previously published work involving random sampling, purposeful sampling and convenience sampling of a wide range of settings (in 2006) and from additional sampling of selected indoor and outdoor areas (in 2007-2008 and 2010).
Results:
The "outdoor" smoking areas of hospitality venues had the highest particulate levels, with a mean value of 72 mcg/m3 (range of maximum values 51-284 mcg/m3) (n=20 sampling periods). These levels are likely to create health hazards for some workers and patrons (i.e., when considered in relation to the WHO air quality guidelines). National survey data also indicate that these venues are the ones where SHS exposure is most frequently reported by non-smokers. Areas inside bars that were adjacent to "outdoor" smoking areas also had high levels, with a mean of 54 mcg/m3 (range of maximum values: 18-239 mcg/m3, for n=13 measurements). In all other settings mean levels were lower (means: 2-22 mcg/m3). These other settings included inside traditional style pubs/sports bars (n=10), bars (n=18), restaurants (n=9), cafes (n=5), inside public buildings (n=15), inside transportation settings (n=15), and various outdoor street/park settings (n=22). During the data collection in all settings made smokefree by law, there was only one occasion of a person observed smoking.
Conclusions:
The results suggest that compliance in pubs/bars and restaurants has remained extremely high in this city in the nearly six years since implementation of the upgraded smokefree legislation. The results also highlight additional potential health gain from extending smokefree policies to reduce SHS exposure in the "outdoor" smoking areas of hospitality venues and to reduce SHS drift from these areas to indoor areas.

Related Concept Videos
 01:23
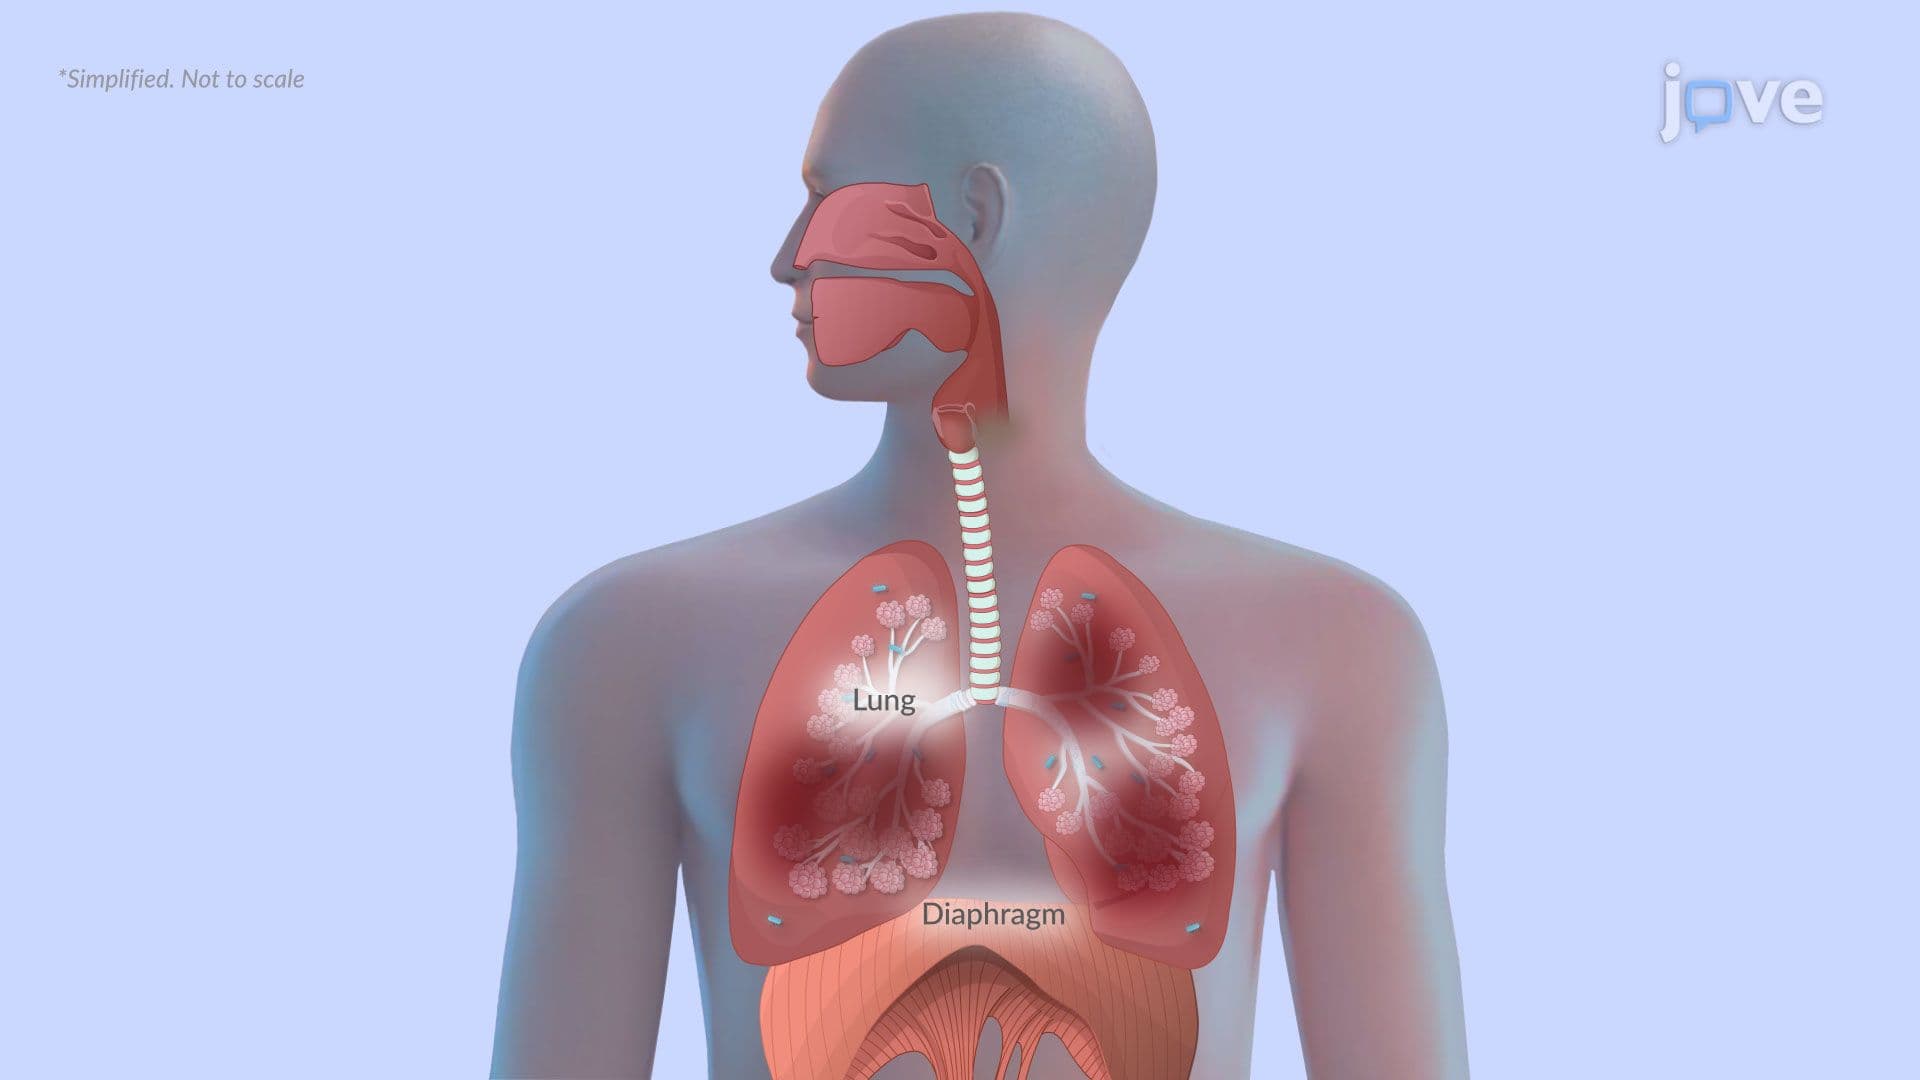
Chronic Obstructive Pulmonary Disease I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation