Related Experiment Video
Updated: May 31, 2026
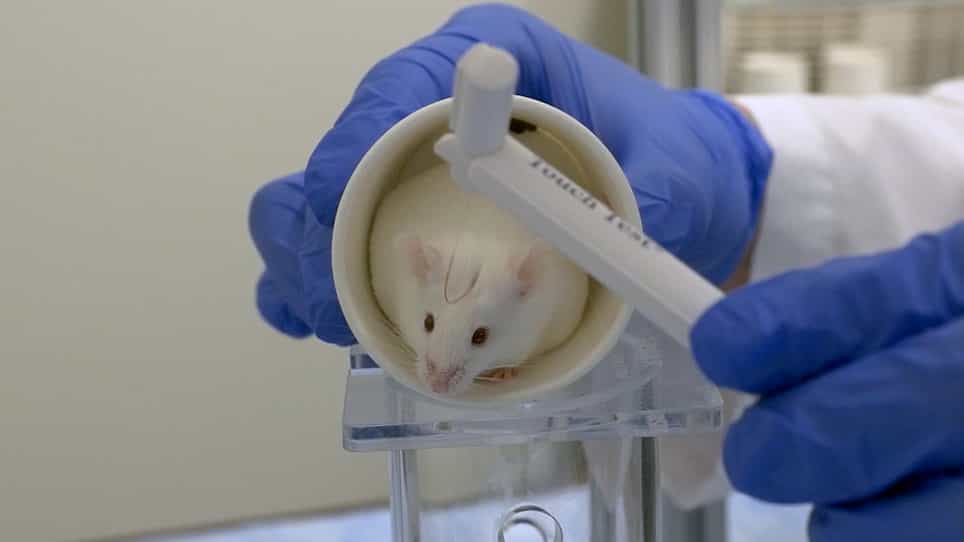

Dural Stimulation and Periorbital von Frey Testing in Mice As a Preclinical Model of Headache
Published on: July 29, 2021
Dr. Harvey Cushing's attempts to cure migraine based on theories of pathophysiology
Katherine Latimer1, Courtney Pendleton, Jason Rosenberg
1Departments of Neurosurgery and Oncology, The Johns Hopkins School of Medicine, Baltimore, Maryland, USA.

Abstract:
A multitude of theories characterized medical thought on migraine in the early 20th century. Newly discovered historical case files revealed Dr. Harvey Cushing's previously unpublished early attempts at surgical cure of migraine. Following institutional review board approval, and through the courtesy of the Alan Mason Chesney Archives, the authors reviewed the microfilm surgical records for The Johns Hopkins Hospital from 1896 to 1912. Patients undergoing surgical intervention by Dr. Harvey Cushing for the treatment of migraine were selected for further review. All 4 patients in the series were women and ranged in age from 29 to 41 years old. The women were admitted and observed in the hospital until a migraine occurred. Surgeries were performed while the women were in the midst of an attack. Cushing used surgical strategies including decompression, temporal artery ligation, and removal of the spine of the second vertebra. In each case, the patients' headaches eventually returned following surgery. Cushing relied on a combination of contemporary theories on migraine including humeral science, vasospastic theory, organic cause, and increased intracranial pressure. His unpublished efforts foreshadowed future surgical efforts at curing migraines.


Related Concept Videos
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:22
Pathophysiology of Vomiting
 01:27
Psychosis: Pathophysiology of Schizophrenia and Other Psychotic Disorders
Researchers have identified genetic factors that increase susceptibility to schizophrenia, underscoring the intricate interplay between genetics and environment in disease development. At the core of schizophrenia's pathophysiology is excessive dopaminergic neurotransmission within the...