Related Experiment Video
Updated: May 31, 2026
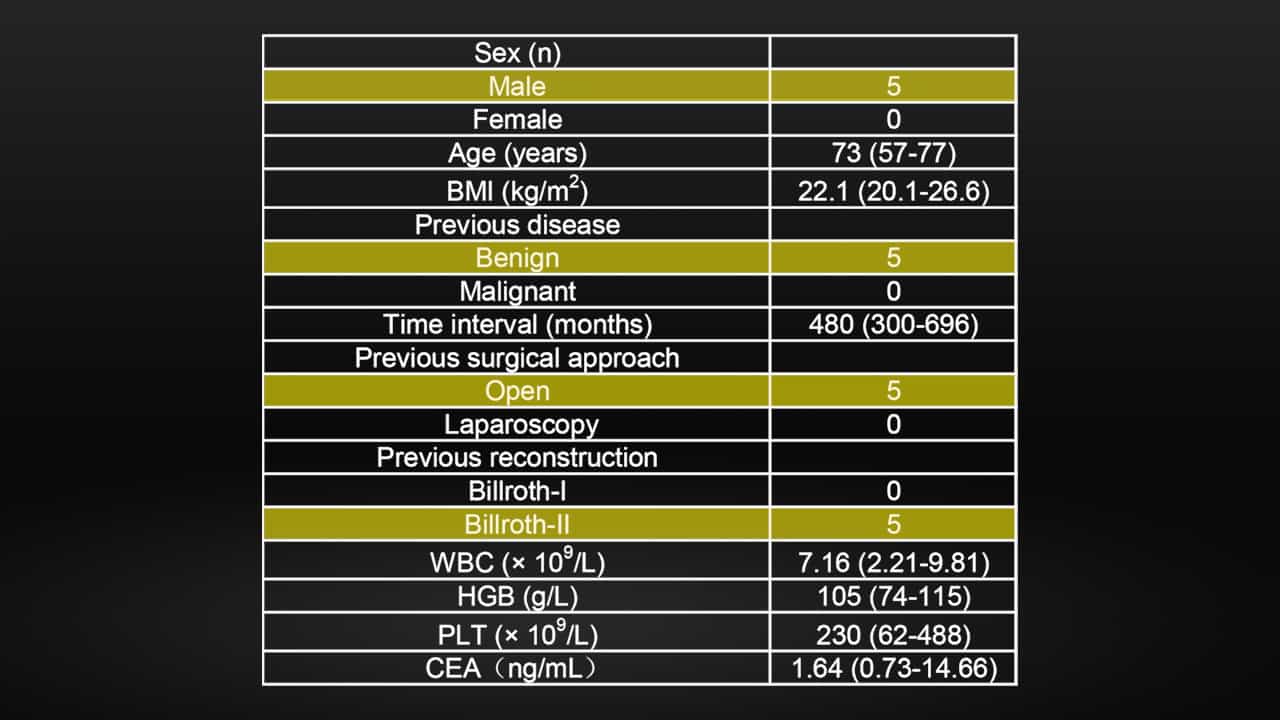

Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
Neoadjuvant chemoradiotherapy for resectable oesophageal and gastro-oesophageal junction cancer--do we need another
M Hingorani1, T Crosby, A Maraveyas
1Queen's Centre for Oncology and Haematology, Castle Hill Hospital, Cottingham, UK. mohan.hingorani@hey.nhs.uk

Aims:
The optimal neoadjuvant therapy option for locally advanced oesophageal cancer remains elusive. Neoadjuvant chemoradiotherapy (CRT) is the preferred modality of choice in the USA. In contrast, neoadjuvant chemotherapy is commonly used in the UK. We provide a comprehensive overview of the available evidence for defining the ideal neoadjuvant treatment algorithm.
Materials And Methods:
The PubMed database combined with American Society of Clinical Oncology and American Society for Therapeutic Radiology and Oncology websites were searched online to identify randomised studies and published meta-analyses that have compared these modalities compared with surgery alone. In particular, we searched for randomised trials that may have directly compared outcomes after neoadjuvant CRT or chemotherapy.
Results:
We identified 17 published randomised studies of neoadjuvant CRT (n = 9) and chemotherapy (n = 8) compared with surgery alone and one prospective series that compared the above modalities against each other. Studies evaluating CRT have reported pathological complete response rates of 15-40% and no increase in postoperative mortality was observed, except in one study that used a hypofractionated radiation schedule. Two randomised studies showed significant survival benefit and the remaining (n = 7) were negative, but showed a trend towards improved survival. Furthermore, at least four meta-analyses have shown improved survival in favour of CRT extending up to an absolute benefit of 13% at 2 years. In comparison, five studies of neoadjuvant chemotherapy showed no survival difference and two of the remaining studies that showed significant benefit included gastric adenocarcinomas and used peri-operative chemotherapy. All the above studies have shown uniformly poor pathological complete response rates of less than 10 percent. Moreover, three meta-analyses were negative, but two showed up to 7% absolute survival benefit at 2 years in favour of chemotherapy. The trial comparing the above modalities showed a trend towards improved survival in favour of CRT, but closed early due to poor recruitment.
Conclusion:
Data from the above studies are potentially conflicting and inconclusive for defining the optimal neoadjuvant treatment schedule. In our opinion, the above question can only be answered within the context of a randomised control trial. We have included a proposal for a trial design for direct comparison of these modalities.
Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 02:56
Treatment Resistent Cancers
 01:27
Esophageal Achalasia