Related Experiment Video
Updated: May 31, 2026


Preclinical Cardiac Electrophysiology Assessment by Dual Voltage and Calcium Optical Mapping of Human Organotypic Cardiac Slices
Published on: June 16, 2020
Electrophysiology issues in adult congenital heart disease
Wilson Lam1, Richard A Friedman
1Baylor College of Medicine, Houston, Texas, USA.

Insights
Adults with congenital heart disease (ACHD) face frequent rhythm disturbances. Advances in medical management, catheter ablation, device therapy, and surgery are improving outcomes for these complex patients.
Area of Science:
- Cardiology
- Electrophysiology
- Adult Congenital Heart Disease
Background:
- Improved pediatric surgical outcomes have increased the population of adults with congenital heart disease (ACHD).
- ACHD patients frequently experience rhythm disturbances, including tachyarrhythmias and bradyarrhythmias, due to intrinsic anomalies or post-surgical palliation.
- An estimated one million-plus ACHD patients live in the US, with moderate to severe defects having a high incidence of arrhythmia.
Purpose of the Study:
- To review current management strategies for rhythm disturbances in adults with congenital heart disease.
- To discuss the role of medical management, catheter ablation, device therapy, and surgical interventions in addressing arrhythmias in ACHD.
- To highlight technological and surgical advances that reduce arrhythmia incidence and improve patient outcomes.
Main Methods:
- Review of medical literature and clinical practice guidelines for arrhythmia management in ACHD.
- Discussion of various therapeutic modalities including pharmacotherapy, catheter ablation, implantable devices, and surgical repair.
- Analysis of epidemiological data and outcomes associated with different congenital heart defects and interventions.
Main Results:
- Specific congenital heart defects like Tetralogy of Fallot and single ventricle palliation (Fontan) are associated with high rates of supraventricular and ventricular arrhythmias.
- Post-operative atrioventricular block is a recognized complication of congenital heart surgery, sometimes requiring permanent pacing.
- Catheter ablation in ACHD presents unique challenges due to abnormal anatomy, but advances in mapping and catheter technology are improving efficacy.
- Surgical innovations, such as the arterial switch operation and extracardiac Fontan procedures, have reduced arrhythmia incidence.
Conclusions:
- Rhythm disturbances are a significant concern in the growing ACHD population.
- A multi-faceted approach involving medical, interventional, and surgical strategies is crucial for managing arrhythmias in ACHD.
- Ongoing technological and surgical advancements continue to enhance the treatment and long-term prognosis for ACHD patients with cardiac rhythm abnormalities.
Abstract:
Improved surgical outcomes in children have led to a growing population of adults with congenital heart disease. Rhythm disturbances in the adult congenital heart disease (ACHD) patient can be intrinsic to the anomaly or acquired after palliation. Tachyarrhythmias, either supraventricular or ventricular, and bradyarrhythmias, either sinus node dysfunction or atrioventricular block, may occur frequently. Technological advances in intervention and surgical approaches have led to prophylactic and therapeutic reduction in arrhythmias. In order of escalation, this article addresses medical management, catheter ablation, device therapy for antitachycardia pacing and defibrillation, and surgical intervention. There are now an estimated one million-plus ACHD patients living in the United States. An estimated 45% of those have simple defects (e.g., atrial septal defects), 40% have moderately complex defects (e.g., tetralogy of Fallot, or ToF), and 15% have severely complex defects (e.g., single ventricle anatomy or surgical palliations for transposition of the great arteries [TGA]). The moderate and severe categories have a high incidence of arrhythmia. Of older repaired ToF patients, 34% develop symptomatic atrial or supraventricular tachycardias, 8.5% develop high-grade ventricular tachycardia (VT), and there are an increasing number of implantable defibrillators due to a sudden-death estimate of 2% per decade. Thus, an estimated 50,000 adults with repaired ToF will require electrophysiology follow-up with 100 sudden deaths per year nationally. Roughly 3% of all congenital heart surgeries requiring cardiopulmonary bypass have post-operative AV block, and 1% will require permanent pacing. Older atriopulmonary Fontans have up to an estimated 50% incidence of atrial tachycardia within a decade of palliation due to suture lines and elevated atrial pressures. Patients who have undergone an atrial switch operation (e.g., Mustard or Senning operations) are rarely exclusively in sinus rhythm a decade after repair, thus posing problems for rhythm control and anticoagulation. Catheter ablation in congenital heart disease is often more challenging than structurally normal hearts because of abnormal anatomy (congenital and/or post-surgical) and thicker chamber walls due to unfavorable hemodynamics. In preparation, review of noninvasive imaging, previous catheterization angiography, and surgical palliation reports are paramount prior to a procedure. Fortunately, to meet the growing challenge, newer software with 3-D packages allow for improved mapping. In addition, advances with larger-tipped and irrigated-tip catheters allow for deeper, more effective lesions to be placed. Several advances in surgical approach have led to a reduction in arrhythmias. For example, the arterial switch operation for d-transposition of the great arteries instead of the aforementioned atrial switch operation eliminates the use of a systemic right ventricle that can later develop intra-atrial reentrant tachycardia and sinus node dysfunction. Other advances include paying careful attention to minimizing ventriculotomies in ToF and ventricular septal defect (VSD) repairs, earlier complete repairs, and valve sparing to reduce pulmonary insufficiency. Finally, completion of the extra-cardiac Fontan procedure (e.g., total cavopulmonary connection) for single ventricles avoids extensive suture lines in the right atrium, thereby reducing scarring and higher pressures that lead to IART and sinus node dysfunction. Extracardiac (EC) conduits and lateral tunnel (LT) Fontans are preferred today, and the Fontan conversion procedure (converting prior atriopulmonary Fontans to the EC or LT type) can be performed to reduce arrhythmia and thromboembolic events.


Related Concept Videos
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:28
Mechanism of Cardiac Arrhythmias
 01:30
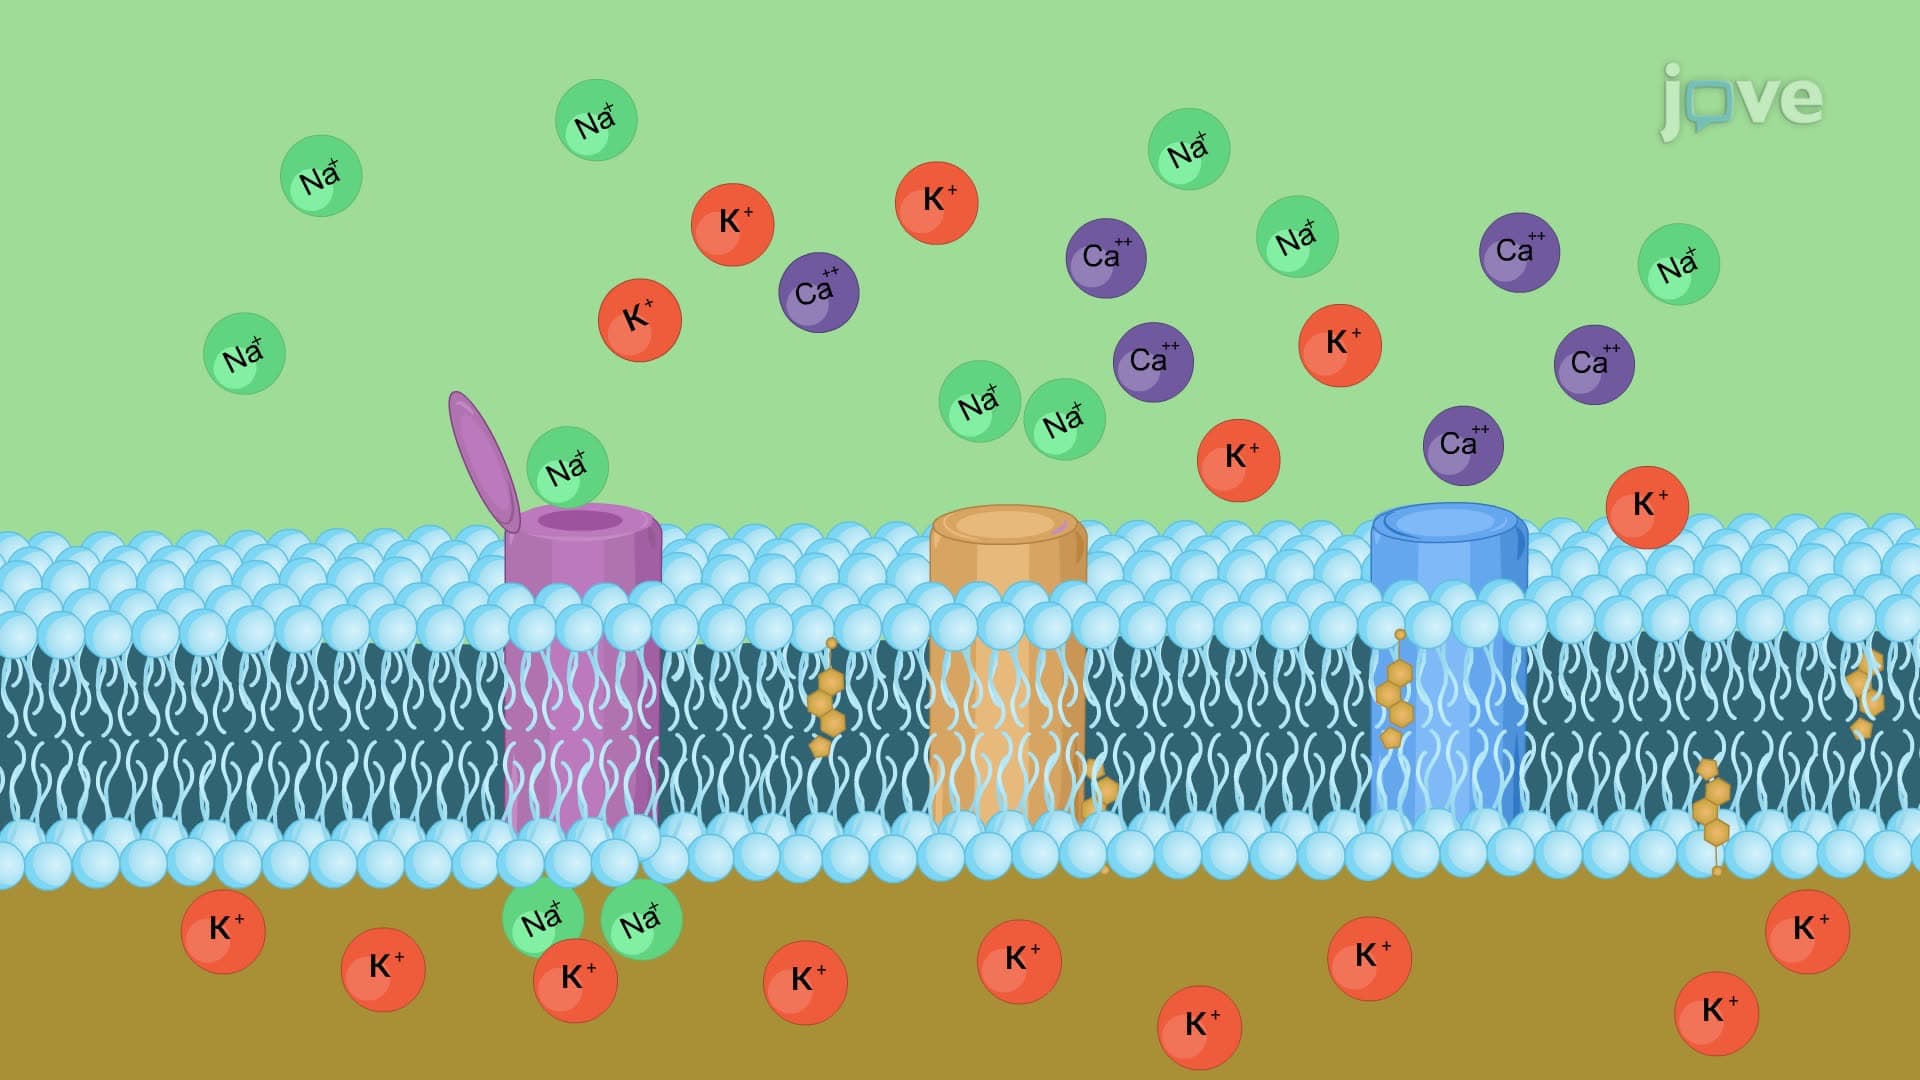
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:15
Dysrhythmias I: Introduction
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:25
Dysrhythmias VI: Management of Dysrhythmias