Related Experiment Video
Updated: May 31, 2026

Intra-Omental Islet Transplantation Using h-Omental Matrix Islet filliNG (hOMING)
Published on: March 14, 2019
Treatment of congenital hyperinsulinism with lanreotide acetate (Somatuline Autogel)
Dalit Modan-Moses1, Ilana Koren, Kineret Mazor-Aronovitch
1Pediatric Endocrinology and Diabetes Unit, The Edmond and Lily Safra Children's Hospital, Chaim Sheba Medical Center, Tel-Hashomer (affiliated with The Sackler School of Medicine, Tel-Aviv University), 52621 Israel. dmodan@sheba.health.gov.il

Insights
Lanreotide acetate, a long-acting somatostatin analog, offers a safe and effective alternative to continuous octreotide pump therapy for congenital hyperinsulinism (CH). This monthly injection improves patient quality of life and is well-tolerated.
Area of Science:
- Pediatric Endocrinology
- Metabolic Disorders
- Pharmacology
Background:
- Congenital hyperinsulinism (CH) is a rare genetic disorder characterized by excessive insulin secretion, leading to severe hypoglycemia.
- Current conservative management often involves frequent feedings and medications like octreotide, administered via multiple daily injections or insulin pumps.
Observation:
- This study reports on two pediatric patients diagnosed with CH who presented with hypoglycemia shortly after birth.
- Both patients were initially managed with a combination of diazoxide, hydrochlorothiazide, frequent feedings, and octreotide via an insulin pump, achieving normoglycemia and good developmental outcomes.
Findings:
- The patients were transitioned to a once-monthly deep subcutaneous injection of lanreotide acetate (30 mg), a long-acting somatostatin analog.
- Continuous glucose monitoring confirmed normoglycemia after discontinuing octreotide pump therapy.
- Treatment with lanreotide acetate has been well-tolerated for over 3-5 years, with patients and parents expressing satisfaction and preference for the monthly injection over pump therapy.
Implications:
- Lanreotide acetate presents a promising, safe, and effective alternative to continuous octreotide pump therapy for managing CH.
- The simplified dosing regimen significantly enhances the quality of life for patients and their families.
- Further long-term studies with larger cohorts are warranted to solidify these findings.
Context:
Congenital hyperinsulinism (CH) may be treated conservatively in many children with octreotide given by multiple sc injections or via an insulin pump.
Objective:
We describe two children treated with a once-monthly injection of a long-acting somatostatin analog.
Patients And Methods:
Both patients presented with hypoglycemia 30 min after birth and were subsequently diagnosed with CH. Patients were initially treated with diazoxide, hydrochlorothiazide, frequent feedings, and octreotide via an insulin pump. With this therapy, they were normoglycemic with a good growth rate, normal weight gain, and excellent neurodevelopment. Treatment with the long-acting somatostatin analog lanreotide acetate (Somatuline Autogel), administered by deep sc injection of 30 mg once a month, was started at the ages of 4½ and 4 yr, respectively. Octreotide infusion was gradually weaned over 1 month. Continuous glucose monitoring after discontinuation of pump therapy showed normoglycemia. The first patient has now been treated with the lanreotide acetate for over 5 yr, and the second for 3 yr. Treatment is well-tolerated, and both the patients and their parents are satisfied with the transition from pump therapy to once-a-month injection and prefer it to pump therapy.
Conclusion:
Lanreotide acetate may be a safe and effective alternative to octreotide pump therapy in patients with CH, offering an improved quality of life. Longer follow-up of a larger patient group is needed.
Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:06
Oral Hypoglycemic Agents: Glinides
 01:25
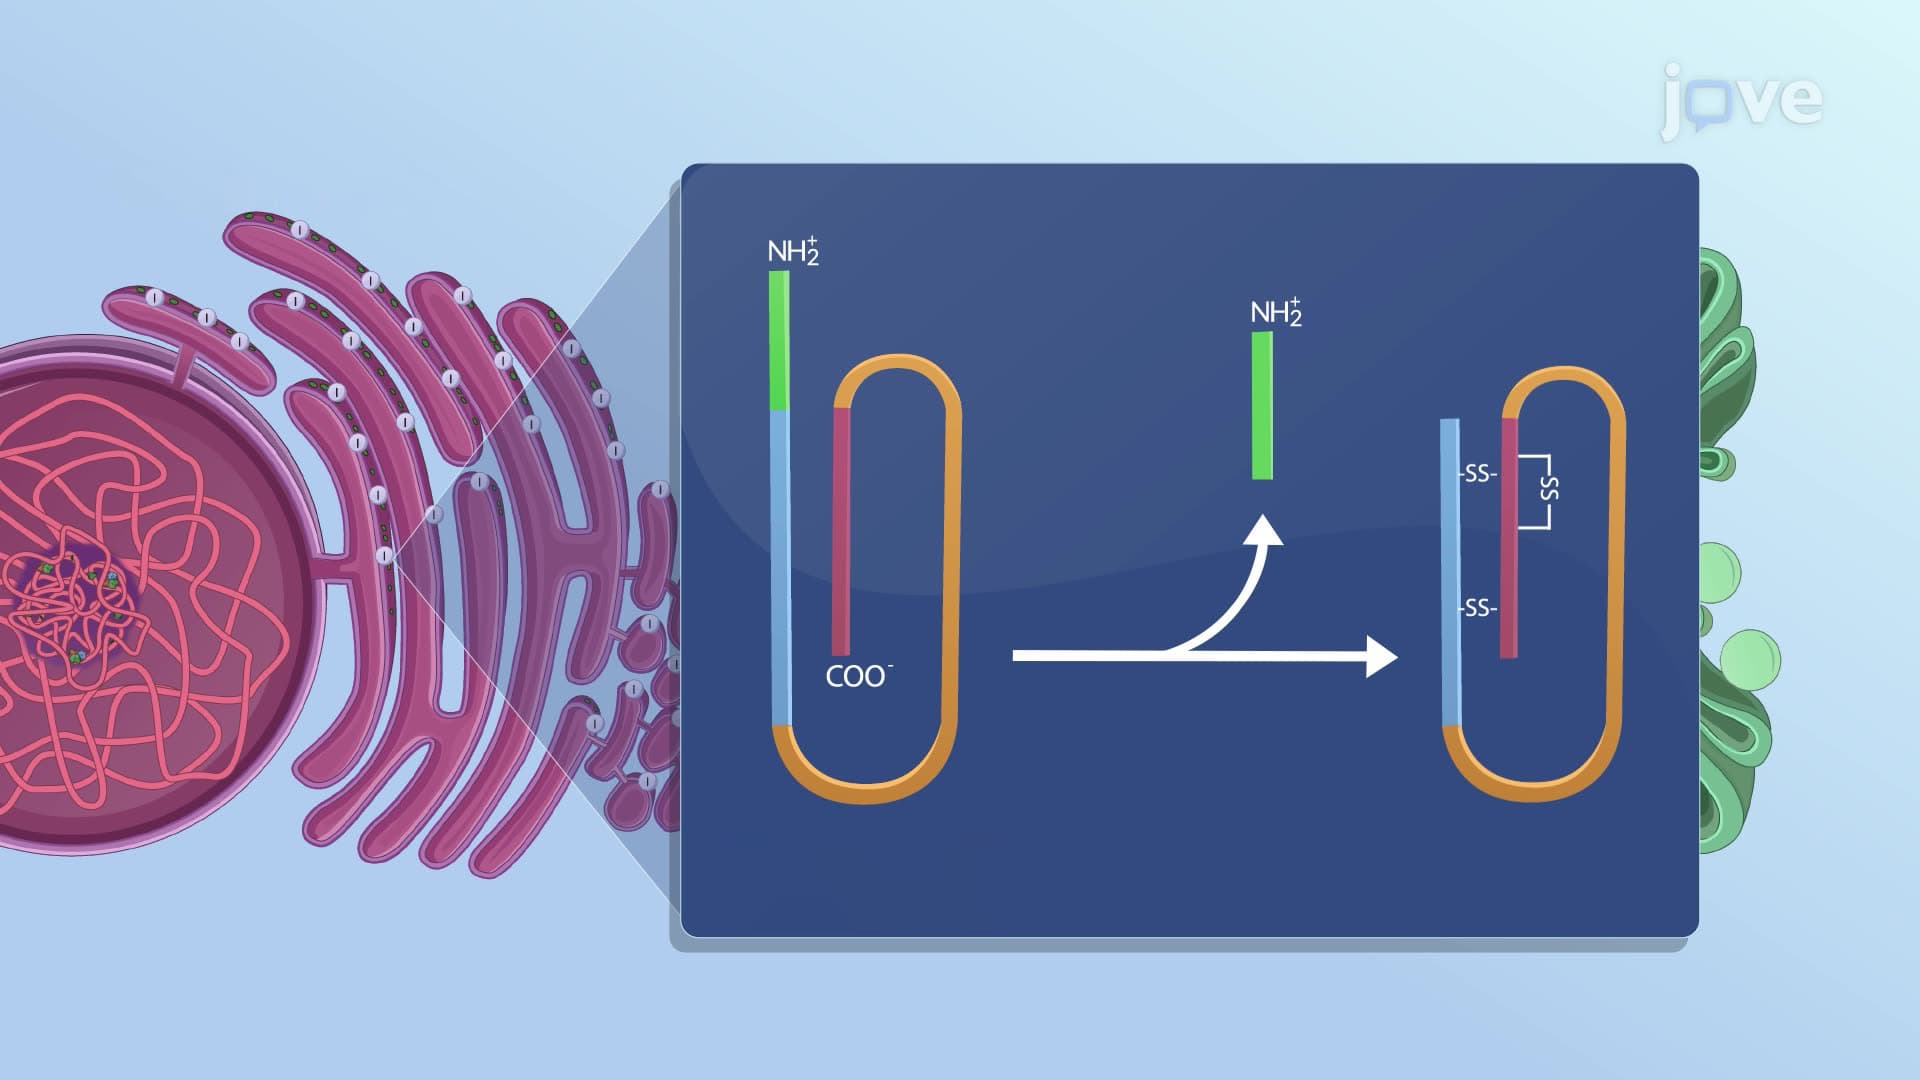
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:15
Hypoglycemia and Glucagon
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...