Related Experiment Video
Updated: May 31, 2026

Biochemical Measurement of Neonatal Hypoxia
Published on: August 24, 2011
Threshold for toxicity from hyperammonemia in critically ill children
Bruno Ozanne1, John Nelson, Jocelyne Cousineau
1CHU Sainte-Justine, Soins Intensifs, 3175 Chemin de la Côte Sainte-Catherine, Montréal (QC), Canada H3T 1C5.

Insights
High ammonia levels (hyperammonemia) in children significantly increase mortality risk, especially in liver failure. A threshold of 200 μmol/L ammonia within 48 hours indicates a critical risk.
Area of Science:
- Pediatric critical care
- Metabolic disorders
- Toxicology
Background:
- Hyperammonemia, caused by reduced liver function or urea cycle enzyme deficiency, can lead to severe cerebral edema and herniation.
- The precise ammonia toxicity threshold and its impact on pediatric mortality remain incompletely understood.
Purpose of the Study:
- To determine the ammonia toxicity threshold associated with mortality in critically ill children.
- To identify risk factors for mortality in pediatric hyperammonemia.
- To compare treatment patterns and outcomes between liver failure and urea cycle defects.
Main Methods:
- Retrospective observational study of pediatric intensive care unit patients with hyperammonemia (January 2000 - April 2009).
- Data collected included clinical and laboratory parameters, treatments, and ammonia levels within the first 7 days.
- Logistic regression analysis was used to estimate the risk of 28-day mortality.
Main Results:
- Ninety patients were included, primarily with liver failure (63.3%) or urea cycle defects (23.3%).
- A 28-day mortality rate of 31.1% was observed.
- Ammonemia ≥200 μmol/L within 48 hours was an independent risk factor for mortality (OR 3.3), with higher risk in liver failure compared to urea cycle defects. Ammonia scavengers were less frequently used in liver failure.
Conclusions:
- An ammonia threshold of ≥200 μmol/L within 48 hours significantly increases mortality risk in pediatric hyperammonemia, particularly in cases of liver failure.
- Timely and appropriate use of ammonia scavengers may be crucial, as they were underutilized in liver failure patients despite potential benefits.
Background & Aims:
Hyperammonemia results from reduction of hepatocyte function or enzyme of urea cycle deficiency. Hyperammonemia contributes to cerebral edema that may lead to cerebral herniation. The threshold of toxicity of ammonemia is unknown.
Methods:
We conducted a retrospective observational study in our pediatric intensive care unit. All children who developed hyperammonemia from January 2000 to April 2009 were included. Clinical and laboratory data at admission, specific treatments implemented, and ammonemias the first 7 days after inclusion were collected. The outcome assessed was 28 day mortality. Risk of mortality was estimated by a logistic regression model.
Results:
Ninety patients with liver failure (63.3%) and primary or secondary urea cycle defect (23.3%) were included. Patients with urea cycle defects were more likely to receive ammonia scavengers than patients with liver failure (47.6% versus 3.5%). The 28 day mortality rate was 31.1%. Risk of mortality increased according to the ammonemia within 48 h: odds ratio 1.5, 1.9, 3.3, 2.4 for ammonemia above 100, 150, 200, and 300 μmol/L, respectively. Peak ammonemia ≥200 μmol/L within the first 48 h was an independent risk factor for mortality, with greater risk found in liver failure than in urea cycle defect.
Conclusions:
Our study identifies a threshold of exposure to ammonia (≥200 μmol/L) above which mortality increases significantly, especially in liver failure. Specific treatments of hyperammonemia are rarely used in liver failure when compared with urea cycle defect even though use of ammonia scavengers may help to decrease ammonemia.
More Related Videos


Related Concept Videos
 01:23
Urea Cycle
 01:20
Titration of a Weak Base with a Strong Acid
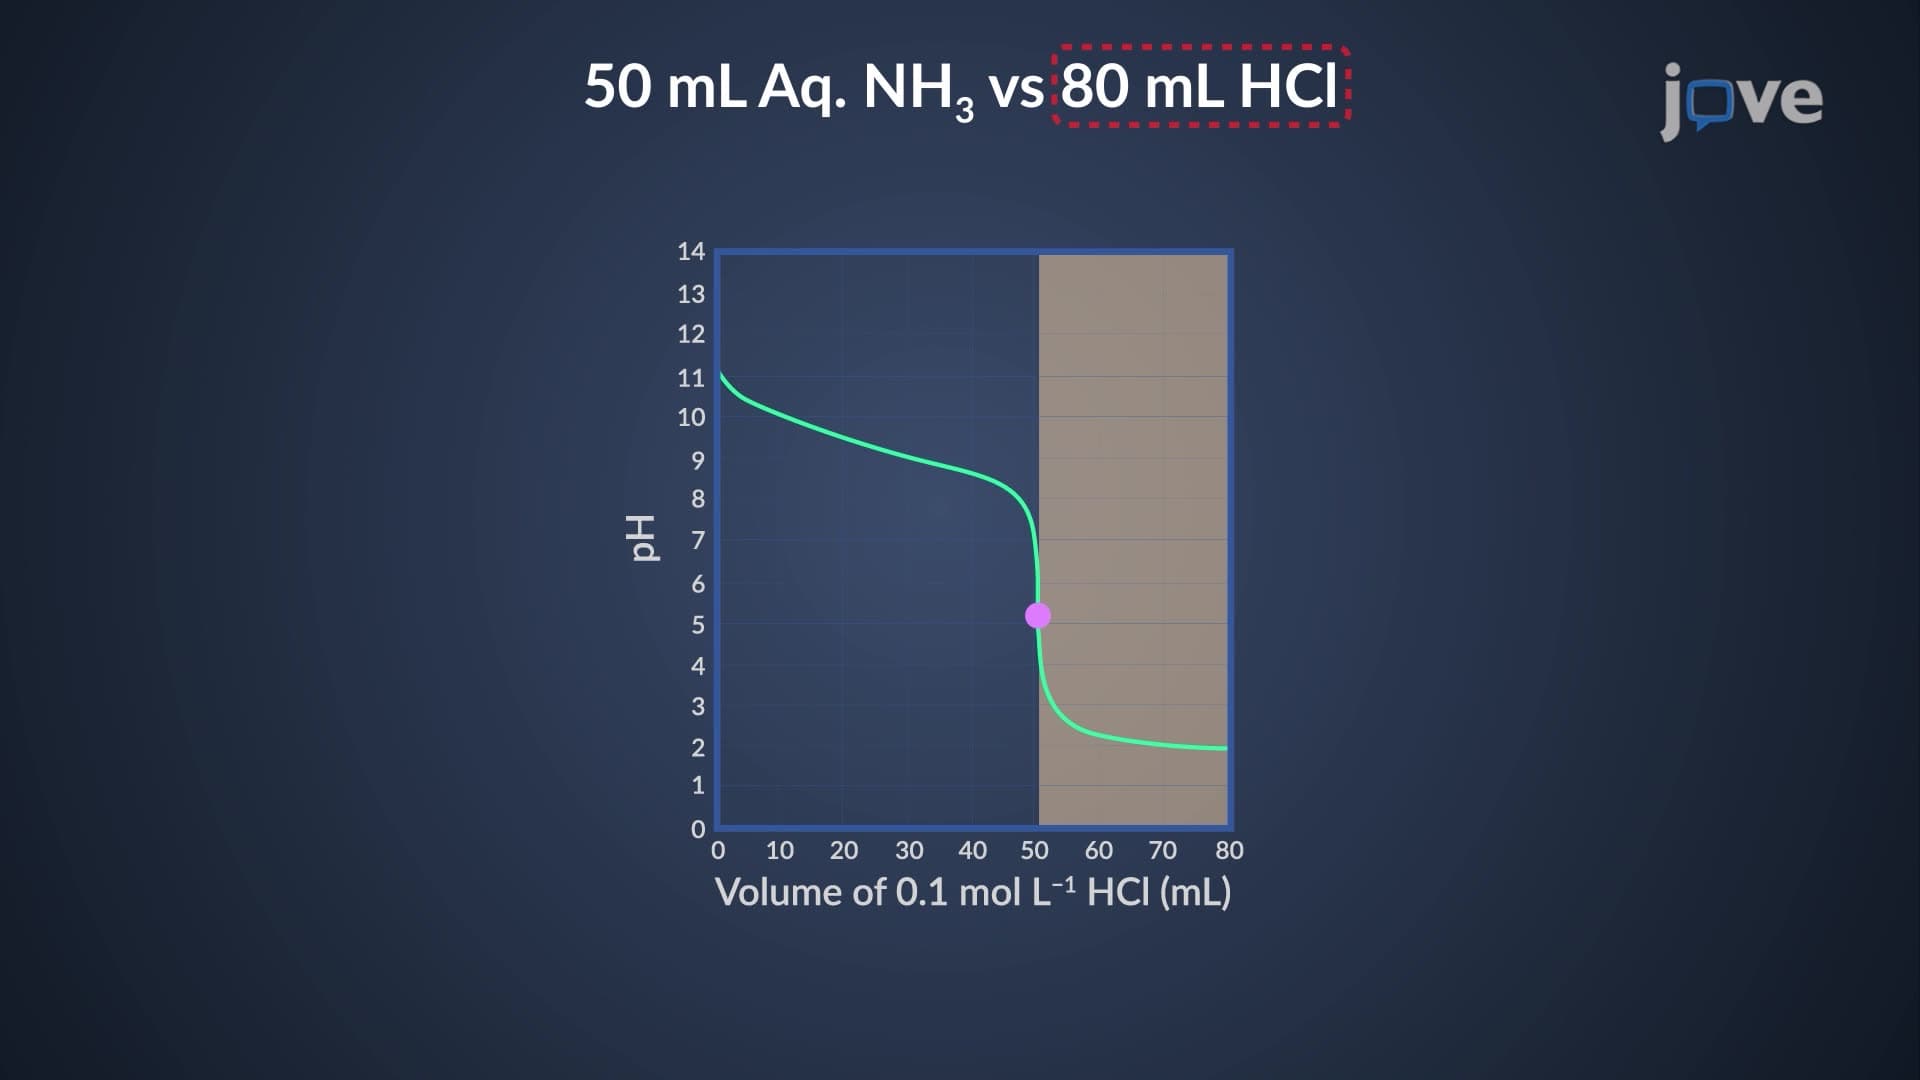
Using the ICE table and substituting the Kb value, we calculate the initial pH of 50 mL of 0.1 M ammonia to be 11.11. Addition of 25 mL of 0.1 M hydrochloric acid to this solution of ammonia results in a buffer with an equal concentration of ammonia and ammonium ions. The pH of this buffer can be calculated by substituting these...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:29
Hepatic Encephalopathy
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption