Related Experiment Video
Updated: May 31, 2026


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Concurrent primary aldosteronism and subclinical cortisol hypersecretion: a prospective study
Francesco Fallo1, Chiara Bertello, Davide Tizzani
1Department of Medical and Surgical Sciences, University of Padova, Padova, Italy. francesco.fallo@unipd.it

Background:
Primary aldosteronism is the most frequent cause of secondary hypertension and is responsible for an increased risk of cardiometabolic complications. A concomitant subtle cortisol hyperproduction could enhance cardiovascular risk. We prospectively estimated the occurrence of subclinical hypercortisolism in primary aldosteronism patients.
Methods:
In a large population of hypertensive patients without clinical signs of hypercortisolism, 76 consecutive patients with primary aldosteronism were investigated. Differential diagnosis between unilateral and bilateral aldosterone hypersecretion was made by computed tomography/MRI and/or adrenal venous sampling (AVS). Subclinical hypercortisolism was defined as failure to suppress plasma cortisol to less than 50 nmol/l after 1 mg-overnight dexamethasone, used as screening test, and at least one of two other abnormal hormonal parameters, that is, adrenocorticotrophin (ACTH) less than 2 pmol/l and urinary cortisol more than 694 nmol/24 h.
Results:
Three out of 76 patients had postdexamethasone plasma cortisol more than 50 nmol/l. Only one also showed low-normal ACTH and mildly elevated urinary cortisol. The patient had a right 4 cm adrenal mass. Laparoscopic adrenalectomy was followed by short-term steroid replacement to prevent adrenal insufficiency. In-situ hybridization showed CYP11B1 expression exclusively in tumoral tissue, whereas CYP11B2 was expressed only in a peritumoral region composed of zona glomerulosa-like cells, suggesting the co-existence of a cortisol-producing adenoma and an aldosterone-producing hyperplasia in the same adrenal. The restoration of hormone abnormalities to normal levels was confirmed at 12 months of follow-up.
Conclusion:
Concurrent aldosterone and subclinical cortisol hypersecretion seems to be a rare event in primary aldosteronism patients; however, its detection by appropriate testing is important to avoid AVS misinterpretation.

Related Concept Videos
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:37
Hypothalamic-Pituitary Axis
 01:31
Hormones of the Adrenal Glands
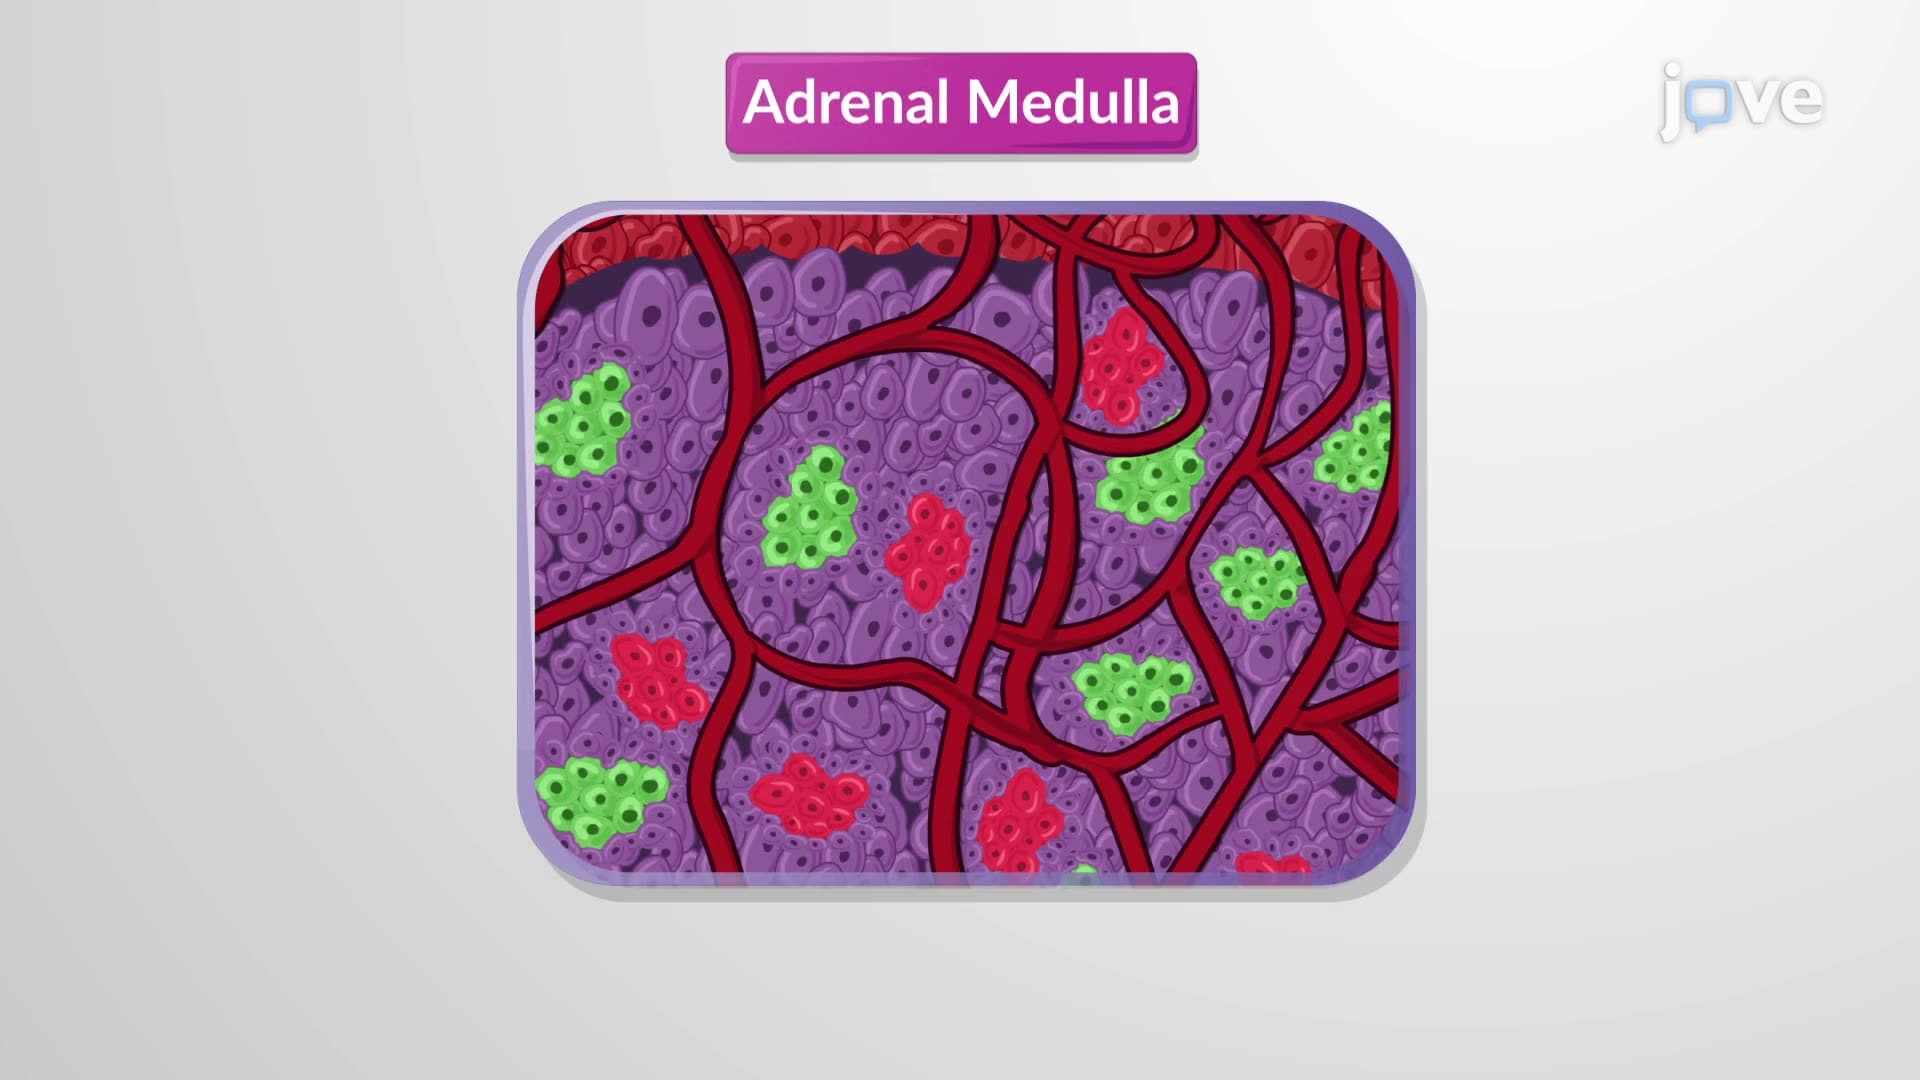
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...