176th ENMC International Workshop: diagnosis and treatment of coenzyme Q₁₀ deficiency
Related Experiment Video
Updated: May 31, 2026

07:35
Assessment of Open Probability of the Mitochondrial Permeability Transition Pore in the Setting of Coenzyme Q Excess
Published on: June 1, 2022
Shamima Rahman1, Catherine F Clarke, Michio Hirano
1Clinical and Molecular Genetics Unit, UCL Institute of Child Health, London WC1N 1EH, UK. S.Rahman@ich.ucl.ac.uk
Neuromuscular Disorders : NMD
|July 5, 2011

Abstract
No abstract available in PubMed .


Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
Diagnosing Pulmonary EmbolismDiagnosing pulmonary embolism (PE) involves clinical assessment and advanced imaging tests. The preferred diagnostic tool is the spiral (helical) CT scan or CT angiography (CTA), which uses intravenous contrast media to visualize the pulmonary vasculature and identify emboli.A ventilation-perfusion (V/Q) scan is an alternative for patients unable to receive contrast media. This scan includes both perfusion and ventilation scanning. Perfusion scanning involves...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
Diagnosing acute coronary syndrome or ACS begins with a thorough patient history. Notable symptoms include central, crushing chest pain radiating to the left arm, neck, jaw, or back, along with shortness of breath, sweating (diaphoresis), nausea, vomiting, dizziness, and palpitations.It is crucial to note any history of cardiac illnesses and assess risk factors, including age, gender, smoking, hypertension, diabetes, hyperlipidemia, and a sedentary lifestyle.During physical examination, vital...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
Clinical manifestationsPeripheral Arterial Disease (PAD) manifests through a range of symptoms, from the characteristic intermittent claudication to atypical presentations and severe complications in advanced stages. Intermittent claudication, a hallmark symptom of PAD, presents as exercise-induced muscle pain that typically resolves within minutes of rest. This pain is reproducible and stems from inadequate blood flow, leading to the accumulation of lactic acid produced during anaerobic...
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
The key clinical manifestations of Rheumatic heart disease (RHD) include several distinct cardiac symptoms.Carditis, a hallmark of acute rheumatic fever, involves inflammation of the heart's endocardium, myocardium, and pericardium. Chronic RHD often results from recurrent episodes of carditis. Its symptoms include the following:Murmurs are caused by valvular damage, especially to the mitral and aortic valves. Mitral stenosis or regurgitation is common, with characteristic heart murmurs...
 01:21
Rheumatic Heart Disease III: Medical Management
Rheumatic heart disease (RHD) management can be divided into two main strategies: prevention and long-term management.Primary PreventionPrimary prevention focuses on timely diagnosis and management of group A streptococcal pharyngitis to prevent acute rheumatic fever. The most widely used antibiotic for treating this condition is intramuscular benzathine penicillin G.Acute Rheumatic Fever TreatmentThe primary treatment goal for a patient diagnosed with acute rheumatic fever is to suppress the...
 01:27
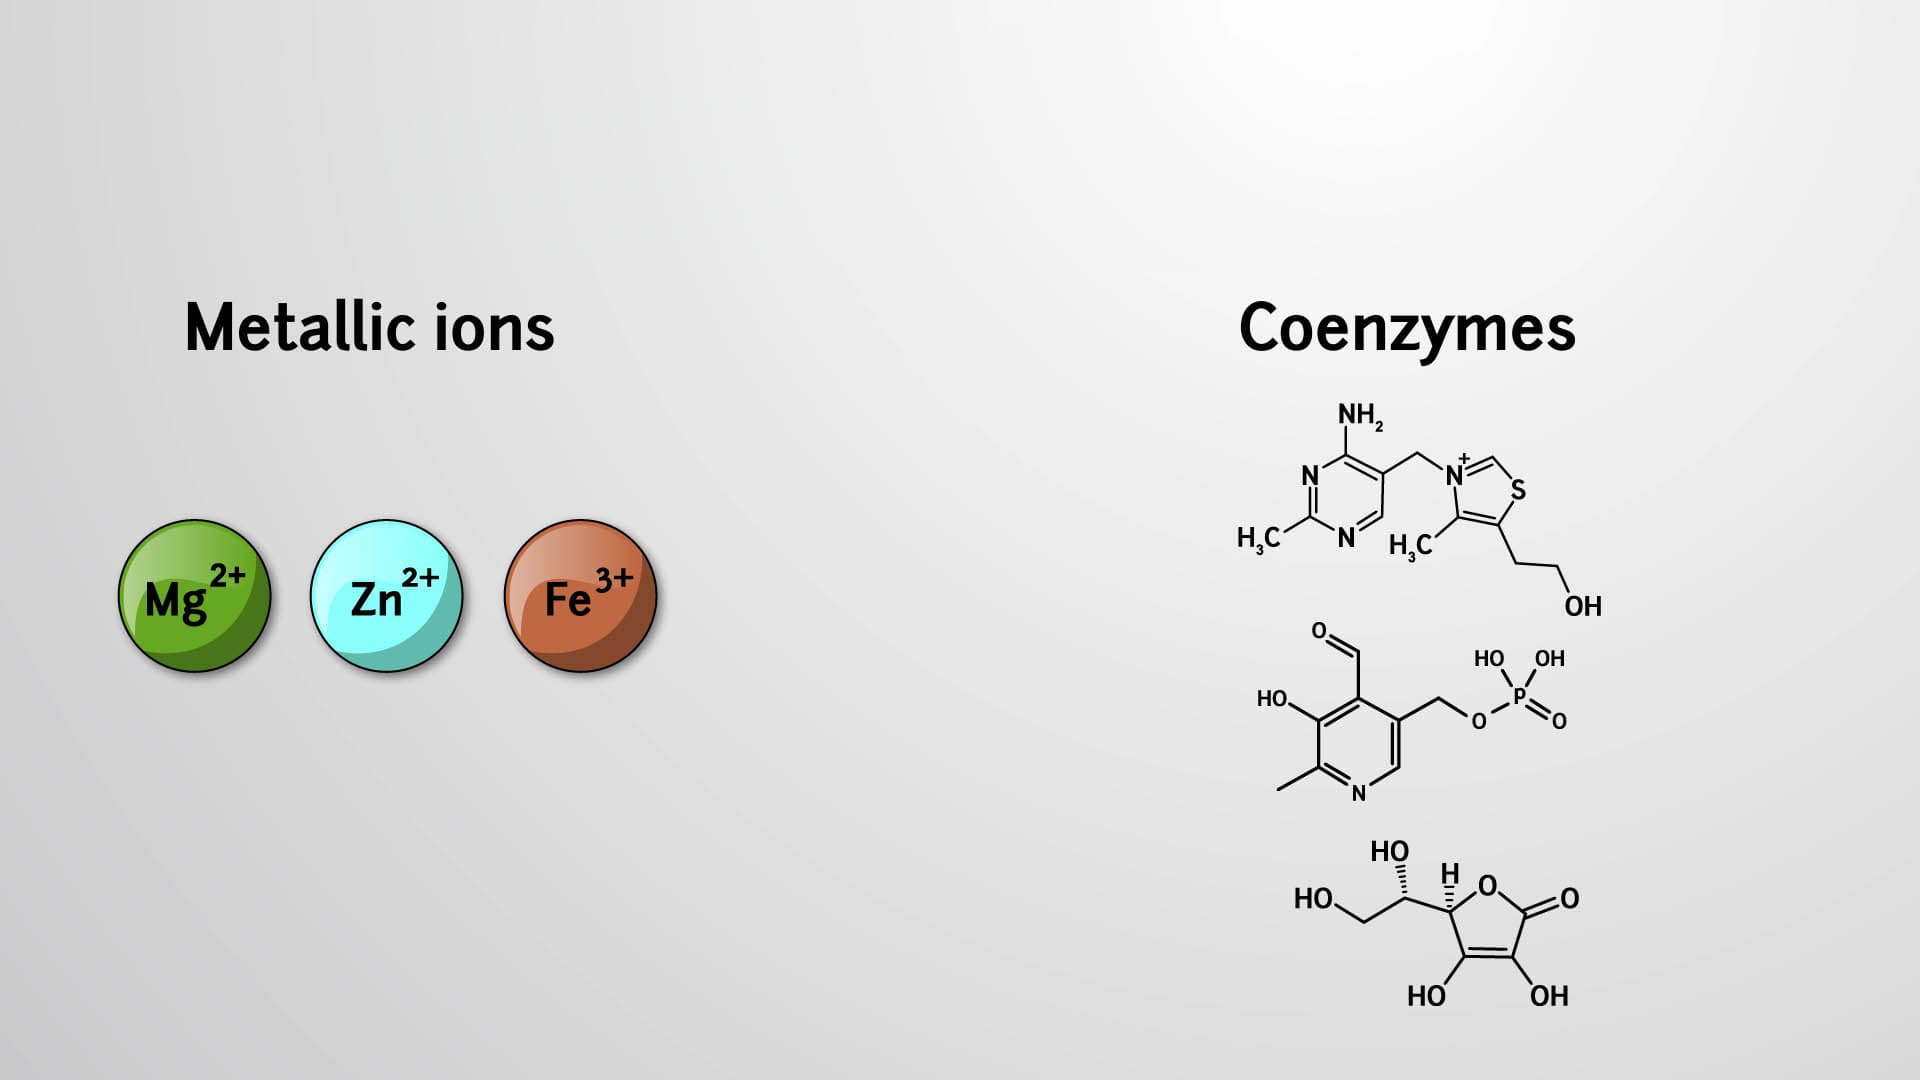
Cofactors and Coenzymes
Enzymes require additional components for proper function. There are two such classes of molecules: cofactors and coenzymes. Cofactors are metallic ions and coenzymes are non-protein organic molecules. Both of these types of helper molecule can be tightly bound to the enzyme or bound only when the substrate binds.