Related Experiment Video
Updated: May 31, 2026
New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Living donor liver transplantation with extensive caval thrombectomy for acute-on-chronic Budd-Chiari syndrome
Akihiko Soyama1, Susumu Eguchi, Katsuhiko Yanaga
1Department of Surgery, Nagasaki University Graduate School of Biomedical Sciences, 1-7-1 Sakamoto, Nagasaki, 852-8501, Japan.

Insights
Living donor liver transplantation (LDLT) for Budd-Chiari syndrome (BCS) requires managing inferior vena cava (IVC) issues. A novel thrombectomy technique successfully treated a patient with a totally thrombosed IVC, demonstrating feasibility.
Area of Science:
- Hepatology
- Transplantation Surgery
- Vascular Surgery
Background:
- Budd-Chiari syndrome (BCS) presents challenges in liver transplantation due to inferior vena cava (IVC) involvement.
- Living donor liver transplantation (LDLT) is complicated by the inability to use donor IVC for recipient IVC replacement.
Observation:
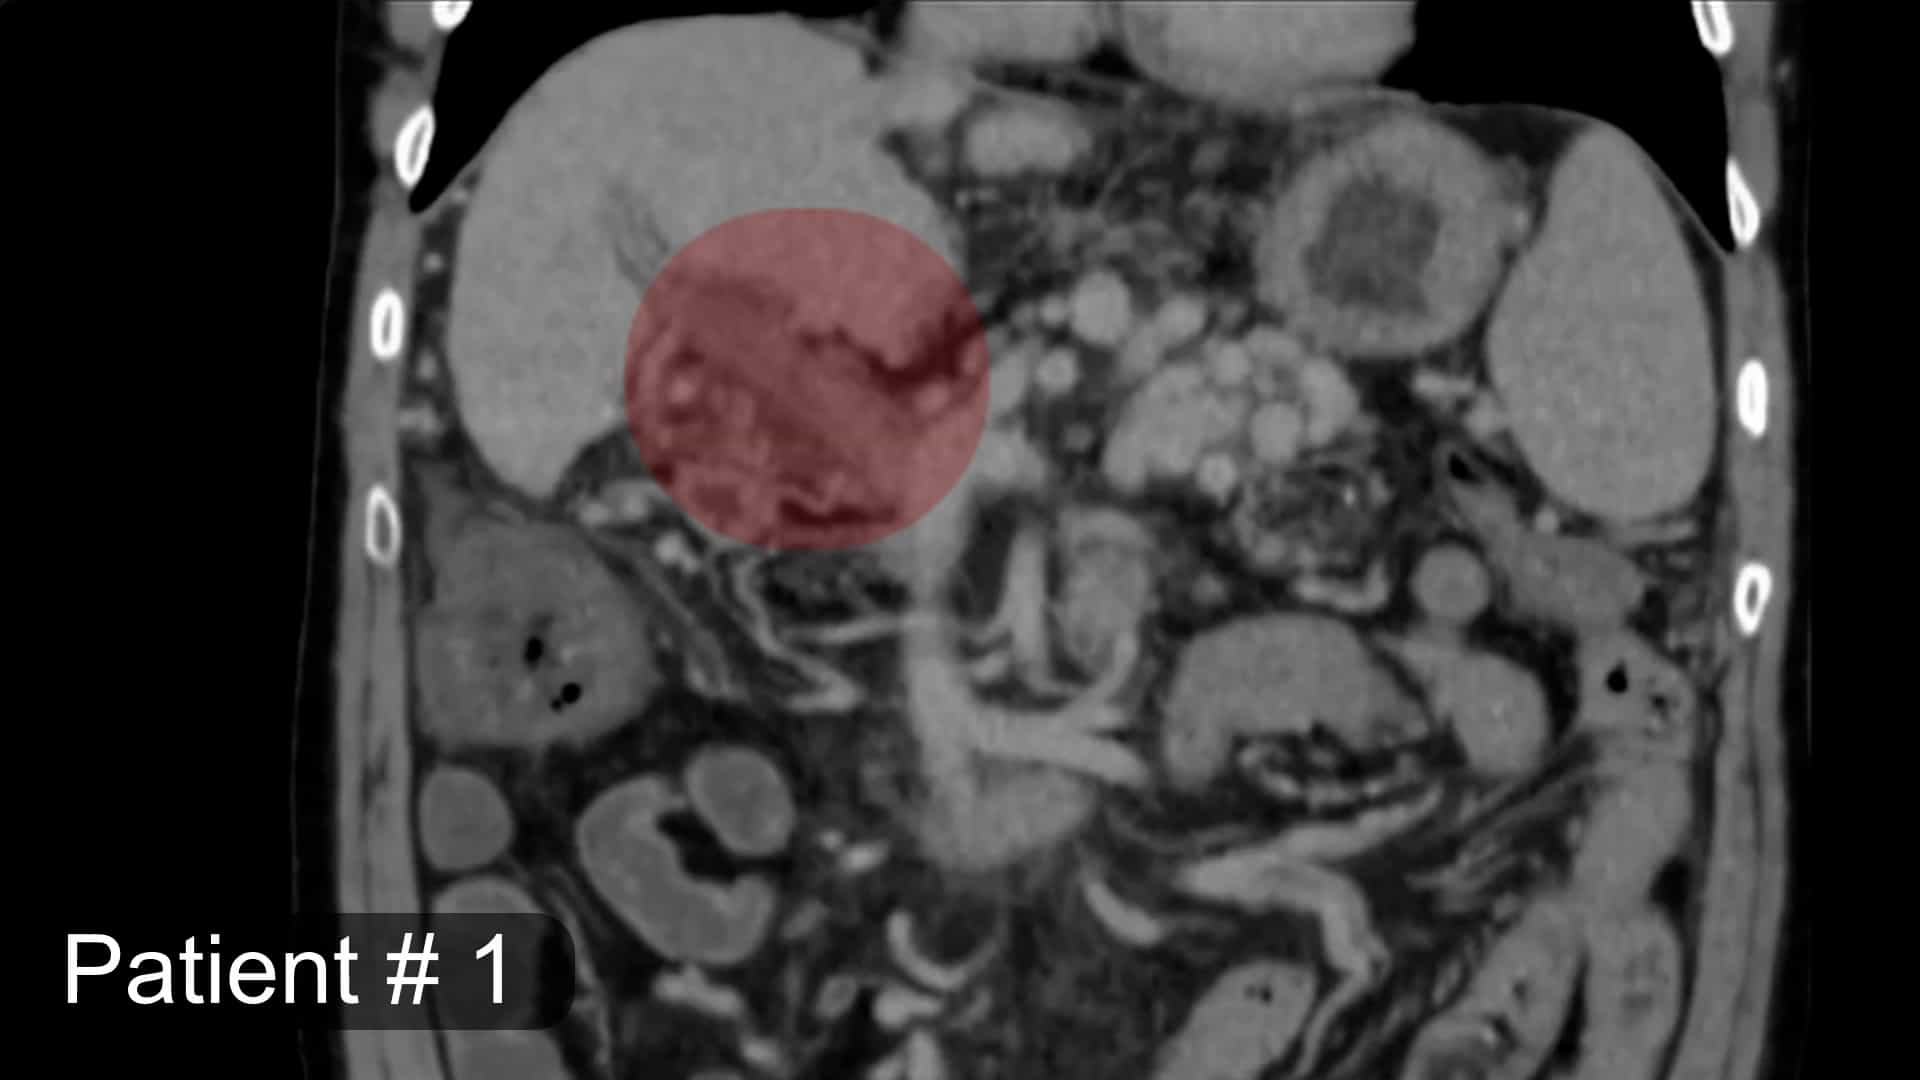
- A patient with acute-on-chronic BCS had a totally thrombosed retrohepatic IVC.
- Standard LDLT procedures are not suitable for such extensive IVC occlusion.
Findings:
- The study details a successful LDLT procedure utilizing extensive thrombectomy without a vessel graft.
- Post-operative imaging confirmed a patent IVC and hepatic veins, indicating successful management of the thrombus.
Implications:
- This technique demonstrates the feasibility of LDLT in BCS patients with severe IVC thrombosis.
- The described extensive thrombectomy offers a potential solution for managing stenotic or occluded IVCs in LDLT for BCS.
- This approach may expand LDLT candidacy for BCS patients with complex IVC pathology.
Abstract:
The key consideration when performing living donor liver transplantation (LDLT) in patients with Budd-Chiari syndrome (BCS) is careful management of a stenotic or occluded inferior vena cava (IVC), because it is not possible to replace the recipient stenotic or occluded IVC with donor IVC as in cadaver donor transplantation. We describe how we performed LDLT with extensive thrombectomy in a patient with acute-on-chronic BCS with a totally thrombosed retrohepatic IVC. The operation was successful and the patient remains well, with follow-up images showing a patent IVC and hepatic veins. To our knowledge, LDLT for a BCS patient with severe extensive caval thrombus has never been reported before. We consider that the successful outcome of this patient clearly demonstrates the feasibility of our technique of extensive thrombectomy, without a vessel graft, to manage a stenotic or occluded IVC in LDLT in patients with BCS.