Related Experiment Video
Updated: May 31, 2026
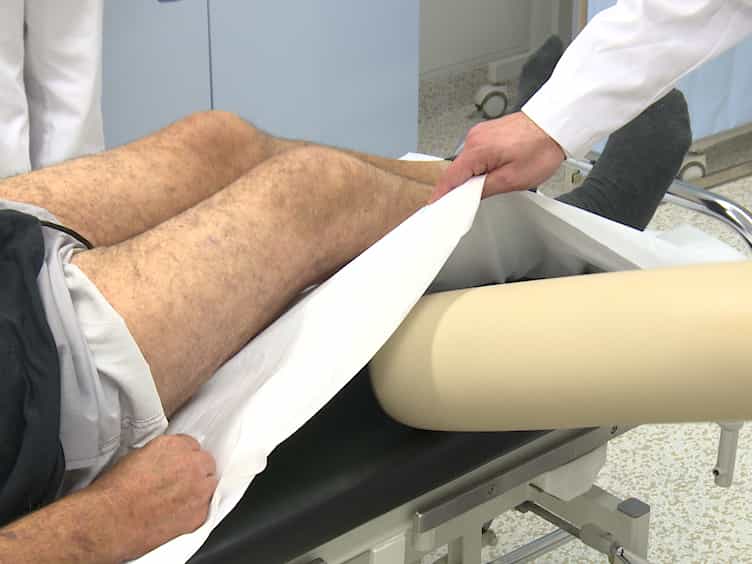

Novel Diagnostics in Revision Arthroplasty: Implant Sonication and Multiplex Polymerase Chain Reaction
Published on: December 3, 2017
Group B streptococcus in prosthetic hip and knee joint-associated infections
P Sendi1, B Christensson, I Uçkay
1Unit of Infectious Diseases, Basel University Medical Clinic Liestal, Liestal, Switzerland. sendi-pa@magnet.ch

Insights
Group B Streptococcus (GBS) periprosthetic joint infections (PJIs) are increasing in adults. Effective treatment, often involving implant removal, can lead to cure and preserved mobility.
Area of Science:
- Infectious Diseases
- Orthopedic Surgery
- Microbiology
Background:
- Invasive group B Streptococcus (GBS) infections are rising in non-pregnant adults.
- Knowledge regarding GBS periprosthetic joint infections (PJIs) is limited.
- This study investigates GBS PJI clinical presentation, treatment, and outcomes.
Purpose of the Study:
- To analyze the clinical features of GBS PJI.
- To evaluate treatment strategies for GBS PJI.
- To determine factors influencing GBS PJI outcomes.
Main Methods:
- Retrospective analysis of 36 GBS PJI cases from 10 centers.
- Follow-up data for at least 2 years on 34 episodes.
- Assessment of clinical presentation, comorbidities, surgical interventions, antimicrobial therapy, and outcomes.
Main Results:
- Most GBS PJIs (75%) occurred over 3 months post-implantation.
- High rates of comorbidities (91%), acute symptoms (69%), and soft tissue damage (83%) were observed.
- Implant removal was necessary in 56% of cases; debridement with implant retention was successful in specific scenarios (short symptom duration, stable prosthesis, minor tissue damage).
- High cure rates (94%) and functional mobility preservation (82%) were achieved.
- Adherence to a published surgical algorithm correlated with favorable outcomes (P = 0.049).
Conclusions:
- GBS PJI presents with significant comorbidities and tissue damage.
- Treatment success, particularly for debridement with implant retention, depends on early intervention and specific clinical factors.
- Surgical management following established guidelines improves outcomes in GBS PJI.
Abstract:
The incidence of invasive group B streptococcus (GBS) infections in non-pregnant adults is increasing. Little is known about GBS in periprosthetic joint infections (PJIs). We aimed to analyse the clinical presentation of GBS PJI and its treatment in association with the outcome. The characteristics of 36 GBS PJIs collected from 10 centres were investigated. In 34 episodes, follow-up examination of ≥ 2 years was available, allowing treatment and outcome analysis. Most infections (75%) occurred ≥ 3 months after implantation. Most patients (91%) had at least one comorbidity; 69% presented with acute symptoms and 83% with damaged periprosthetic soft tissue. In 20 of 34 episodes debridement and retention of implant was attempted, but in five of these the prosthesis was ultimately removed. Hence, in 19 (56%) episodes, the implant was removed, including 14 immediate removals. In four episodes the removal was permanent. Penicillin derivatives and clindamycin were the most common antimicrobials administered (68%). In 94% the infection was cured, and in 82% functional mobility preserved. Debridement with implant retention was successful if the duration of symptoms was short, the prosthesis stable, and the tissue damage minor (10/10 vs 3/10 episodes, P = 0.003). Surgery that complied with a published algorithm was associated with a favourable outcome (P = 0.049).

Related Concept Videos
 01:25
Endocarditis I: Introduction
 01:27
Streptococcal Pharyngitis
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies. Common...
 01:29
Staphylococcal Skin Infections
 01:24
Bacterial Meningitis
 01:22
Bacterial Meningitis I: Introduction