HIV infection and progression of carotid and coronary atherosclerosis: the CARE study
Related Experiment Video
Updated: May 30, 2026
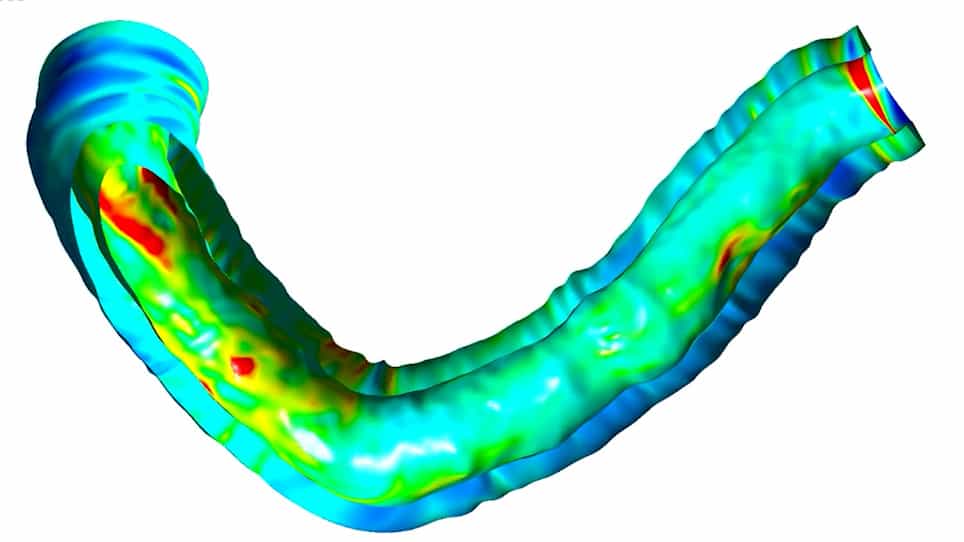
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Alexandra Mangili1, Joseph F Polak, Sally C Skinner
1Nutrition/Infection Unit, Department of Public Health and Community Medicine, Tufts University School of Medicine, Tufts Medical Center, 150 Harrison Avenue, Boston, MA 02111, USA.

Insights
Traditional cardiovascular risk factors, not HIV itself, drive atherosclerotic progression like carotid intima-media thickness (c-IMT) and coronary artery calcium (CAC) in HIV-infected adults. Aggressive risk reduction effectively slows this progression.
Area of Science:
- Cardiology
- Infectious Diseases
- Vascular Biology
Background:
- Carotid intima-media thickness (c-IMT) and coronary artery calcium (CAC) are key vascular risk surrogates.
- Assessing predictors of c-IMT and CAC progression is crucial in HIV-infected adults.
Purpose of the Study:
- To identify predictors of atherosclerotic progression (c-IMT and CAC) in a longitudinal cohort of HIV-infected adults.
- To evaluate the effectiveness of cardiovascular risk reduction strategies.
Main Methods:
- Evaluated c-IMT, CAC scores, and vascular/HIV risk factors at baseline and 3-year follow-up in 255 HIV-infected adults.
- Utilized multivariate regression to determine predictors of atherosclerotic progression.
Main Results:
- Significant predictors for common c-IMT progression included age, systolic blood pressure, triglycerides, and insulin.
- Predictors for internal c-IMT progression involved triglycerides, glucose levels, glucose-lowering medications, insulin sensitivity, waist circumference, and smoking.
- Quantitative insulin sensitivity check index, apolipoprotein B, and triglycerides predicted CAC score progression.
- 28% experienced CAC progression; 32% developed detectable CAC from zero at baseline.
Conclusions:
- Traditional cardiovascular risk factors are the primary drivers of carotid and coronary atherosclerotic disease progression in HIV-infected patients.
- Progression rates for c-IMT and CAC may be higher than expected in this population.
- Aggressive cardiovascular risk reduction is effective in slowing atherosclerotic progression in patients with existing disease.
Background:
Progression of carotid intima-media thickness (c-IMT) and coronary artery calcium (CAC) are increasingly used as surrogates for vascular risk. We assessed the predictors of c-IMT and CAC progression in a large longitudinal cohort of HIV-infected adults.
Methods:
c-IMT, CAC scores, and vascular and HIV risk factors were evaluated at baseline and at 3-year follow-up in 255 HIV-infected adults. Multivariate regression was used to determine the predictors of atherosclerotic progression.
Results:
The mean change in c-IMT per year of follow-up was 0.016 mm for the common and 0.020 mm for the internal. Significant predictors of yearly progression were age, systolic blood pressure, triglycerides, and insulin for common c-IMT and triglycerides >=150 mg/dL, glucose >126 mg/dL, use of glucose-lowering medications, quantitative insulin sensitivity check index, high waist circumference, and current smoking for internal c-IMT. Twenty-eight percent had CAC progression. Of those with zero CAC at baseline, 32% had detectable scores at follow-up. Of those with detectable CAC at baseline, 26% had progression at follow-up. For CAC score, quantitative insulin sensitivity check index, apolipoprotein B, and triglycerides predicted progression. Those with abnormal surrogate markers at baseline were more likely to have the metabolic syndrome reversed and be started on antihypertensive medications over the 3-year follow-up period than those who had no abnormalities at baseline.
Conclusions:
Although c-IMT and CAC progression rates in HIV-infected patients appear higher than expected for this age and risk groups, traditional cardiovascular risk factors remain the strongest determinants of carotid and coronary atherosclerotic disease progression in HIV-infected patients. Aggressive cardiovascular risk reduction is effective at slowing the atherosclerotic progression in those with preexisting disease.
Related Concept Videos
 01:26
Atherosclerosis III: Management
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:23
Atherosclerosis IV: Nursing Management
 01:30
Acute Coronary Syndrome III: Diagnostic Studies