Related Experiment Video
Updated: May 30, 2026
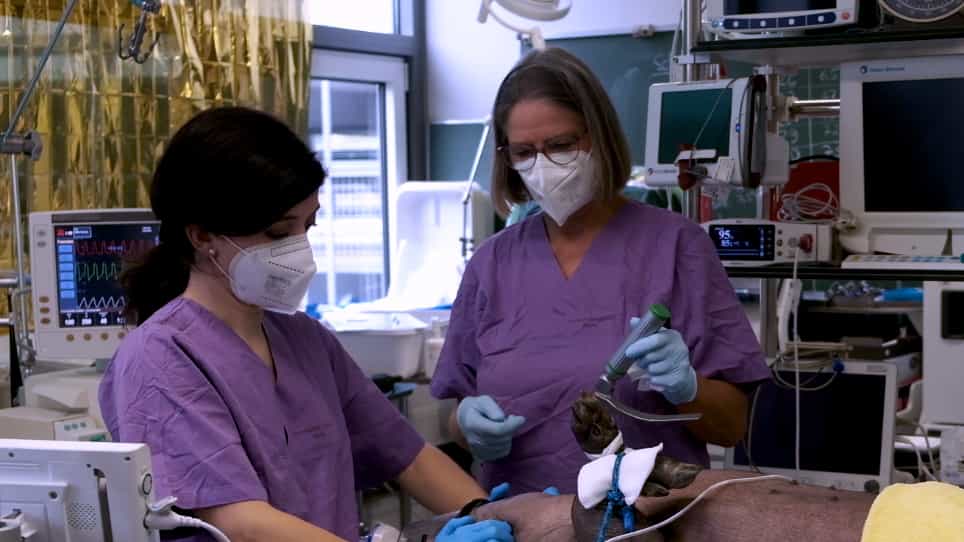

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Fiberoptic-guided tracheal tube placement through the air-Q® Intubating Laryngeal Airway: a performance study in a
Richard E Galgon1, Kristopher M Schroeder, Christopher S Schmidt
1Department of Anesthesiology, University of Wisconsin School of Medicine and Public Health, Madison, WI 53792-3272, USA. galgon@wisc.edu

Purpose:
This study characterizes the performance and success rate for fiberoptic-guided tracheal tube placement through the air-Q(®) Intubating Laryngeal Airway (air-Q).
Methods:
Using a manikin, anesthesia trainees and staff anesthesiologists, experienced in fiberoptic-guided intubation, performed five consecutive fiberoptic-guided tracheal tube placements via the air-Q. Participant characteristics, procedure segment times, total procedure times, and observed failures were recorded. Linear mixed effect models with random slopes and intercepts were used to assess participant performance.
Results:
Ten anesthesia trainees and ten staff anesthesiologists participated. Anesthesia trainees were younger and had practiced for fewer years compared to staff anesthesiologists. Gender was equally distributed between the groups. Both segmental and overall procedure times decreased from the first to the fifth trial among all participants, independent of experience level and gender. Overall mean procedure time decreased from 102 ± 31 to 68 ± 14 s, representing a relative time reduction of 33% and a mean time difference of 34 s [95% confidence interval (CI) 22-47 s; p < 0.0001]. Tracheal tube placement was successful in all attempts; however, three tracheal tube dislodgements occurred during air-Q removal (overall procedure success 97%).
Conclusions:
Fiberoptic-guided tracheal tube placement through the air-Q can be performed in a clinically acceptable period of time with high success by operators skilled in fiberoptic-guided intubation. Tracheal tube dislodgement during air-Q removal remains a potential risk that should be emphasized.


Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.