

Is there a necessity for individual blood water corrections when conductivity-based access blood flow measurements
Shih-Han S Huang1, Paul A Heidenheim, Kerri Gallo
1Division of Nephrology, Department of Medicine, University of Western Ontario, and London Health Sciences Centre, London, ON, Canada.

Background/Aims:
Access blood water flow rate (Qaw) can be measured during hemodialysis using an online effective ionic dialysance (EID) methodology. Fresenius employ this methodology in their 2008K dialysis machine. The machine computer converts Qaw to an access blood flow rate (Fresenius Qa) using a generic blood water constant (BWC). We wished to validate this BWC.
Methods:
18 patients had Fresenius Qa measurements using the EID and these were compared with a 'gold standard' ultrasound dilution methodology (Transonic Qa). Qa values were also obtained by removing the BWC from Fresenius Qa values to obtain the Qaw and recorrecting it with individualized patient factors using hematocrit and total protein values (HctTp Qa). The measurements were repeated after 1 h.
Results:
There were no significant differences between Fresenius and Transonic, nor between HctTp and Transonic Qa values (p > 0.17). There were strong correlations between both sets of values (r > 0.856; p < 0.001). There was a significant correlation between the pairs of Transonic Qa values (r = 0.823; p < 0.007), but not for Fresenius Qa pairs (r = 0.573; p > 0.07). It was surmised that the BWC was not valid post-dialysis.
Conclusion:
The generic BWC is comparable to individualized blood water correction factors when Qa measures are made early in dialysis and prior to ultrafiltration treatment.

Related Concept Videos
 01:28
Capillary Exchange
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:29
Blood Flow
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:27
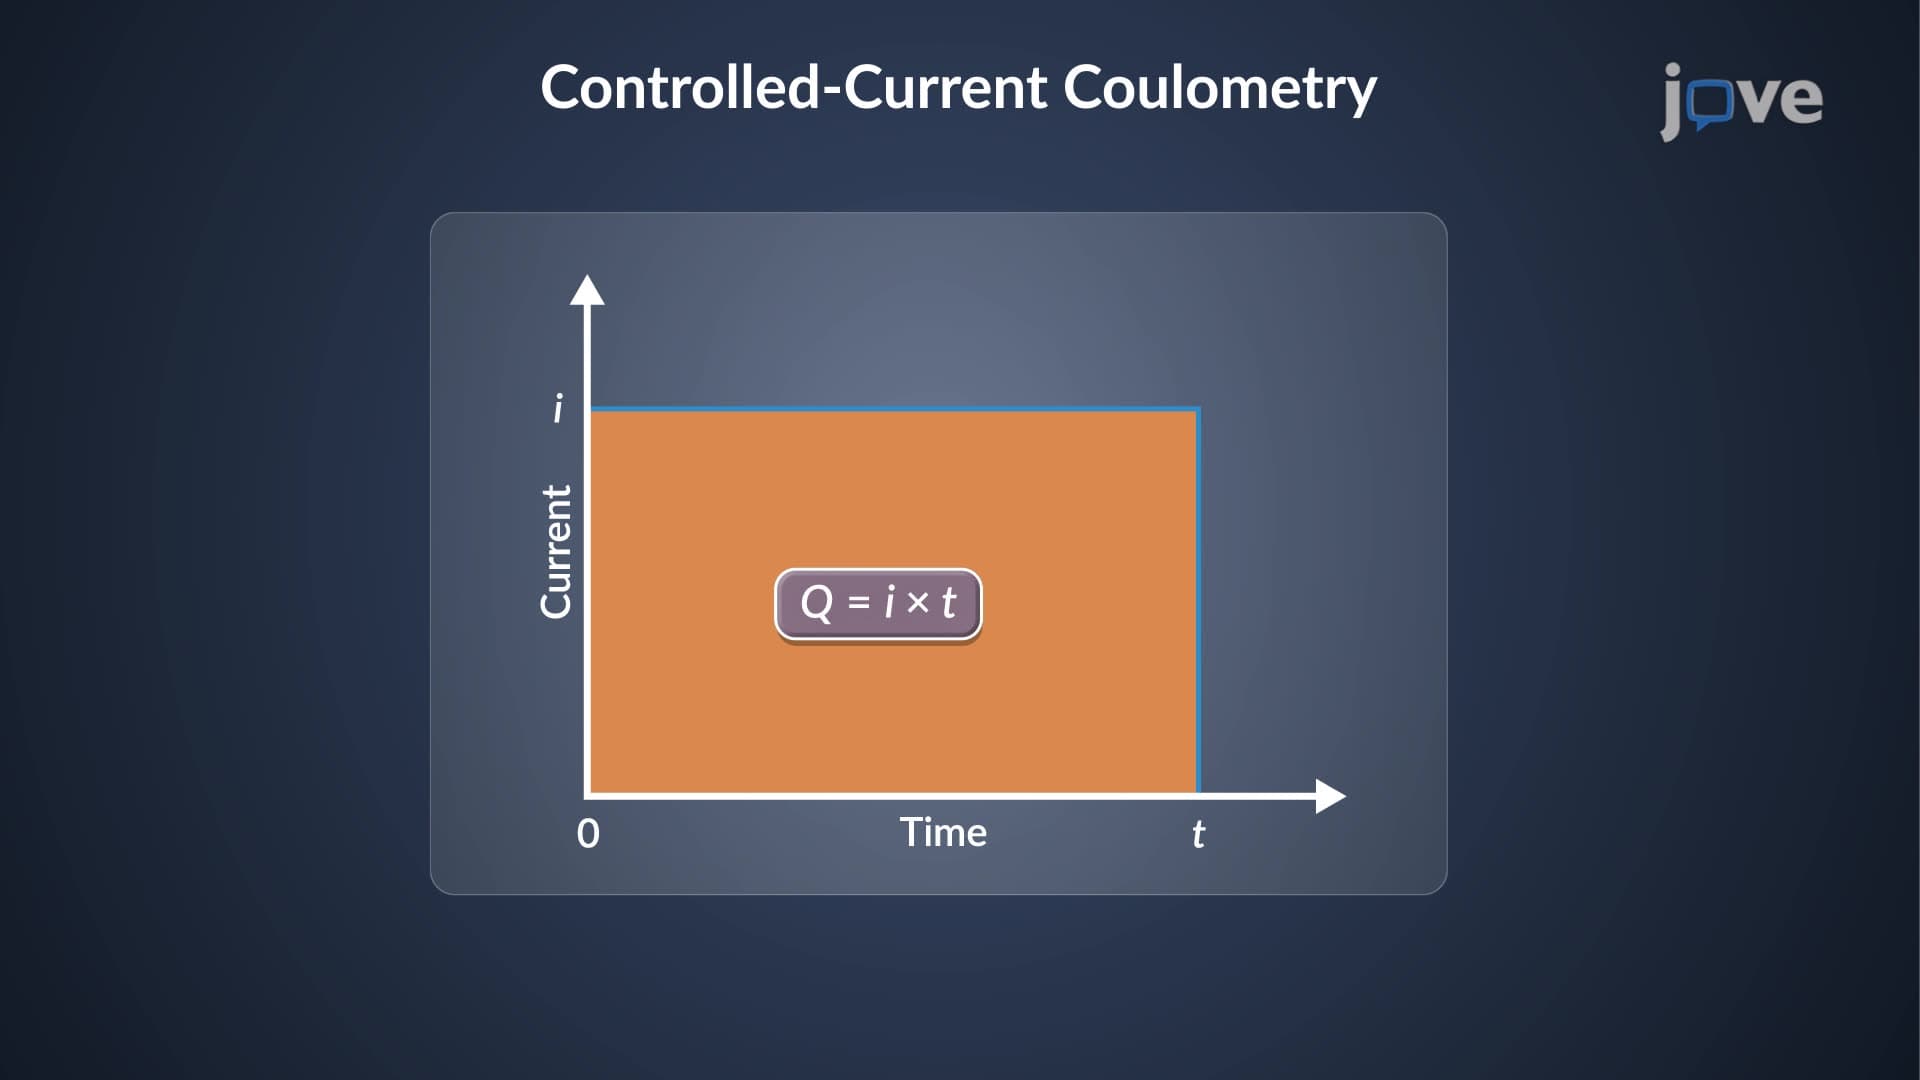
Controlled-Current Coulometry: Overview