Related Experiment Video
Updated: May 30, 2026
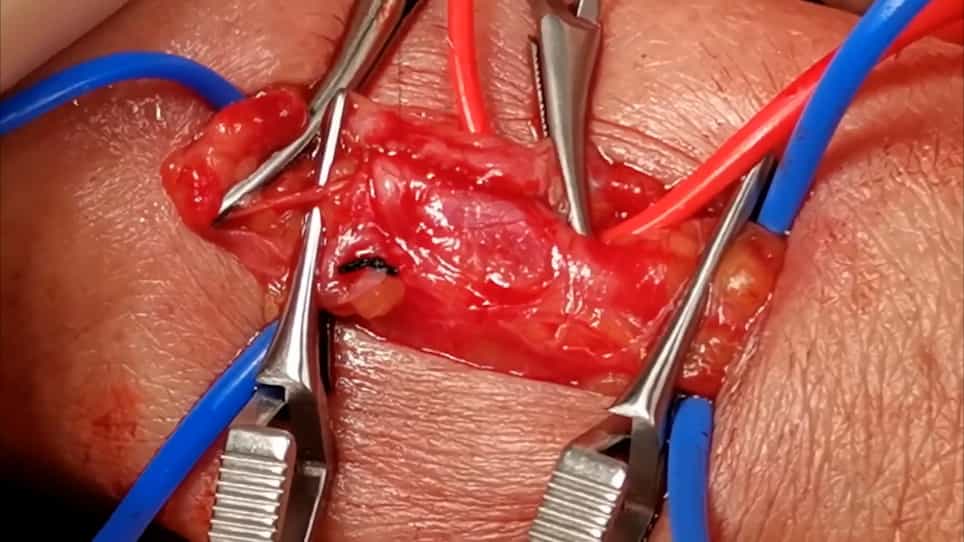

Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Hemodialysis vascular access options after failed Brescia-Cimino arteriovenous fistula
Aneesh Srivastava1, Sandeep Sharma
1Department of Urology and Renal Transplantation, Sanjay Gandhi Postgraduate Institute of Medical Sciences, Lucknow, Uttar Pradesh, India.

The survival of patients on long-term hemodialysis has improved. End-stage renal disease patients now need maintenance of their vascular access for much longer periods. Arteriovenous fistulae formed at the wrist are the first choice for this purpose, but, in many patients, these fistulae fail over time or are not feasible because of thrombosed veins. We searched the Pubmed database to evaluate the various options of vascular access in this group of patients based on the published literature. It is quite evident that, whenever possible, autogenous fistulae should be preferred over prosthetic grafts. Use of upper arm cephalic and basilic veins with transpositions wherever required can enhance autogenous fistula options to a large extent. Upper arm grafts should be used when no autogenous fistula is possible. Lower limb and body wall fistula sites are to be considered at the end, when all options in both upper limbs are exhausted.
The survival of patients on long-term hemodialysis has improved. End-stage renal disease patients now need maintenance of their vascular access for much longer periods. Arteriovenous fistulae formed at the wrist are the first choice for this purpose, but, in many patients, these fistulae fail over time or are not feasible because of thrombosed veins. We searched the Pubmed database to evaluate the various options of vascular access in this group of patients based on the published literature. It is quite evident that, whenever possible, autogenous fistulae should be preferred over prosthetic grafts. Use of upper arm cephalic and basilic veins with transpositions wherever required can enhance autogenous fistula options to a large extent. Upper arm grafts should be used when no autogenous fistula is possible. Lower limb and body wall fistula sites are to be considered at the end, when all options in both upper limbs are exhausted.

Related Concept Videos
 01:25
Hemodialysis I: Introduction
 01:30
Continuous Renal Replacement Therapy
 01:24
Hemodialysis II: Procedure and Complications
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:29
Venous Thrombosis III: Interprofessional Care
 01:25
Hemodialysis III: Nursing Management