Related Experiment Video
Updated: May 30, 2026
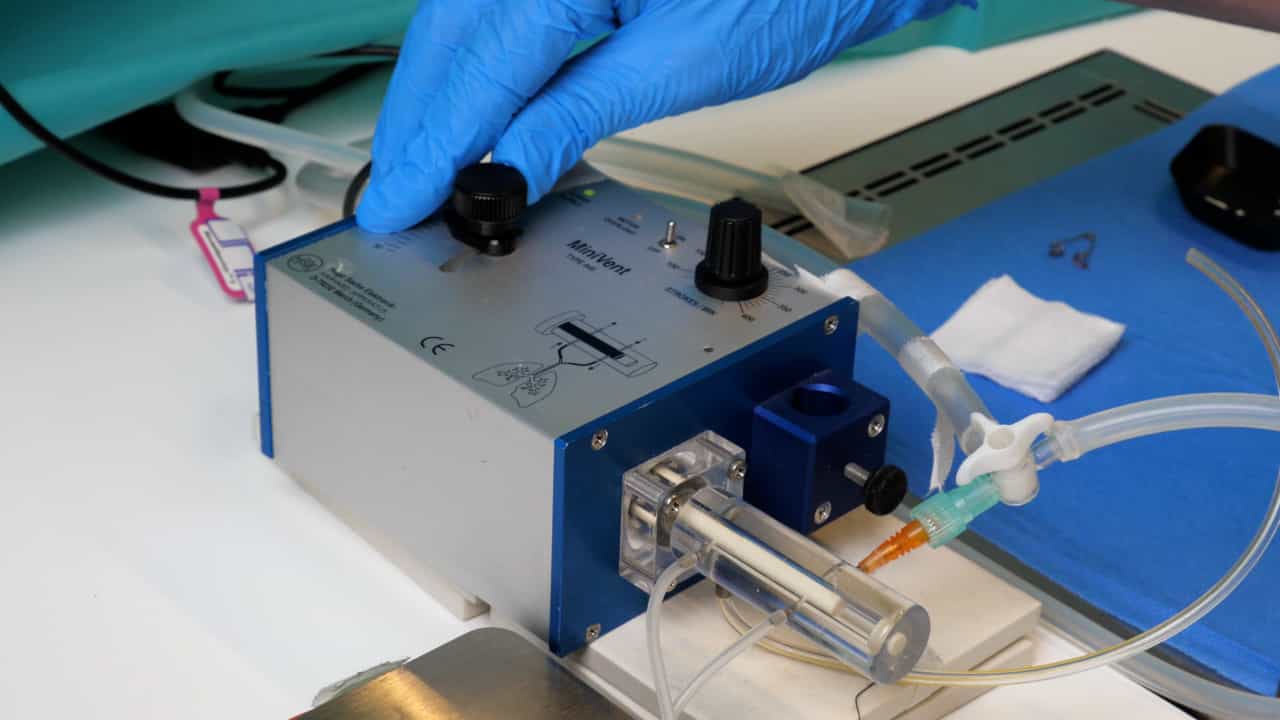

Remotely Triggered LAD Occlusion Using a Balloon Catheter in Spontaneously Breathing Mice
Published on: March 22, 2024
Left circumflex occlusion in acute myocardial infarction (from the National Cardiovascular Data Registry)
W Kyle Stribling1, Michael C Kontos, Antonio Abbate
1Virginia Commonwealth University, Richmond, USA. wkstrib@yahoo.com

Insights
Acute left circumflex artery occlusion often presents without ST-elevation myocardial infarction (STEMI). Patients with non-STEMI (NSTEMI) LCx occlusion have lower in-hospital mortality than those with STEMI.
Area of Science:
- Cardiology
- Interventional Cardiology
- Acute Coronary Syndromes
Background:
- Acute left circumflex (LCx) artery occlusion typically presents with ST-segment elevation less than 50% of the time, potentially delaying treatment.
- Limited contemporary data exists on the clinical outcomes of patients with LCx territory occlusion who do not have ST-segment elevation myocardial infarction (STEMI).
Purpose of the Study:
- To compare clinical outcomes, including in-hospital mortality, between patients with STEMI and non-STEMI (NSTEMI) due to acute LCx territory occlusion.
- To identify factors influencing outcomes in LCx occlusion presenting as STEMI versus NSTEMI.
Main Methods:
- Retrospective analysis of 27,711 patients with myocardial infarction and acute LCx territory occlusion treated with percutaneous coronary intervention (PCI) from April 2004 to June 2009.
- Exclusion of patients with prior coronary artery bypass grafting.
- Logistic generalized estimating equation modeling was used to compare outcomes between STEMI and NSTEMI groups, adjusting for baseline characteristics.
Main Results:
- Of 27,711 patients, 67% presented with STEMI and 33% with NSTEMI.
- Patients with STEMI were more likely to have proximal LCx culprit lesions (63% vs 27%).
- Risk-adjusted in-hospital mortality was significantly greater in the STEMI group compared to the NSTEMI group (OR 1.36, 95% CI 1.12-1.65).
Conclusions:
- Acute LCx territory occlusion frequently presents as NSTEMI.
- Patients with NSTEMI LCx occlusion exhibit a lower in-hospital mortality risk compared to those with STEMI.
- Potential contributing factors to lower NSTEMI mortality include myocardium involved, lesion location, and dual blood supply.
Abstract:
Compared to occlusions of other major coronary arteries, patients presenting with acute left circumflex (LCx) occlusion usually have ST-segment elevation on the electrocardiogram <50% of the time, potentially delaying treatment and resulting in worse outcomes. In contemporary practice, little is known about the clinical outcomes of patients with LCx territory occlusion without ST-segment elevation myocardial infarction (STEMI). We identified patients with myocardial infarction from April 2004 to June 2009 in the CathPCI Registry treated with percutaneous coronary intervention for culprit LCx territory occlusion, excluding those with previous coronary artery bypass grafting. Logistic generalized estimating equation modeling was used to compare the outcomes, including in-hospital mortality between patients with STEMI and non-STEMI (NSTEMI) adjusting for differences in the baseline characteristics. Of the 27,711 patients with myocardial infarction and acute LCx territory occlusion, 18,548 (67%) presented with STEMI and 9,163 (33%) with NSTEMI. With the exception of a greater proportion of cardiac risk factors and cardiac history in the NSTEMI group, the demographic and baseline characteristics were clinically similar between the 2 groups, despite the statistical significance resulting from the large population. The patients with STEMI were more likely to have a proximal LCx culprit lesion (63% vs 27%, p <0.0001) and had greater risk-adjusted in-hospital mortality (odds ratio 1.36, 95% confidence interval 1.12 to 1.65, p = 0.002) compared to patients with NSTEMI. In conclusion, acute LCx territory occlusion often presents as NSTEMI, but patients with NSTEMI and occlusion have a lower mortality risk than those with STEMI, possibly because of factors such as the amount of myocardium involved, the lesion location along the vessel, and/or a dual blood supply.

Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and narrowing...