Related Experiment Video
Updated: May 30, 2026


Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Unusual case of 'trapped fourth ventricle' in a child with posthemorrhagic hydrocephalus--lessons learnt
Suhas Udayakumaran1, Liana Beni Adani
1Department of Pediatric Neurosurgery, Dana Children's Hospital, Tel Aviv Sourasky Medical Center, Tel Aviv University, Tel Aviv, Israel.

Insights
A rare dermoid tumor in the fourth ventricle was found in a child with cerebral palsy and posthemorrhagic hydrocephalus. This highlights the need for careful imaging and assessment in neurologically compromised children to avoid delayed diagnosis.
Area of Science:
- Pediatric Neurology
- Neuro-oncology
- Developmental Pediatrics
Background:
- Posthemorrhagic hydrocephalus (PHH) and cerebral palsy (CP) are common in premature infants, requiring multidisciplinary follow-up.
- Imaging in these children typically focuses on ventricles and tissue damage, potentially overlooking rare pathologies.
Observation:
- A 3-year-old child with spastic CP secondary to prematurity and PHH, who had a ventriculoperitoneal shunt, presented with neurological changes.
- Follow-up imaging showed a persistent large fourth ventricle. A repeat MRI revealed a cystic lesion in the fourth ventricle, prompting surgical exploration.
Findings:
- Surgical exploration identified a large dermoid tumor within the fourth ventricle.
- Differential diagnosis for a large fourth ventricle in shunted PHH/CP patients includes cerebellar atrophy, isolated fourth ventricle, cystic lesions, and neoplasms.
Implications:
- Neurologically compromised children present diagnostic challenges, necessitating regular clinical assessment and timely, protocol-driven imaging.
- This case underscores the importance of considering rare pathologies, like fourth ventricle dermoid tumors, in the management of complex pediatric neurological conditions to prevent diagnostic delays and improve outcomes.
Abstract:
In most of the children with posthemorrhagic hydrocephalus (PHH), multidisciplinary follow-up is performed, with the focus on consequences of prematurity, cerebral palsy (CP) and hydrocephalus. A large fourth ventricle is common in these children but imaging performed in order to document ventricles and tissue damage is not oriented to exclude coexisting rare pathologies. We report a 3-year-old child with spastic CP, secondary to prematurity and PHH. A ventriculoperitoneal shunt was inserted at the age of 2 months. On follow-up imaging the child demonstrated well-drained supratentorial ventricles with a persistent large fourth ventricle. Because of a neurological change in spasticity and new-onset torticollis, a repeat MRI was performed, suggesting a cystic, nonenhancing lesion of the fourth ventricle. The surgical exploration revealed a large dermoid of the fourth ventricle. We analyze the differential diagnosis of a clinically significant large fourth ventricle in a shunted child with PHH and CP. This includes conditions without pressure in the posterior fossa such as tissue loss due to cerebellar atrophy, or pathologies causing a true increase in pressure of the fourth ventricle (isolated fourth ventricle, cystic lesions and neoplasms of the fourth ventricle). Neurologically compromised children pose additional challenges in reaching a definitive diagnosis and hence require a careful regular assessment of their clinical status with additional well-timed imaging with appropriate protocols to allow appropriate treatment when indicated and to avoid morbidity due to delayed diagnosis. We present a rare coexistence of a dermoid tumor within the fourth ventricle in a CP child with PHH and express the dilemmas associated with its management.

Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:18
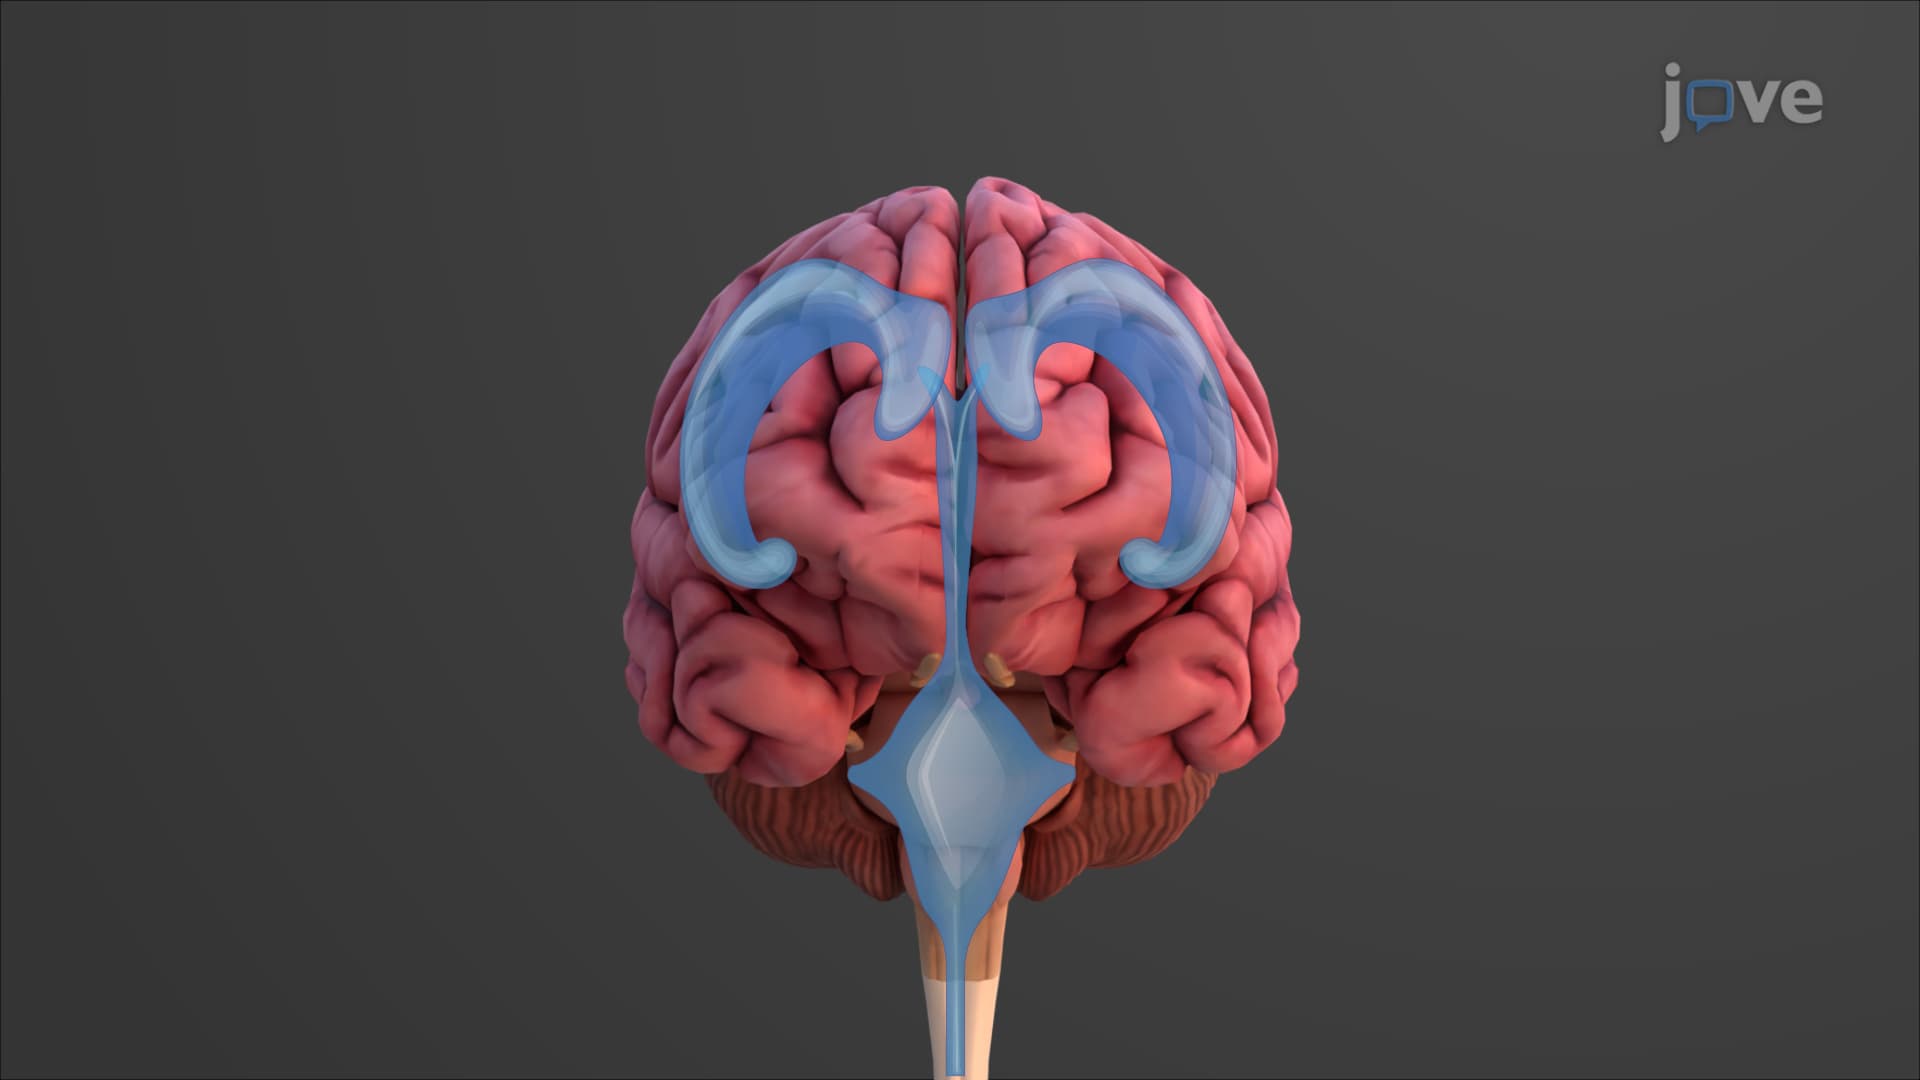
Anatomy of the Brain: Ventricles
 01:22
Cerebral Edema ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction