Related Experiment Video
Updated: May 30, 2026

Adapting Human Videofluoroscopic Swallow Study Methods to Detect and Characterize Dysphagia in Murine Disease Models
Published on: March 1, 2015
Development of pharyngo-esophageal physiology during swallowing in the preterm infant
N Rommel1, M van Wijk, B Boets
1Centre for Pediatric & Adolescent Gastroenterology, Children, Youth & Women's Health Service, Women's and Children's Hospital, North Adelaide (SA), Australia. nathalie.rommel@med.kuleuven.be

Insights
Preterm infants show developing pharyngeal motility and upper esophageal sphincter (UES) function. Poor coordination between pharyngeal propulsion and UES relaxation in young infants impacts feeding effectiveness and hospitalization duration.
Area of Science:
- Neonatal physiology
- Swallowing biomechanics
- Pediatric gastroenterology
Background:
- Poor feeding is a primary cause of extended hospitalization for preterm infants.
- Pharyngeal and upper esophageal sphincter (UES) function in preterm infants is poorly understood due to assessment challenges.
Purpose of the Study:
- To investigate the developmental trajectory of pharyngeal motility.
- To characterize upper esophageal sphincter (UES) function during nutritive swallowing in preterm infants.
- To analyze the coordination between pharyngeal and UES activity.
Main Methods:
- High-resolution manometry was employed to assess swallowing in 18 preterm infants.
- Measurements were taken weekly from the first oral feeding attempt (31-32 weeks gestation) for four weeks.
- Analysis included 980 swallows, characterizing pharyngeal and UES pressure dynamics.
Main Results:
- An age-related increase in peak pharyngeal pressure was observed.
- The time for UES relaxation decreased with age.
- Youngest infants exhibited uncoordinated swallowing, with the UES not fully relaxed during peak pharyngeal propulsion.
Conclusions:
- Swallowing physiology in preterm infants demonstrates developmental changes linked to feeding efficiency.
- Immature pharyngeal pressures and poor coordination of pharyngeal propulsion with UES relaxation are common.
- These findings may explain feeding difficulties, choking, and fatigue in infants under 34 weeks gestation.
Background:
Poor feeding is a common cause of prolonged hospitalization of preterm infants. Pharyngeal and upper esophageal sphincter (UES) function of preterm infants has been technically difficult to assess and is therefore poorly characterized. The aim of this study was to assess the development of pharyngeal motility, UES function, and their coordination during nutritive swallowing in preterm infants.
Methods:
Development of swallowing was assessed in 18 preterm infants. High resolution manometry was performed at first oral feeding attempt (31-32 week) and then weekly for 4 weeks. Pharyngeal and UES pressure changes were characterized in 980 swallows.
Key Results:
During swallowing, we observed an age-related increase in peak pharyngeal pressure at the laryngeal inlet (1 cm above UES) but an age-related decrease in the time required for the UES to fully relax to nadir. Analysis of the timing of proximal pharyngeal contractile peak and UES nadir showed that the UES was not fully relaxed when bolus propulsive forces were at their peak in the youngest infants.
Conclusions & Inferences:
Results show developmental changes in infant swallow physiology that can be clearly linked to the effectiveness of nutritive swallowing. Most preterm infants demonstrated poor pharyngeal pressures at the laryngeal inlet coupled with poor coordination of pharyngeal propulsion with UES relaxation. These pressure patterns were less efficient than those demonstrated by older infants who were more adept at feeding. These observations may explain why infants under 34 weeks are physiologically unable to feed effectively and experience frequent choking and fatigue during feeding.


Related Concept Videos
 01:22
Physiology of the Gastrointestinal System I: Ingestion and Propulsion
 01:25
Deglutition
Swallowing can be divided into three stages: the voluntary phase, the pharyngeal phase, and the esophageal phase. Although the...
 01:24
Esophagus
The movement of edibles from the pharynx into the esophagus is facilitated by the upper esophageal sphincter, which is formed primarily by the...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:27
Esophageal Achalasia
 01:20
Pharynx
Nasopharynx
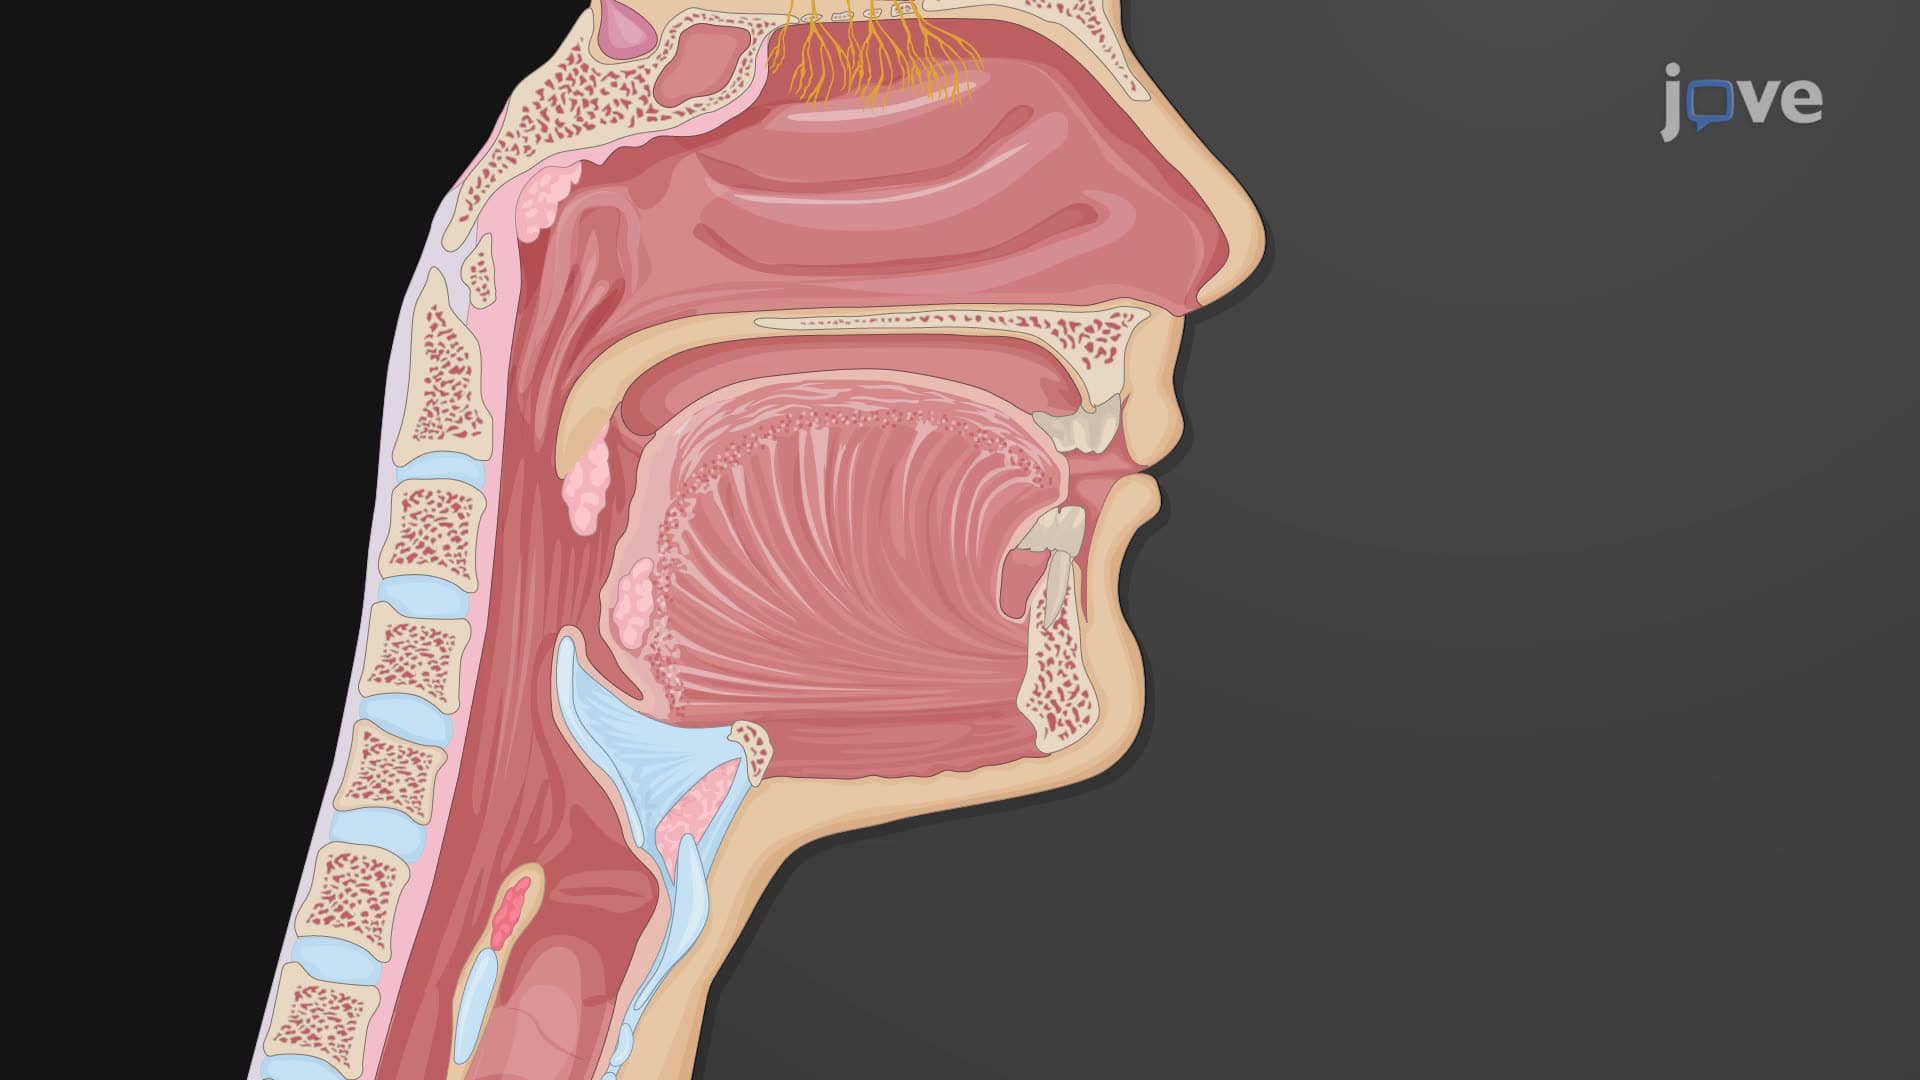
The nasopharynx, bordered by the conchae of the nasal cavity, serves exclusively as an air conduit. In its superior region, the pharyngeal tonsils or adenoids are located. These tonsils are clusters of lymphoid reticular tissue akin to a lymph node. The precise...