Related Experiment Video
Updated: May 30, 2026
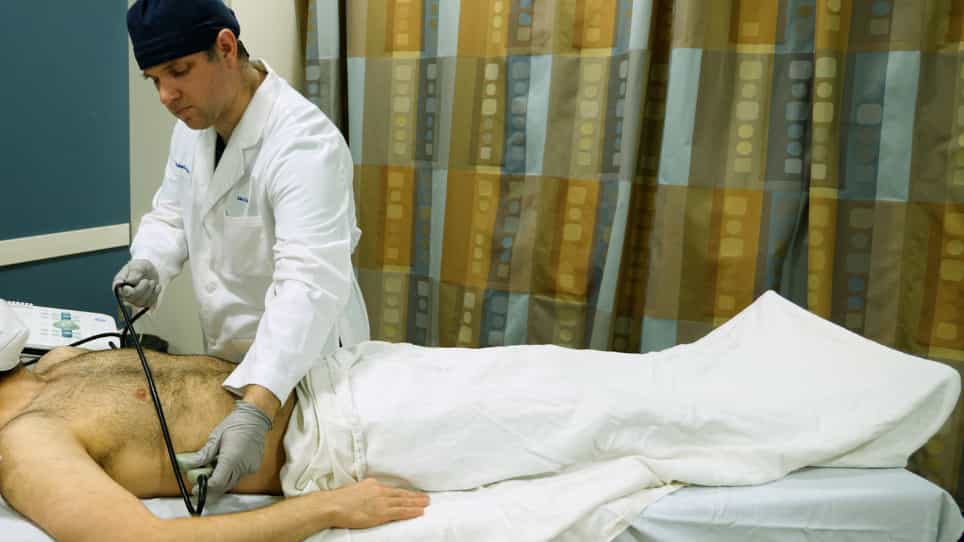
Focused Assessment with Sonography for Trauma (FAST) Exam: Image Acquisition
Published on: September 22, 2023
High-velocity penetrating thoracic trauma with suspected cardiac involvement in a combat support hospital
Francisco Dominguez1, Alec C Beekley, Linda L Huffer
1Cardiology Service MCHE-MDC, Brooke Army Medical Center, 3851 Roger Brooke Drive, San Antonio, TX 78234-6200, USA.

Purpose:
The most common cardiac injuries in the United States are blunt trauma from motor vehicle accidents or low-velocity trauma from stabbings. During military conflict, high-velocity injuries, including gunshot wounds (GSW) and fragment injury from improvised explosive devices (IED), are relatively more common.
Methods:
This is a retrospective review of cases with high-velocity penetrating injury and suspected myocardial involvement during a 6-month period in Baghdad, Iraq, at a United States Army hospital during Operation Iraqi Freedom.
Results:
Eleven cases survived to admission (GSW in 5, IED in 6). The mean age of the all-male cohort was 27 years (range, 3-54 years). Eight of the 11 patients (73%) were victims of polytrauma. The entrance involved the right ventricle (n = 3), right atrium (n = 2), left ventricle (n = 1), or mediastinum and pericardial reflections (n = 5). Echocardiography was performed in all 11 patients. In 7 patients, no foreign body was identifiable, and in 2 patients the foreign body was identified within the pericardial fat pad. Three patients were identified as having a suspected ventricular septal defect, ranging in size from 2 to 8 mm. The most common electrocardiographic abnormality was atrioventricular block and right bundle branch block. In 4 patients, the management of the chest injury was nonsurgical, and in 1 patient the treatment was a chest tube only. Four of the patients underwent median sternotomy, 1 underwent emergent lateral thoracotomy, and 1 underwent an infradiaphragmatic approach.
Conclusion:
This case series is too small to draw definitive conclusions; however, a multidisciplinary approach to high-velocity injuries with potential for cardiac involvement augments preoperative assessment for myocardial injury and may allow selective nonoperative management.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:30
Introduction Cardiac Emergencies
 01:08
Pneumothorax II: Pathophysiology