Related Experiment Video
Updated: May 30, 2026


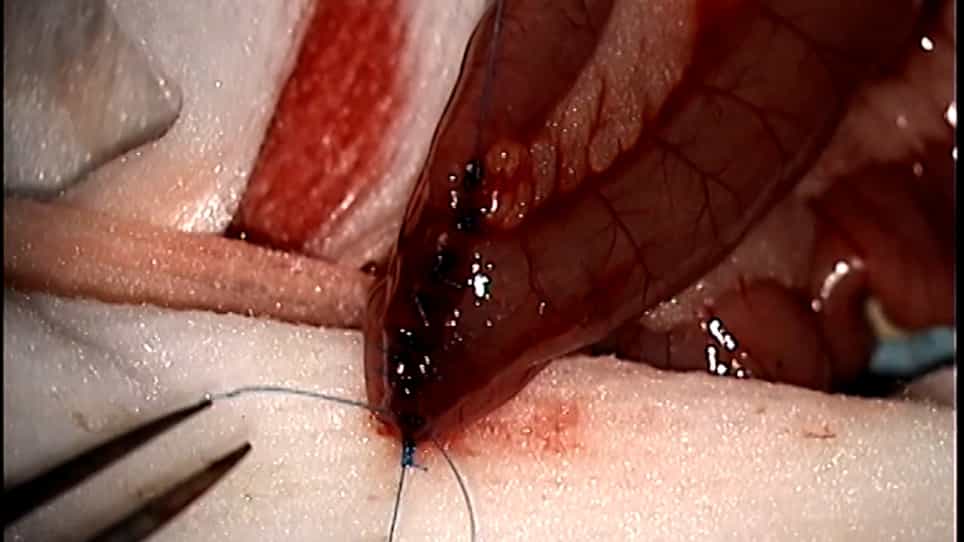
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Effects of Roux-en-Y operations on glucose homeostasis in obese GK rats
Xueli Zhang1, Wenhai Huang, Yong Zhang
1Department of General Surgery, Central Hospital of Fengxian District, 9588 Nan Feng Road, Shanghai 201400, China. zhangxueli_2010@sina.cn

Aim:
To investigate the therapeutic effects of different styles of gastric bypass surgery on type 2 diabetes mellitus (T2DM) GK rats.
Methods:
Twenty 6-8-week-old male GK rats were randomly divided into four groups: group A was operated by Roux-en-Y gastrojejunostomy with duodenum exclusion and stomach capacity maintenance, group B was operated by loop-type gastrojejunostomy with duodenum exclusion and stomach capacity maintenance, group C was operated by Roux-en-Y gastrojejunostomy with partial gastrectomy, and group D was operated by loop-type gastrojejunostomy with partial gastrectomy. Changes of fasting blood glucose, oral glucose tolerance test (OGTT), and insulin tolerance test (ITT) in different operations were detected.
Results:
The operations exerted good effects on controlling blood glucose in groups A, B, C, and D. There was no significant difference between groups A and C (P > 0.05) or between groups B and D (P > 0.05), while operations in groups A and C were more effective than groups B and D (P < 0.05). On the 21st day after surgery, OGTT in animals of groups A and C was significantly improved, as indicated by a 34% reduction in the area under the curve (AUC) for blood glucose (P < 0.05 versus groups B and D); pregavage insulin levels (ng/ml) were significantly decreased in groups A and C (P < 0.05 versus groups B and D). The insulin tolerance test (ITT) confirmed impaired insulin sensitivity in groups B and D, compared with groups A and C.
Conclusions:
Gastric bypass surgery might be effective to treat type 2 diabetes mellitus (T2DM), and Roux-en-Y gastrojejunostomy might be more effective than other operative styles.

Related Concept Videos
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:02
Glucose Homeostasis: Regulation of Blood Glucose
During fasting, when blood glucose levels are low, the pancreas secretes glucagon. it...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:29
Hyperglycemia
 01:24
Type II Diabetes II: Pathophysiology