Related Experiment Video
Updated: May 30, 2026
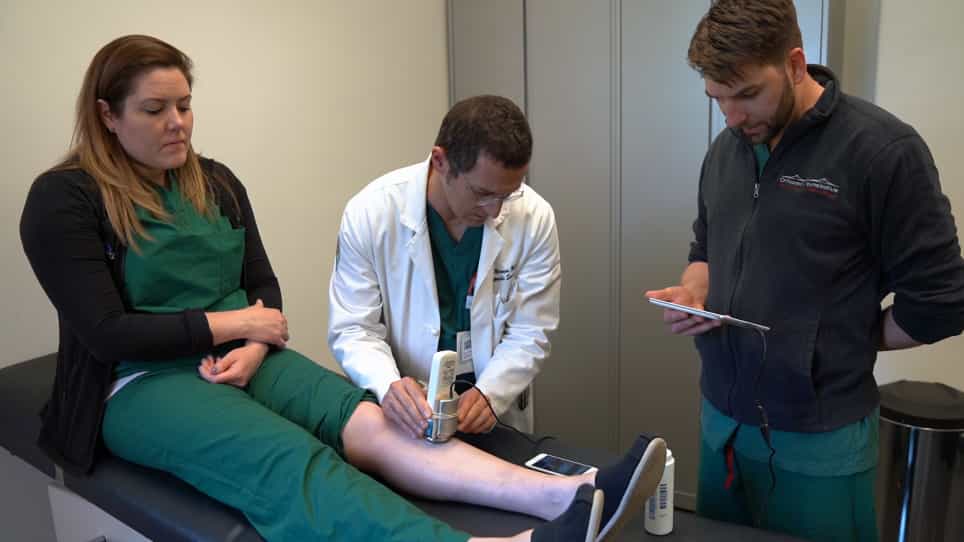

A Novel Non-invasive Method for the Detection of Elevated Intra-compartmental Pressures of the Leg
Published on: May 31, 2019
The effect of abdominal wall plication on intra-abdominal pressure and lower extremity venous flow: a case report
Christopher J Pannucci1, Amy K Alderman, Sandra L Brown
1Section of Plastic Surgery, University of Michigan, Ann Arbor, MI 48109, USA. cpannucc@umich.edu

Abdominal wall plication is known to cause increased intra-abdominal pressure (IAP). Whether plication-associated increased IAP causes lower extremity venous stasis, a recognized risk factor for DVT, remains unknown. A 55-year-old woman had a unilateral pedicled TRAM procedure for mastectomy reconstruction. Prior to plication, duplex ultrasound measured proximal femoral vein (PFV) cross-sectional diameter and volume-flow. PFV measurements were repeated immediately after plication and on post-operative days (POD) 1, 2, and 4. Bladder pressure was measured at similar timepoints. PFV volume-flow decreased from 0.22 L/min to 0.16 L/min (73% of baseline) immediately post-plication and reached a nadir of 0.08 L/min (36% of baseline) on POD 2. Bladder pressure increased from 13 mm Hg to 19 mm Hg after plication, and peaked at 31 mm Hg after intra-operative trunk flexion to 30°. Thus, abdominal wall plication was associated with increased intra-abdominal pressure and ultrasound-documented lower extremity venous stasis that persisted for 48 h after surgery.
Abdominal wall plication is known to cause increased intra-abdominal pressure (IAP). Whether plication-associated increased IAP causes lower extremity venous stasis, a recognized risk factor for DVT, remains unknown. A 55-year-old woman had a unilateral pedicled TRAM procedure for mastectomy reconstruction. Prior to plication, duplex ultrasound measured proximal femoral vein (PFV) cross-sectional diameter and volume-flow. PFV measurements were repeated immediately after plication and on post-operative days (POD) 1, 2, and 4. Bladder pressure was measured at similar timepoints. PFV volume-flow decreased from 0.22 L/min to 0.16 L/min (73% of baseline) immediately post-plication and reached a nadir of 0.08 L/min (36% of baseline) on POD 2. Bladder pressure increased from 13 mm Hg to 19 mm Hg after plication, and peaked at 31 mm Hg after intra-operative trunk flexion to 30°. Thus, abdominal wall plication was associated with increased intra-abdominal pressure and ultrasound-documented lower extremity venous stasis that persisted for 48 h after surgery.

Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:26
Varicose Veins I: Introduction
 01:30
Venous Thrombosis IV: Nursing Management
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation