Bivalirudin for anticoagulation during hypothermic cardiopulmonary bypass and recombinant factor VIIa for iatrogenic coagulopathy
Related Experiment Video
Updated: May 30, 2026
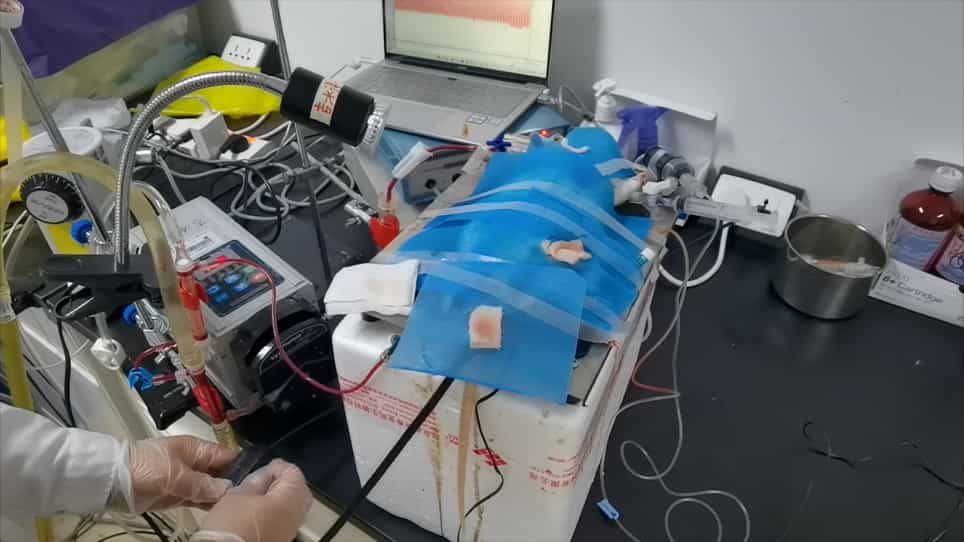
Establishment of Deep Hypothermic Circulatory Arrest in Rats
Published on: December 16, 2022
Erin L Nagle1, Laura V Tsu, William E Dager
1University of California, Davis Medical Center, Sacramento, CA, USA.

Objective:
To describe management of anticoagulation with a decreased dose requirement of bivalirudin during cardiopulmonary bypass using deep hypothermic circulatory arrest (DHCA) and the reversal of the ensuing coagulopathy with recombinant factor VIIa (rFVIIa).
Case Summary:
A 48-year-old male developed chest pain, hypertension, and an aortic aneurysm requiring urgent surgical repair. At the time of surgery, the patient reported an allergy to heparin, so bivalirudin was used for anticoagulation (1 mg/kg loading dose, followed by intermittent infusions of 1.25-2.5 mg/kg/h over the 5 hours of cardiopulmonary bypass). When the cooling process was initiated, bivalirudin was stopped in anticipation of loss of the clotting cascade function and potential slowing of drug elimination. Bivalirudin was restarted for 45 minutes during the rewarming period because of concern for potential clot formation in the bypass circuit with recovery of hemostasis; it was again stopped due to the patient's activated clotting time (ACT) of 504 seconds. Despite this measure, diffuse and severe coagulopathy was observed upon rewarming, with ACTs longer than 999 seconds. Although multiple blood products were administered, visualization of a clot in the surgical field was not notable. A total dose of rFVIIa 20 μg/kg was administered, resulting in visual clot formation within 4 minutes. On postsurgical day 6, bilateral asymptomatic distal deep vein thromboses were noted on imaging; on postsurgical day 8, fondaparinux 2.5 mg subcutaneously was administered daily to prevent clot extension. The patient was discharged on postoperative day 23 with no acute issues and no further anticoagulants.
Discussion:
Alternative anticoagulation agents such as bivalirudin are used in patients who have an allergy or contraindication to heparin. We propose that prolonged coagulopathy after the induction of hypothermia is due to decreased clotting cascade function as well as slowing of protease activity resulting in decreased bivalirudin elimination. We observed a positive response to low-dose rFVIIa, which could be due to activation of the extrinsic pathway and/or a thrombin burst, resulting in hemostasis. Currently, there is limited evidence supporting reversal of direct thrombin inhibitors with rFVIIa.
Conclusions:
In the setting of DHCA, bivalirudin should be used cautiously, with frequent monitoring of the ACTs and potential cessation of the infusion in anticipation of prolonged drug effect with subsequent potential coagulopathy. If coagulopathy ensues, use of low-dose rFVIIa may be an option to initiate hemostasis. When using rFVIIa, it is important to consider the risk of thrombosis and monitor patients accordingly.


Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:22
Heart Failure VI: Adjunct Therapies