Related Experiment Video
Updated: May 30, 2026
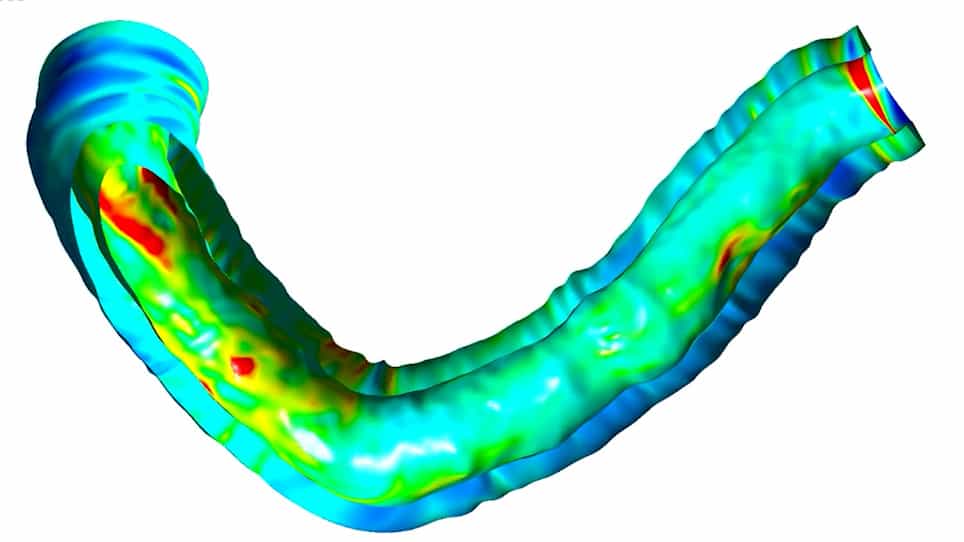

Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Association between biologic therapies for chronic plaque psoriasis and cardiovascular events: a meta-analysis of
Caitriona Ryan1, Craig L Leonardi, James G Krueger
1Department of Dermatology, Baylor Research Institute, 3900 Junius St, Ste 125, Dallas, TX 75246, USA. caitriona.ryan@baylorhealth.edu

Context:
Ustekinumab and briakinumab, monoclonal antibodies to the shared p40 subunit of interleukin (IL)-12 and IL-23, have shown efficacy in treating chronic plaque psoriasis (CPP). Preliminary reports of major adverse cardiovascular events (MACEs) in psoriasis patients receiving anti-IL-12/23 agents have prompted concern.
Objective:
To evaluate a possible association between biologic therapies for CPP and MACEs via meta-analysis.
Data Sources:
Randomized controlled trials (RCTs) of anti-IL-12/23 (ustekinumab and briakinumab) agents and anti-tumor necrosis factor α (TNF-α) agents (adalimumab, etanercept, and infliximab) used in treating CPP were reviewed using the Cochrane Central Register of Controlled Trials, ClinicalTrials.gov, and Ovid MEDLINE from database inception to May 2011. The results of registered nonpublished completed studies were procured through abstract publications or poster presentations.
Study Selection:
Randomized, placebo-controlled, double-blind, monotherapy studies (with safety outcome data for MACE) of IL-12/23 antibodies and anti-TNF-α agents in adults. Studies of psoriatic arthritis were excluded.
Data Extraction:
Two investigators independently searched data while 6 investigators reviewed the abstracted data.
Results:
A total of 22 RCTs comprising 10 183 patients met the predefined inclusion criteria. The primary outcome measure was MACE, a composite end point of myocardial infarction, cerebrovascular accident, or cardiovascular death during the placebo-controlled phase of treatment in patients receiving at least 1 dose of study agent or placebo. Absolute risk differences were used as an effect measure. There was no evidence of statistical heterogeneity across the studies using the I(2) statistic (I(2) = 0), allowing for combination of trial results using the Mantel-Haenszel fixed-effects method. During the placebo-controlled phases of the anti-IL-12/23 studies, 10 of 3179 patients receiving anti-IL-12/23 therapies experienced MACEs compared with zero events in 1474 patients receiving placebo (Mantel-Haenszel risk difference, 0.012 events/person-year; 95% confidence interval [CI], -0.001 to 0.026; P =.12). In the anti-TNF-α trials, only 1 of 3858 patients receiving anti-TNF-α agents experienced a MACE compared with 1 of 1812 patients receiving placebo (Mantel-Haenszel risk difference, -0.0005 events/person-year; 95% CI, -0.010 to 0.009; P = .94).
Conclusions:
Compared with placebo, there was no significant difference in the rate of MACEs observed in patients receiving anti-IL-12/IL-23 antibodies or anti-TNF-α treatments. This study may have been underpowered to identify a significant difference.
Related Concept Videos
 01:26
Atherosclerosis III: Management
 01:27
Psychoneuroimmunology: Cardiovascular Disease
A key area of focus in PNI is the relationship between stress and coronary...
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:30
Coronary Artery Disease I: Introduction
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...