Related Experiment Video
Updated: May 29, 2026
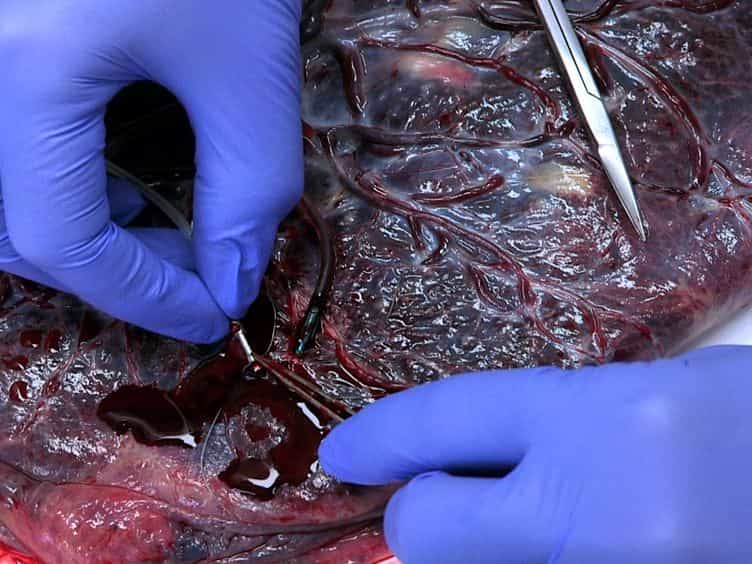

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
The transfer of 6-mercaptopurine in the dually perfused human placenta
J R Hutson1, A Lubetsky, A Walfisch
1Division of Clinical Pharmacology and Toxicology, Hospital for Sick Children, 555 University Ave, Toronto, Ontario M5G 1X8, Canada.

The immunosuppressant azathioprine is increasingly being used in pregnancy. The human placenta is considered a relative barrier to the major metabolite, 6-mercaptopurine (6-MP), and likely explains the lack of proven teratogenicity in humans. The aim of this study was to determine how the human placenta restricts 6-MP transfer using the human placental perfusion model. After addition of 50 ng/ml (n=4) and 500 ng/ml (n=3) 6-MP into the maternal circulation, there was a biphasic decline in its concentration and a delay in fetal circulation appearance. Under equilibrative conditions, the fetal-to-maternal concentration ratio was >1.0 as a result of ion trapping. Binding to placental tissue and maternal pharmacokinetic parameters are the main factors that restrict placental transfer of 6-MP. Active transport is unlikely to play a significant role and drug interactions involving, or polymorphisms in, placental drug efflux transporters are not likely to put the fetus at risk of higher 6-MP exposure.
The immunosuppressant azathioprine is increasingly being used in pregnancy. The human placenta is considered a relative barrier to the major metabolite, 6-mercaptopurine (6-MP), and likely explains the lack of proven teratogenicity in humans. The aim of this study was to determine how the human placenta restricts 6-MP transfer using the human placental perfusion model. After addition of 50 ng/ml (n=4) and 500 ng/ml (n=3) 6-MP into the maternal circulation, there was a biphasic decline in its concentration and a delay in fetal circulation appearance. Under equilibrative conditions, the fetal-to-maternal concentration ratio was >1.0 as a result of ion trapping. Binding to placental tissue and maternal pharmacokinetic parameters are the main factors that restrict placental transfer of 6-MP. Active transport is unlikely to play a significant role and drug interactions involving, or polymorphisms in, placental drug efflux transporters are not likely to put the fetus at risk of higher 6-MP exposure.


Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase