Related Experiment Video
Updated: May 29, 2026
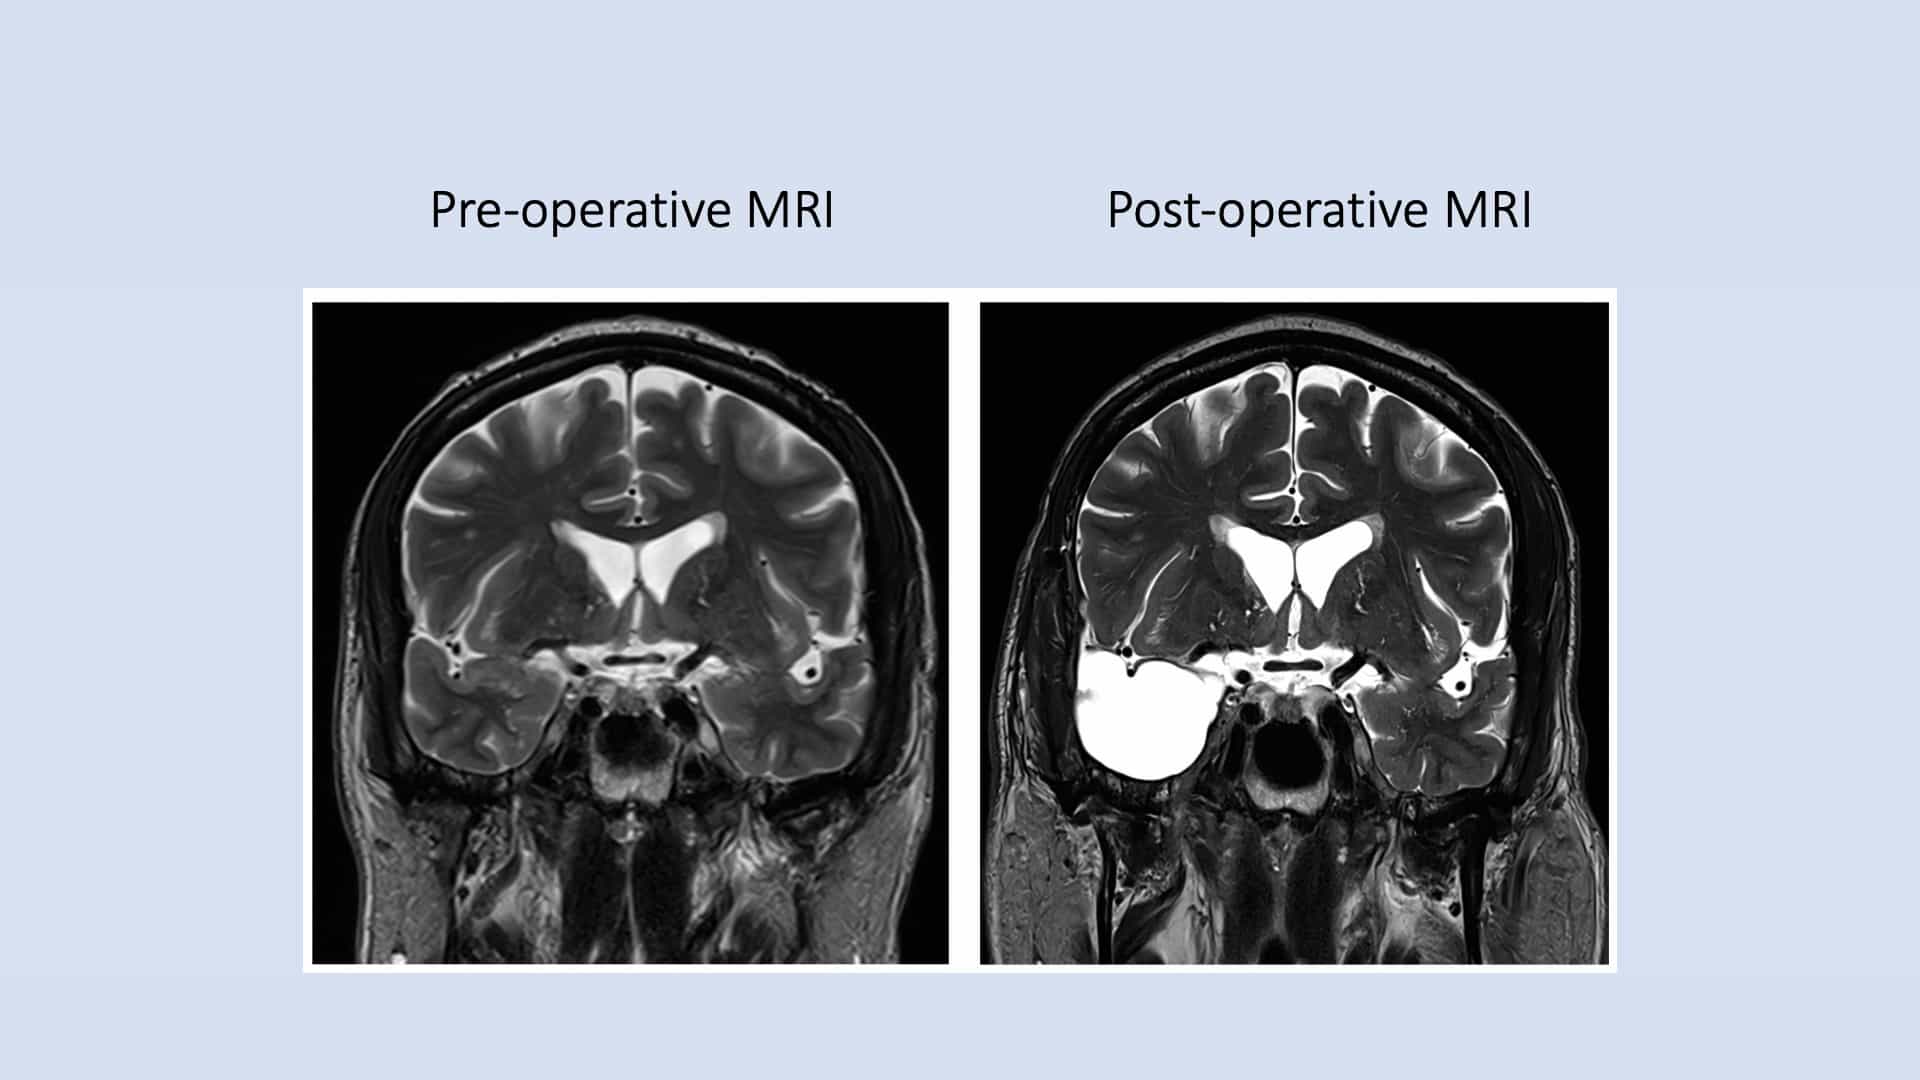

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Epilepsy surgery of the temporal lobe in pediatric population: a retrospective analysis
Miguel Angel Lopez-Gonzalez1, Jorge Alvaro Gonzalez-Martinez, Lara Jehi
1Department of Neurosurgery, Neurological Institute, Cleveland Clinic, Cleveland, Ohio 44195, USA. lopezm5@ccf.org

Insights
Pediatric epilepsy surgery offers long-term seizure control with low complication rates. Extensive surgical resection is the key predictor of successful outcomes in pediatric temporal lobe epilepsy (TLE).
Area of Science:
- Pediatric Neurology
- Neurosurgery
- Epileptology
Background:
- Referral for epilepsy surgery in pediatric patients remains low despite proven efficacy.
- Retrospective studies indicate positive outcomes for epilepsy surgery in children.
Purpose of the Study:
- To detail surgical outcomes and long-term results for pediatric temporal lobe epilepsy (TLE) at a single center.
- To identify predictors of surgical success in pediatric TLE.
Main Methods:
- Retrospective review of pediatric TLE patients (<18 years) who underwent surgery from 1996-2006.
- Cox proportional hazard modeling analyzed factors influencing surgical outcomes.
- Kaplan-Meier survival analysis assessed seizure freedom rates.
Main Results:
- 130 pediatric patients were analyzed; mean seizure onset to surgery was 6.3 years.
- Seizure-freedom rates at 12 years were 41%. 75.3% achieved Engel class I outcome.
- Complication rate was 7%; reoperation rate was 3.1%. Extensive resection was the sole significant predictor of favorable outcomes.
Conclusions:
- Careful patient selection through multidisciplinary evaluation is crucial for pediatric epilepsy surgery.
- Successful long-term seizure control can be achieved with low complication rates in pediatric TLE.
- Extensive surgical resection is vital for optimal outcomes.
Background:
There is still some reluctance to refer pediatric patients for epilepsy surgery, despite evidence of success in retrospective series.
Objective:
To describe surgical experience and long-term outcome in pediatric temporal lobe epilepsy (TLE) at a single institution.
Methods:
Retrospective review of pediatric (<18-years-old) TLE patients who underwent surgery between November 1996 and December 2006 at Cleveland Clinic Epilepsy Center. Cox proportional hazard modeling was used to assess outcome predictors.
Results:
One hundred thirty pediatric patients met study criteria. Mean time between seizure onset and surgery was 6.3 years. Invasive evaluation was used in 32 patients (24.5%). Hippocampal sclerosis was present in 70 patients (53.8%), either alone or associated in dual pathology. The complication rate was 7%. The seizure-freedom rates at 1, 2, 5, and 12 years were 76%, 72%, 54%, and 41%, respectively (Kaplan-Meier). With the use of the Engel outcome classification, 98 (75.3%) patients were class I, 11 (8.5%) class II, 9 (7%) class III, and 12 (9.2%) were class IV at last follow-up. Only 4 (3.1%) patients underwent reoperations. Antiepileptic drugs (AEDs) were discontinued in 36 patients (28.3%) in a mean period of 18 months (SD ± 17 months; range, 6-102 months). Although left-sided resection, lower number of preoperative AED trials (≤ 4), and tumor pathology correlated with favorable seizure outcomes, extensive surgical resection remained the only significant outcome predictor after multivariate analysis (P = .007; HR = 0.13 [95% confidence interval 0.007-0.64]).
Conclusion:
Careful selection of surgical candidates by multidisciplinary evaluations is required. Long-term seizure control is achieved successfully with acceptable low complication rates.
Related Concept Videos
 01:22
Epilepsy ll: Types
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types: