Related Experiment Video
Updated: May 29, 2026
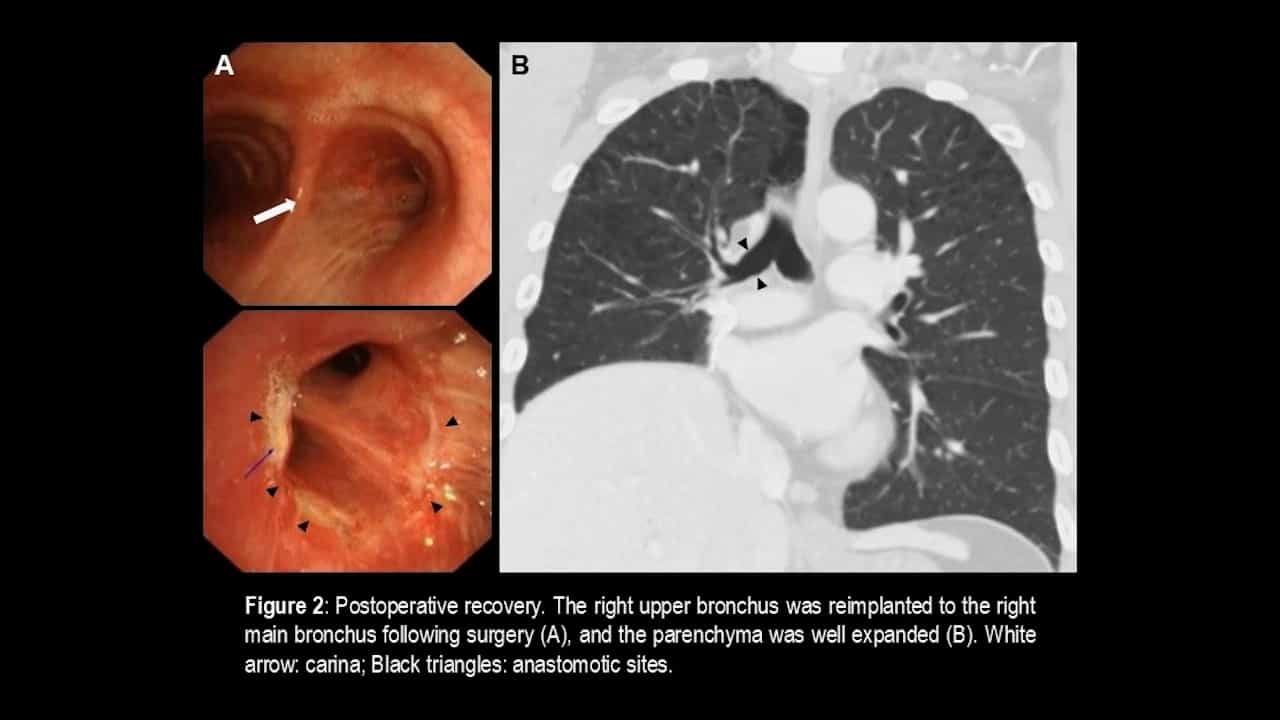
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Safety-net burden hospitals and likelihood of curative-intent surgery for non-small cell lung cancer
Katherine S Virgo1, Alex G Little, Stacey A Fedewa
1Health Services Research Department, American Cancer Society, National Home Office, Atlanta, GA, USA.

Background:
Black patients are less likely to undergo surgery for early-stage non-small cell lung cancer (NSCLC) compared with white patients, and are more likely to undergo resection at low-volume hospitals. However, little is known about the relationship between hospital safety-net burden and the likelihood of curative-intent surgery for black and white patients. This study analyzes whether hospital safety-net burden is associated with curative-intent surgery among adult early-stage NSCLC patients treated at facilities accredited by the American College of Surgeons Commission on Cancer.
Study Design:
Adult patients diagnosed with invasive initial primary early-stage (TNM I-II) NSCLC during 2003-2005 were obtained from the National Cancer Data Base. Curative-intent surgery included anatomic resection, wedge resection, and segmentectomy. Hospital safety-net burden was defined as the percent of cancer patients per facility that were Medicaid-insured or uninsured. Generalized estimating equations and linear mixed models were used to control for clustering by facility.
Results:
Of 52,853 evaluable patients, those treated at high safety-net burden facilities were significantly less likely (unadjusted p < 0.0001) to undergo curative-intent surgery than patients treated at low safety-net burden facilities. Controlling for patient and other facility characteristics, high safety-net burden remained significantly associated (p < 0.0001) with reduced likelihood of curative-intent surgery overall (odds ratio = 0.69; 95% CI, 0.62-0.77) and in black- and white-only models (odds ratio = 0.59, 95% CI, 0.48-0.73; odds ratio = 0.71; 95% CI, 0.63-0.80, respectively).
Conclusions:
Both black and white adult patients treated for early-stage NSCLC at high safety-net burden facilities are less likely to undergo curative-intent surgery than those treated at low safety-net burden facilities. Innovative solutions are needed to ensure quality cancer care at high safety-net burden facilities.