Related Experiment Video
Updated: May 29, 2026

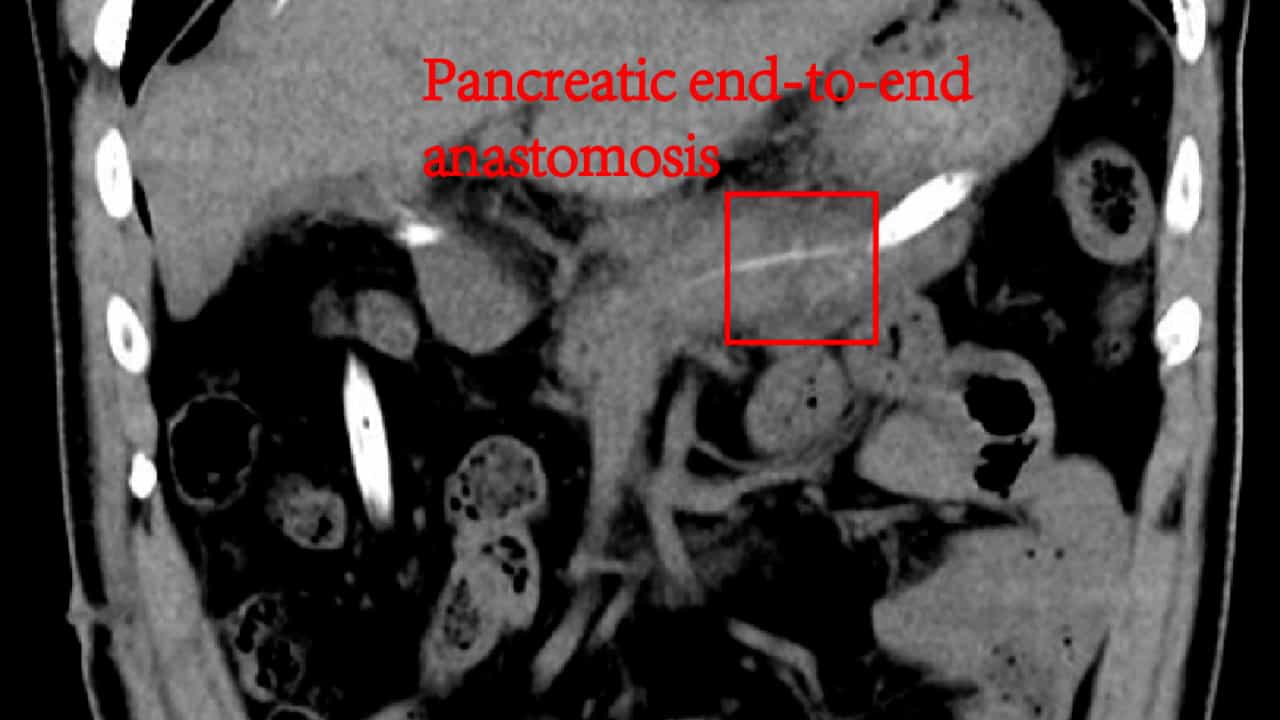
Application of Simplified Stent-bridging Pancreaticogastrostomy in Open Pancreaticoduodenectomy
Published on: March 17, 2026
Use of pancreatic duct stents after pancreaticoduodenectomy
1Division of Surgical Oncology, Johns Hopkins University, 600 North Wolfe Street, Blalock 685, Baltimore, MD 21212, USA. rschulick@jhmi.edu

Insights
Pancreatic duct stenting after pancreaticoduodenectomy shows mixed results. External stents may reduce pancreatic fistula rates, particularly in high-risk patients with soft glands and small ducts.
Area of Science:
- Gastroenterology
- Surgical Oncology
- Clinical Trials
Background:
- Pancreatic anastomosis leak is a major complication after pancreaticoduodenectomy, leading to significant morbidity and mortality.
- Identifying effective strategies to prevent pancreatic fistula is crucial for improving patient outcomes.
Purpose of the Study:
- To review level-one evidence from clinical trials on the efficacy of pancreatic duct stenting in reducing pancreatic fistula after pancreaticoduodenectomy.
Main Methods:
- Review of three randomized controlled trials and one prospective trial focusing on pancreaticoduodenectomy.
- Analysis of studies investigating internal versus external pancreatic duct stenting.
Main Results:
- Two studies found no benefit of internal pancreatic duct stenting in reducing pancreatic fistulas.
- Two studies indicated a potential benefit of external pancreatic duct stenting in reducing leakage rates.
- External stenting showed promise, especially for high-risk patients with specific pancreatic characteristics.
Conclusions:
- Internal pancreatic duct stenting does not consistently reduce pancreatic fistula rates.
- External pancreatic duct stenting may offer a protective advantage against pancreatic fistula after pancreaticoduodenectomy.
- Patient selection, particularly those with soft glands and small ducts, is important when considering external stenting.
Abstract:
After pancreaticoduodenectomy, the pancreatic anastomosis carries the highest risk of leak and cause of morbidity and mortality. In this review article, three randomized controlled clinical trials and a fourth prospective trial focused on pancreaticoduodenectomy that contribute to level-one evidence are examined. The Johns Hopkins group demonstrated that internal pancreatic duct stenting did not decrease the frequency or severity of postoperative pancreatic fistulas. The Queen Mary Hospital group demonstrated that external drainage of the pancreatic duct with a stent reduced the leakage rate of pancreaticojejunostomy after pancreaticoduodenectomy. The University of Athens group demonstrated that internal stenting of the pancreaticojejunostomy anastomosis did not reduce the incidence of pancreatic fistula and related complications. Finally, the French Surgery Research Group demonstrated that the use of an external stent through the pancreatic anastomosis reduced the pancreatic fistula rate. In summary, two studies do not demonstrate an advantage to the use of internal pancreatic duct stents and two studies demonstrate a possible advantage to the use of external pancreatic duct stents, especially in highest risk patients with soft glands and small pancreatic ducts.