Related Experiment Video
Updated: May 29, 2026

Evaluation of Coronary Flow Reserve After Myocardial Ischemia Reperfusion in Rats
Published on: June 28, 2019
Physiological basis for angina and ST-segment change PET-verified thresholds of quantitative stress myocardial
Nils P Johnson1, K Lance Gould
1Weatherhead PET Center For Preventing and Reversing Atherosclerosis, Division of Cardiology, Department of Medicine, University of Texas Medical School and Memorial Hermann Hospital, Houston, Texas, USA.

Objectives:
This study aimed to determine the quantitative low-flow threshold for stress-induced perfusion defects with severe angina and/or significant ST-segment depression during dipyridamole hyperemia.
Background:
Vasodilator stress reveals differences in regional perfusion without ischemia in most patients. However, in patients with a perfusion defect, angina, and/or significant ST-segment depression during dipyridamole stress, quantitative absolute myocardial perfusion and coronary flow reserve (CFR) at the exact moment of definite ischemia have not been established. Defining these low-flow thresholds of angina or ST-segment changes may offer insight into physiological disease severity in patients with atherosclerosis.
Methods:
Patients underwent rest-dipyridamole stress positron emission tomography (PET) with absolute flow quantification in ml/min/g. Definite ischemia was defined as a new or worse perfusion defect during dipyridamole stress with significant ST-segment depression and/or severe angina requiring pharmacological treatment. Indeterminate clinical features required only 1 of these 3 abnormalities. The comparison group included patients without prior myocardial infarction, or angina or electrocardiographic changes after dipyridamole.
Results:
In 1,674 sequential PET studies, we identified 194 (12%) with definite ischemia, 840 (50%) studies with no ischemia, and 301 (18%) that were clinically indeterminate. A vasodilator stress perfusion cutoff of 0.91 ml/min/g optimally separated definite from no ischemia with an area under the receiver-operator characteristic curve (AUC) of 0.98 and a CFR cutoff of 1.74 with an AUC = 0.91, reflecting excellent discrimination at the exact moment of definite ischemia.
Conclusions:
Thresholds of low myocardial vasodilator stress perfusion in ml/min/g and CFR sharply separate patients with angina or ST-segment change from those without these manifestations of ischemia during dipyridamole stress with excellent discrimination. Stress flow below 0.91 ml/min/g in dipyridamole-induced PET perfusion defects causes significant ST-segment depression and/or severe angina. However, when the worst vasodilator stress flow exceeds 1.12 ml/min/g, these manifestations of ischemia occur rarely.
Related Concept Videos
 01:29
Angina III: Clinical Manifestations and Assessment
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
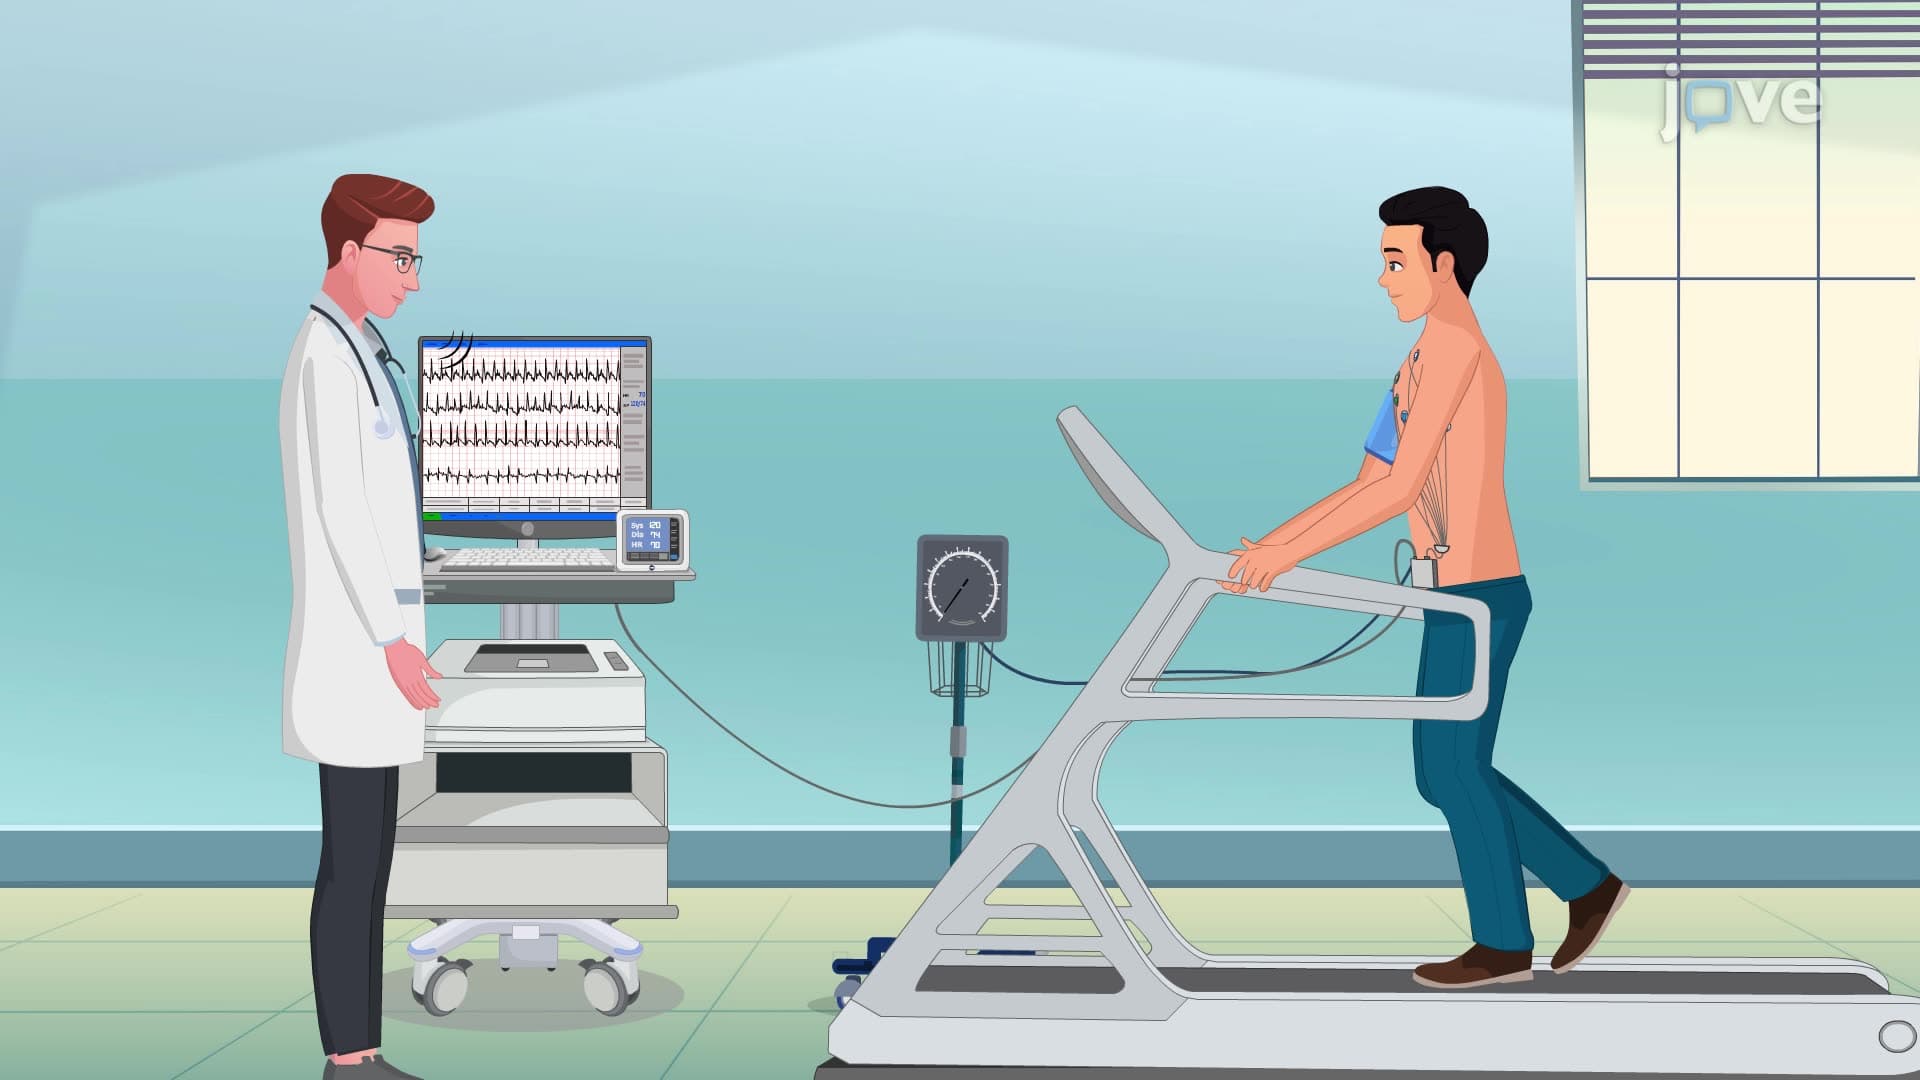
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Angina I: Introduction
 01:20
Angina V: Nursing Management