Related Experiment Video
Updated: May 29, 2026
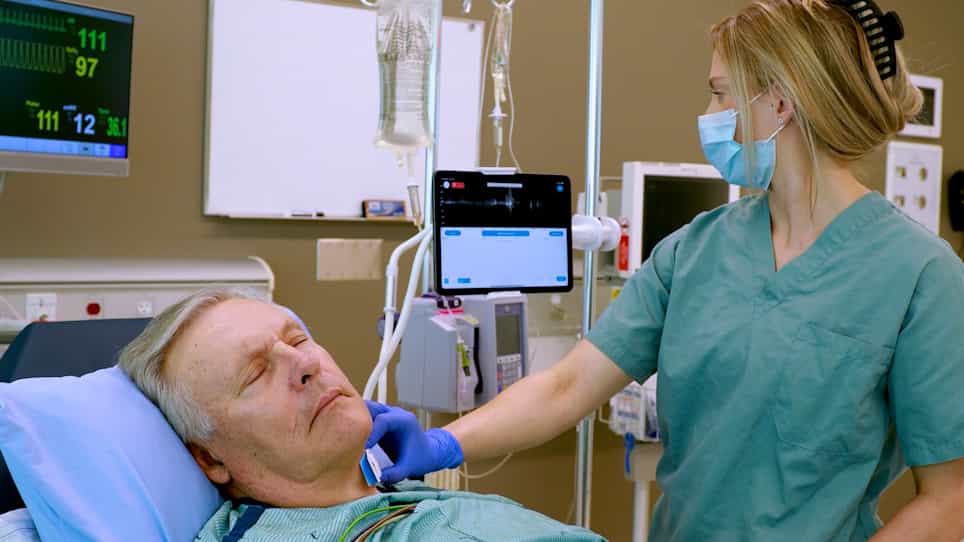

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Passive leg raising can predict fluid responsiveness in patients placed on venovenous extracorporeal membrane
Pierre-Grégoire Guinot1, Elie Zogheib, Mathieu Detave
1Department of Anesthesiology and Critical Care, Amiens University Hospital, Place Victor Pauchet, Amiens, F-80054, France. guinotpierregregoire@gmail.com

Introduction:
In ICUs, fluid administration is frequently used to treat hypovolaemia. Because volume expansion (VE) can worsen acute respiratory distress syndrome (ARDS) and volume overload must be avoided, predictive indicators of fluid responsiveness are needed. The purpose of this study was to determine whether passive leg raising (PLR) can be used to predict fluid responsiveness in patients with ARDS treated with venovenous extracorporeal membrane oxygenation (ECMO).
Methods:
We carried out a prospective study in a university hospital surgical ICU. All patients with ARDS treated with venovenous ECMO and exhibiting clinical and laboratory signs of hypovolaemia were enrolled. We measured PLR-induced changes in stroke volume (ΔPLRSV) and cardiac output (ΔPLRCO) using transthoracic echocardiography. We also assessed PLR-induced changes in ECMO pump flow (ΔPLRPO) and PLR-induced changes in ECMO pulse pressure (ΔPLRPP) as predictors of fluid responsiveness. Responders were defined by an increase in stroke volume (SV) > 15% after VE.
Results:
Twenty-five measurements were obtained from seventeen patients. In 52% of the measurements (n = 13), SV increased by > 15% after VE (responders). The patients' clinical characteristics appeared to be similar between responders and nonresponders. In the responder group, PLR significantly increased SV, cardiac output and pump flow (P < 0.001). ΔPLRSV values were correlated with VE-induced SV variations (r² = 0.72, P = 0.0001). A 10% increased ΔPLRSV predicted fluid responsiveness with an area under the receiver operating characteristic curve (AUC) of 0.88 ± 0.07 (95% confidence interval (CI95): 0.69 to 0.97; P < 0.0001), 62% sensitivity and 92% specificity. On the basis of AUCs of 0.62 ± 0.11 (CI₉₅: 0.4 to 0.8; P = 0.31) and 0.53 ± 0.12 (CI₉₅: 0.32 to 0.73, P = 0.79), respectively, ΔPLRPP and ΔPLRPO did not predict fluid responsiveness.
Conclusions:
In patients treated with venovenous ECMO, a > 10% ΔPLRSV may predict fluid responsiveness. ΔPLRPP and ΔPLRPO cannot predict fluid responsiveness.

Related Concept Videos
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system as it...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:11
Assessing Blood pressure in the Leg
Preparation: