Related Experiment Video
Updated: May 29, 2026
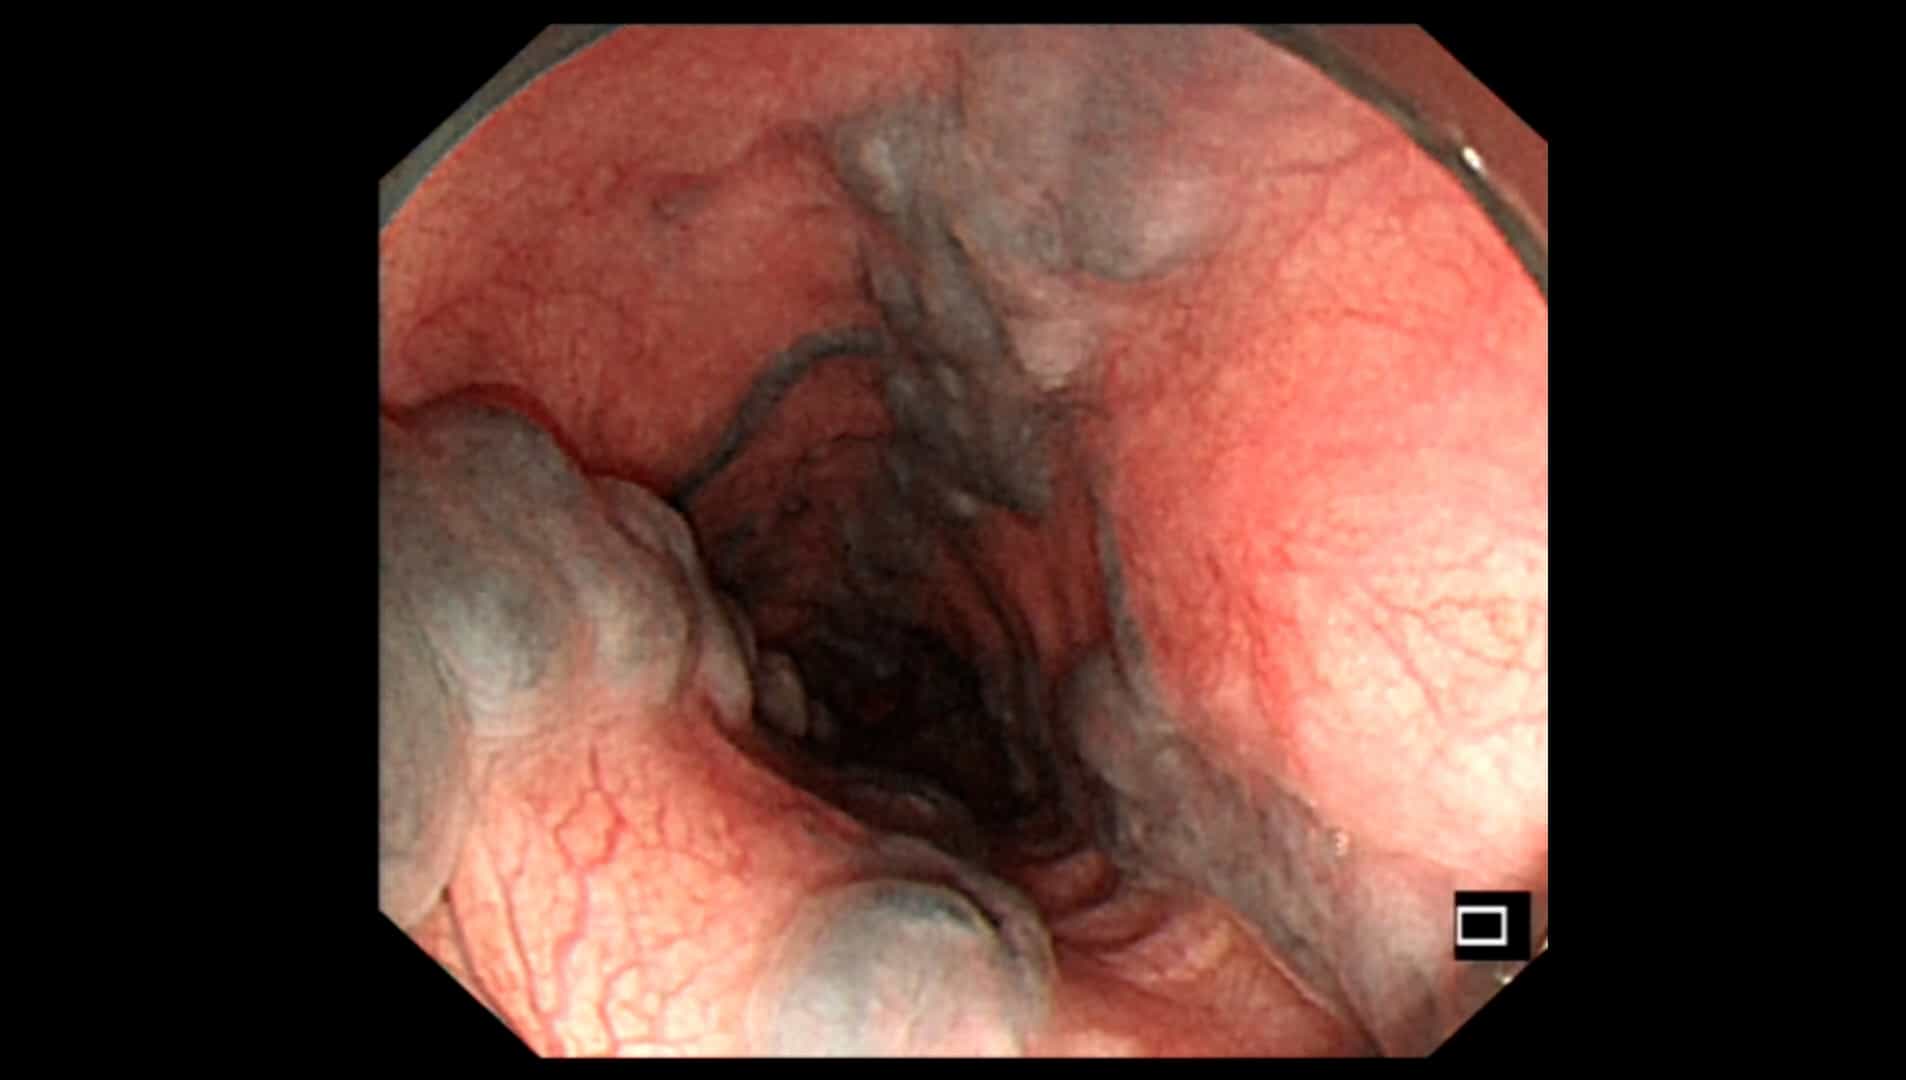

Underwater Endoscopic Injection Sclerotherapy for Gastroesophageal Varices
Published on: August 1, 2025
A clinical prediction rule and platelet count predict esophageal varices in children
Juan Cristóbal Gana1, Dan Turner, Giorgina Mieli-Vergani
1Division of Pediatrics, Gastroenterology, Hepatology and Nutrition Unit, Pontificia Universidad Católica de Chile, Santiago, Chile. jcgana@gmail.com

Insights
Noninvasive tests, including clinical prediction rules (CPR) and platelet counts, effectively identify esophageal varices in children. These methods help triage pediatric patients for necessary endoscopic evaluations, improving diagnostic accuracy.
Area of Science:
- Pediatric Gastroenterology
- Hepatology
- Diagnostic Medicine
Background:
- Esophageal varices diagnosis in children often requires invasive endoscopy.
- Noninvasive tests are needed to reduce patient burden and risk.
- A clinical prediction rule (CPR) was previously developed for this purpose.
Purpose of the Study:
- To validate a noninvasive clinical prediction rule (CPR) for diagnosing esophageal varices in pediatric patients.
- To assess the efficacy of noninvasive tests in identifying esophageal varices in children.
Main Methods:
- Data from 108 children (<18 years) with chronic liver disease or portal vein obstruction were analyzed.
- Endoscopic findings were correlated with blood tests and abdominal ultrasound (spleen size) results.
- The diagnostic accuracy of noninvasive predictors was evaluated using receiver operating characteristic curves.
Main Results:
- Esophageal varices were present in 69% of children studied.
- The platelet:spleen size z-score ratio (AUROC 0.84) and CPR (AUROC 0.80) were strong noninvasive predictors.
- Platelet count (AUROC 0.79) also showed significant predictive value.
Conclusions:
- Noninvasive tests, specifically CPR and platelet counts, can aid in triaging children for endoscopy.
- These diagnostic tools help identify patients with esophageal varices, optimizing care pathways.
- The findings support the use of noninvasive methods to guide pediatric endoscopic procedures.
Background & Aims:
The validation of noninvasive tests to diagnose esophageal varices is a priority in children because repeated endoscopic evaluations are too invasive. We measured the ability of a previously developed noninvasive clinical prediction rule (CPR) to predict the presence of esophageal varices in children.
Methods:
We analyzed data from 108 children, younger than age 18, who received endoscopies at 8 centers, to assess portal hypertension from chronic liver disease or portal vein obstruction. Blood test and abdominal ultrasound scan results were obtained within 4 months of endoscopy. Grading of varices identified by endoscopy was confirmed by independent blinded review. Spleen size, based on data from the ultrasound scan, was expressed as a standard deviation score relative to normal values for age.
Results:
Of the children studied, 74 had esophageal varices (69%), including 35 with large varices (32%). The best noninvasive predictors of esophageal varices of any size were as follows: platelet:spleen size z-score ratio (area under the receiver operating characteristic curve [AUROC], 0.84; 95% confidence interval [CI] 0.75-0.93), CPR (AUROC, 0.80; 95% CI, 0.70-0.91), and platelet count (AUROC, 0.79; 95% CI, 0.69-0.90). The positive predictive values for the CPR and platelet count were 0.87 and 0.86, the negative predictive values were 0.64 and 0.63, the positive likelihood ratios were 3.06 and 2.76, and the negative likelihood ratios were 0.64 and 0.63, respectively. Based on positive and negative predictive values, the most accurate noninvasive tests were the CPR and platelet counts.
Conclusions:
Noninvasive tests such as CPR and platelet count can assist in triaging children for endoscopy to identify esophageal varices.
More Related Videos


Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...